Mon, Sep 28, 2026
[Archive]
Volume 34, Issue 2 (March & April 2026)
J Adv Med Biomed Res 2026, 34(2): 166-174 |
Back to browse issues page


Ethics code: IR.BUMS.REC.1401.268


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Mortazavi Moghaddam S G, Nikoomanesh F, Ghaderi T, Babaiyan S. Fungal Colonization in Intubated ICU Patients: Prevalence, Risk Factors, and Clinical Outcomes. J Adv Med Biomed Res 2026; 34 (2) :166-174
URL: http://journal.zums.ac.ir/article-1-7754-en.html
URL: http://journal.zums.ac.ir/article-1-7754-en.html
Sayyed Gholamreza Mortazavi Moghaddam1 

 , Fatemeh Nikoomanesh2 , Tahereh Ghaderi *3 , Saeede Babaiyan4
1- Department of Internal Medicine, School of Medicine, Birjand University of Medical Sciences, Birjand, Iran
2- Infectious Diseases Research Center, Birjand University of Medical Sciences, Birjand, Iran
3- School of Medicine, Birjand University of Medical Sciences, Birjand, Iran. ,taherehghaderi88@gmail.com
4- Department of Anesthesiology, School of Medicine, Birjand University of Medical Sciences, Birjand, Iran
2- Infectious Diseases Research Center, Birjand University of Medical Sciences, Birjand, Iran
3- School of Medicine, Birjand University of Medical Sciences, Birjand, Iran. ,
4- Department of Anesthesiology, School of Medicine, Birjand University of Medical Sciences, Birjand, Iran
Keywords: Aspergillosis, Candidiasis, Fungal Colonization, Tracheobronchial Tree, Mechanical Ventilation, Bronchoalveolar lavage
Full-Text [PDF 458 kb]
(146 Downloads)
| Abstract (HTML) (802 Views)
Full-Text: (28 Views)
ABSTRACT
Background & Objective: Given the high prevalence of fungal colonization in intubated patients and the importance of diagnosing hospital-acquired fungal infections, this study aimed to investigate the prevalence of fungal colonization in the tracheobronchial tree of patients undergoing prolonged mechanical ventilation in the intensive care unit (ICU) and the associated risk factors affecting clinical outcomes.
Materials & Methods: In this cross-sectional study, the medical records of 100 patients admitted to the ICU of Vali Asr and Razi Hospitals in Birjand were reviewed and recorded in a structured checklist. Mini-BAL samples were collected from the endotracheal tube and placed in sterile Falcon tubes containing physiological saline for fungal analysis. Part of the sample was sent for direct microscopy using 10% KOH and culture, while another part was sent in a screw-capped tube at −20°C for molecular testing using polymerase chain reaction (PCR).
Results: In the initial examination, fungi were isolated from 43 samples in direct examination and culture, and fungal DNA was detected in 12 additional samples using PCR. Candida albicans (66.7%) was the most commonly identified species. Also, two cases of Aspergillus flavus were identified by culture and PCR. There was no significant relationship between risk factors and fungal infections. The mortality rate in patients with fungal infections was significantly higher than in those without fungal infections P = 0.019.
Conclusion: Considering the high prevalence of fungal infections in ICU patients, identifying risk factors and using accurate laboratory techniques to diagnose infection and implement effective treatment strategies can prevent the colonization of fungal agents in the tracheobronchial tree.
Keywords: Aspergillosis, Candidiasis, Fungal Colonization, Tracheobronchial Tree, Mechanical Ventilation, Bronchoalveolar Lavage
Fungal lung disease encompasses a wide spectrum of organisms and associated clinical conditions, presenting a significant global health challenge (1,2). In recent years, alongside the increase in patients at risk, fungal infections particularly those involving the respiratory tract have increased (3). Following the hospitalization of patients with serious conditions and susceptibility to infections in ICUs, as well as an increase in the duration of ICU stay, patients are exposed to numerous fungal species, particularly Candida and Aspergillus, through various sources (4). Risk factors associated with fungal colonization of the respiratory tract include the widespread use of antibiotics particularly broad-spectrum agents, the long-term use of immunosuppressive agents and corticosteroids, and the dramatic increase in the number of patients requiring care in specialized wards, as well as infirm patients needing indwelling catheters (5,6). Often, these risk factors that contribute to fungal colonization or fungal infection coexist in ICU-admitted patients.
Fungal colonization and the resulting infections are a major contributor to morbidity and mortality in the ICU (7). Studies have shown that total parenteral nutrition (TPN), sepsis, and surgeries were risk factors that led to a 60% rate of fungal colonization] in these patients (8,9). One of the common factors related to fungal colonization in ICU patients is the use of respiratory ventilation, which allows the spread of contamination from the endotracheal tube to the tracheobronchial tree and ultimately invasive fungal disease (9,10). Several reports have shown that the mortality rate of ICU patients with candidiasis and aspergillosis ranges from 40% to 42% (8). Candida spp, a component of normal human flora, and Aspergillus spp are common saprophytic fungal agents in the environment whose spores can penetrate the respiratory system and lead to colonization. Studies show that in the case of colonization by this type of fungus, β-D-glucan (BG), a major polysaccharide of the fungal cell wall, can act as a pro-inflammatory factor, causing disruption in the function of macrophages and neutrophils and predisposing individuals to bacterial infections (11-12). In the case of aspergillosis, it can trigger immunological reactions, and allergic bronchopulmonary aspergillosis (ABPA) is one such condition associated with aspergillosis in immunologically healthy individuals (13). The Mucorales family is a rare type that mainly causes pulmonary infections in immunocompromised hosts, and in invasive forms mortality is over 90% (10).
Invasive fungal (IF) infection leads to increased mortality in the case of delayed treatment (14). The lack of high‑sensitivity and high‑specificity diagnostic methods for the timely diagnosis of IF highlights the need for the identification of risk factors and evaluation methods to ensure timely treatment even in the absence of laboratory evidence of infection (15). Thus, treatment strategies for fungal lung diseases rely mainly on antifungal agents, but the emergence of antifungal‑resistant strains poses a substantial global threat and adds complexity to existing therapeutic challenges. In this study, we evaluated the prevalence of fungal colonization and investigated the associated risk factors related to long-term ICU admission.
2. Materials and Methods
2.1 Study Design and Population
In this cross-sectional study, 100 bronchoalveolar lavage (BAL) samples were collected from patients admitted to the ICUs of Razi and Vali Asr Hospitals in Birjand during the years 2022–2023. Demographic information of the patients was collected anonymously in structured checklists and kept confidential by the researcher.
Inclusion Criteria for the Study: All ICU-admitted and mechanically ventilated patients who had been hospitalized for at least 7 days. Informed consent for participation in the study was obtained from the patient or their relatives.
2.2 Exclusion Criteria
Sampling was excluded if it posed a risk to the patient, if the patient’s clinical condition made sampling impossible, or if informed consent was not obtained.
2.3 Sampling
Samples were collected as mini-BAL samples from the tracheobronchial tree through the endotracheal tube and placed in sterile Falcon tubes containing physiological saline for fungal analysis. The samples were immediately homogenized and divided into two parts: One portion was examined by direct microscopy and fungal culture, while the second portion was stored at −20°C in screw‑capped tubes for molecular testing. Only samples positive by both direct microscopy and culture were subjected to PCR analysis.
2.4 Microbiological Investigation
The BAL samples were referred to the laboratory for microscopic examination (16). Initially, to homogenize the sample, 10% trypsin was added and centrifuged at 3000 rpm for 15 minutes. The supernatant was discarded, and the remaining sediment was used for microscopic examination and culture.
The sediment was inoculated under strict sterile conditions onto Sabouraud Dextrose Agar (SDA) and Czapek’s Agar, then incubated at 28 °C for 7 days to allow for fungal growth and sufficient spore production. After this period, the media were examined for growth, and positive samples were identified.
2.5 Molecular Investigation by Polymerase Chain Reaction (PCR)
In this study, PCR was utilized with primers for the ITS1 and ITS4 regions specific for identifying Aspergillus spp., Candida spp., and Mucor spp. (17). Fungal DNA extraction was performed using a DNA extraction kit (Poya Gene Azma).
Positive controls included standard fungal strains of Candida from the microbiology department’s fungal archive, including Candida albicans (ATCC 10231), Candida glabrata (ATCC 2001), and Candida parapsilosis (ATCC 22019). Aspergillus fumigatus (ATCC 46645) and Aspergillus flavus (ATCC 204304) (the most common fungal strains in tracheobronchial colonization) were also considered.
2.6 First-round amplification
To amplify the 18S rDNA gene fragment, primers ITS1 and ITS4 were used. The primers were designed based on sequences available in the GenBank database for each genus of the studied fungi, which were blasted and synthesized from reliable sources.
The 25‑µL PCR mixture contained 2 µL of DNA template, 12.5 µL of master mix, and 1.5 pmol of each primer. (ITS1 5’TCC GTA GGT GAA CCT GCG G 3’ and ITS4 5’TCC TCC GCT TAT TGA TAT GC 3’) were adjusted to a final volume of 25 µL using DEPC water.
Reaction involved 1 cycle at 95˚C for 5 min, followed by 35 cycles with a denaturation step at 95˚C for 30s, an annealing step at 55°C for 1 min, and an extension step at, followed by 1 cycle at 72°C for 6 min.
2.7 Semi-nested amplification
For the second amplification, 1 µL of the first‑round PCR product was used in a 25‑µL semi‑nested PCR reaction mixture containing 12.5 µL of master mix and 1.5 pmol of ITS4 and ITS86 (5’ GTG AAT CAT CGA ATC TTT GAA C 3’), adjusted to a final volume of 25 µL using DEPC water.
Reaction conditions included 1 cycle at 95°C for 5 min, followed by 30 cycles of denaturation at 95°C for 30 s, annealing at 55°C for 30 s, and extension at 72°C for 30 s, followed by a final extension at 72°C for 6 min. The negative control included all PCR components except the DNA template.
The sizes of the amplified fragments for the desired strains with each primer are shown in Table 1. PCR was performed using the PeqSTAR 2X thermal cycler (PEQLAB, Germany). The PCR products were visualized using 2% agarose gel electrophoresis.
2.8 Statistical analysis
Data were entered into SPSS version 22 after collection. Descriptive statistics (central tendency and dispersion indices) were used to report descriptive data. The Kolmogorov-Smirnov test was employed to assess data normality. For data analysis, the Mann-Whitney test, the Chi-square test, or Fisher’s exact test was utilized. A significance level of P < 0.05 was considered statistically significant.
3. Result
3.1 Demographic characteristics of the patients
A total of 100 patients (52% female and 48% male) with a mean age of 66.17 ± 19.13 years were examined in this study. The age group of 60 to 80 years had the highest frequency (46%). The most common infections diagnosed upon admission were sepsis (47%) and pneumonia (26%). Other diagnoses included malignant disorders (n = 3), intoxications (n = 3), gastrointestinal disorders (n = 6), neurological disorders (n = 9), and cardiovascular or other medical conditions (n = 15). Regarding the source of ICU admission, 59 patients were transferred from internal medicine wards and 41 were admitted directly from the emergency departmentt.
3.2 Diagnosis of fungal colonization/ infection
In the initial examination using direct microscopy (using staining) and culture of BAL samples, 43 positive and 57 negative cases were identified for fungal elements (Figure 1A). Forty yeast and three mold isolates were recovered, with Candida albicans (56%, n = 24/43) being the most prevalent, followed by Candida glabrata (35%, n = 15/43) and Aspergillus spp. (7%, n = 3/43). Two mixed cultures containing both C. albicans and C. glabrata were identified (Figure 1B).
To confirm the results of microscopic examination and culture, DNA extraction from BAL samples was performed, followed by PCR testing using specific primers for Candida and Aspergillus species. The PCR results indicated that 12 samples were positive by molecular testing, which identified C. albicans (66.7%, n = 8/12), C. glabrata (16.7%, n = 2/12), and Aspergillus flavus (16.7%, n = 2/12). Notably, one culture-negative sample tested positive for A. flavus DNA via PCR, while two cases with positive Aspergillus cultures yielded negative PCR results. Overall, C. albicans was the predominant species, and two cases of A. flavus colonization were confirmed by molecular analysis.
3.3 Comparison of factors associated with fungal colonization/ infection
The results of the comparison of demographic and clinical conditions showed that there was no significant association between age, sex, or clinical condition and positive fungal colonization (Table 1).
Based on the results of this study, 27 patients survived and were discharged from the ICU, whereas 73 patients died. The mean duration of ICU stay was 24.36 ± 18.21 days, and the mean duration of mechanical ventilation was 23.63 ± 17.54 days.
There was no statistically significant association between the duration of general hospital stay, ICU stay, or mechanical ventilation and the occurrence of fungal colonization (Table 2).
In addition, systemic corticosteroids were administered to 55 patients. There was no statistically significant difference in the rate of fungal colonization between patients receiving antibiotics or corticosteroids and those who did not.
No significant correlation was observed between fungal colonization, other medications, and organ-specific complications (Table 3).
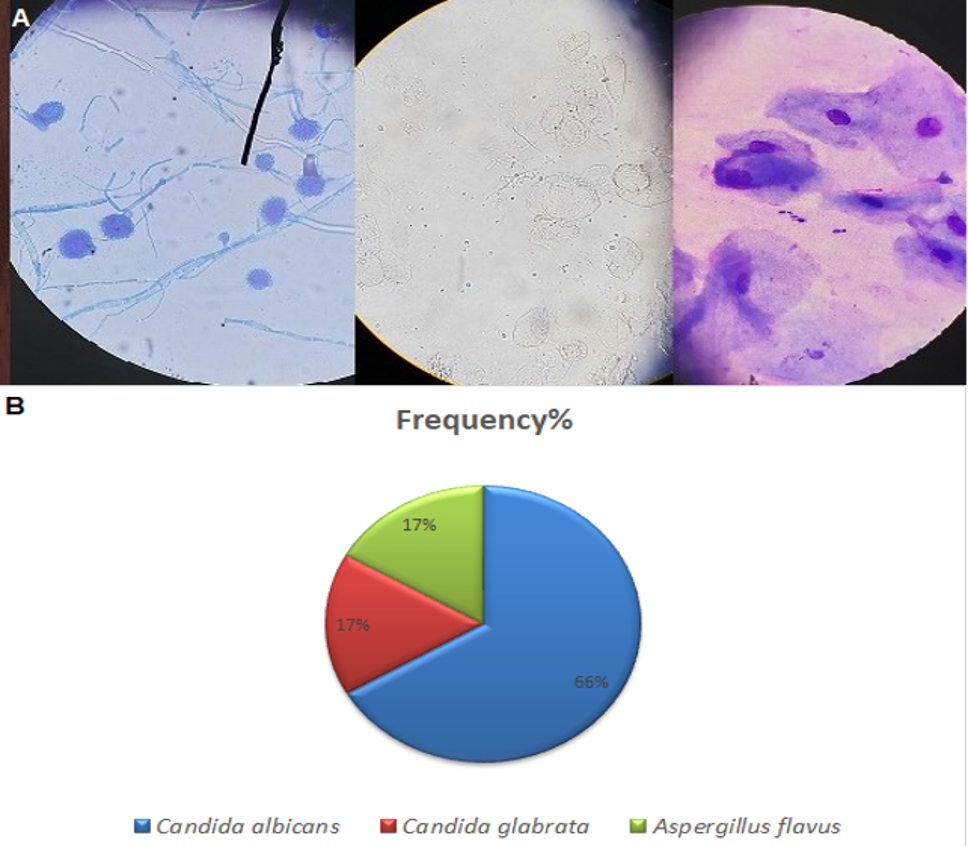
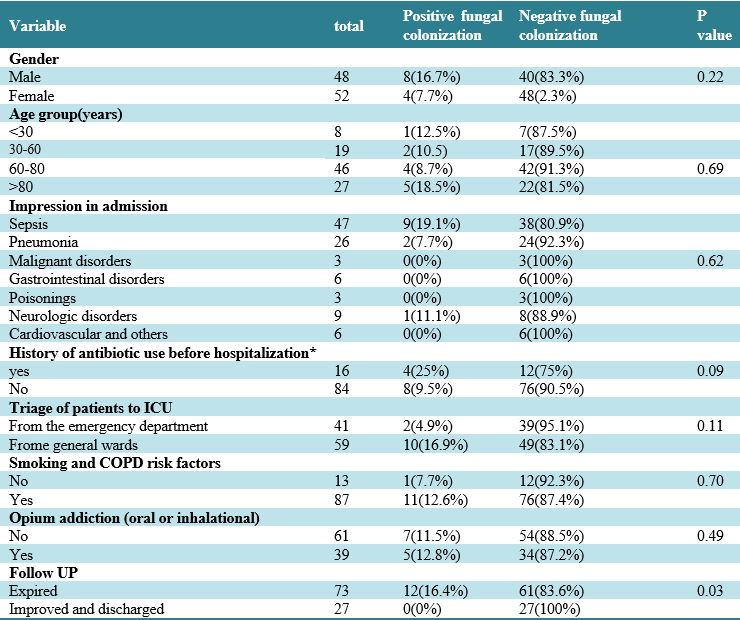
Table 2. Comparison of fungal colonization according to hospitalization days.
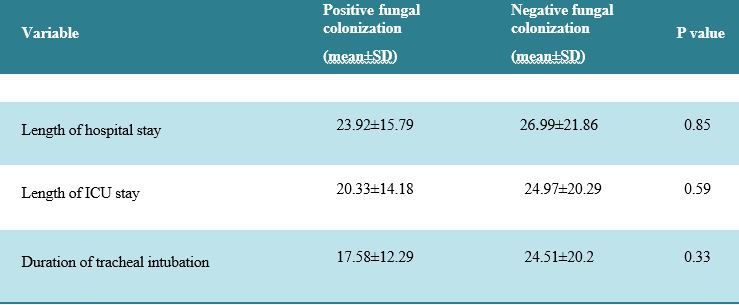
Table 3. Comparison of fungal colonization according to medications and organ complications.
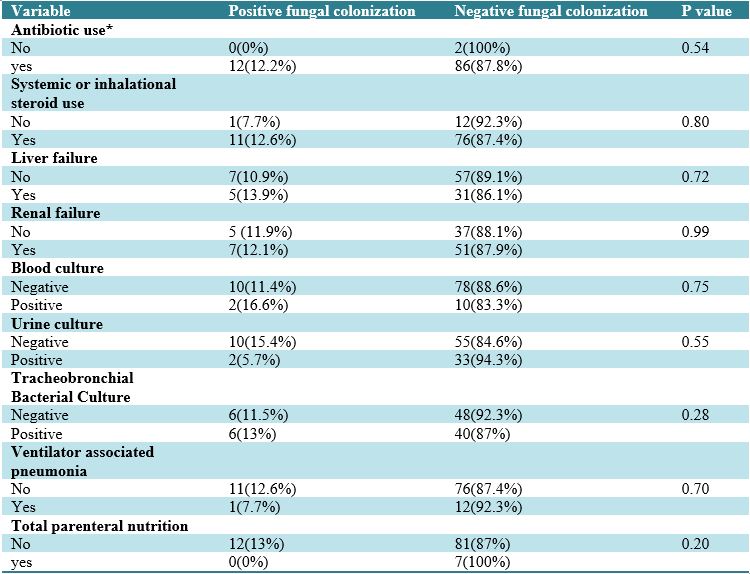
Note: *Taking antibiotics during hospitalization
4. Discussion
Fungal colonization of the tracheobronchial tract is globally responsible for a significant proportion, estimated at one-third, of mortality linked to lung infections. In this study, a total of 100 patients were analyzed; of these, 73 patients died during their ICU stay, and 27 recovered. However, fungal colonization was not detected in any of the surviving patients. Leon et al. reported that the mortality rate in ICU patients with invasive candidiasis was over 50% (9). In a study
conducted by Hamet et al., it was reported that 44% of the studied patients expired (3).
In the study by Khodavisi et al., it was reported that among the patients studied, 46.6% died and 53.3% recovered (18).
The incidence and etiology of pulmonary fungal infection can vary depending on the types of patients, hospital settings, and geographical locations. In this study, the most common
causes of hospitalization of patients in the ICU include sepsis, pneumonia, and cardiovascular diseases, which are
major risk factors contributing to increased mortality. According to studies, the use of broad-spectrum antibiotics, corticosteroid use, long-term use of immunosuppressive agents, diabetes, prolonged hospitalization duration, and long-term intubation and mechanical ventilation are considered important risk factors for fungal colonization in the respiratory tract (19–21). A study by Yi-si Zhao showed that all patients with a positive fungal sample within 48 hours of ICU admission exhibited six major clinical risk factors for fungal colonization. These were: arterial catheter, enteral nutrition, corticosteroids, broad-spectrum antibiotics, urinary catheter, and invasive mechanical ventilation (8). The results of the present study showed no significant association between the evaluated risk factors and fungal colonization (Table 2). Another parameter that increases fungal colonization and fungal pathogenicity is age, because with increasing age and a age-related decline in cell-mediated immunity, it puts them at risk of various fungal, bacterial, or viral infections. In the present study, however, no association was observed between age groups and the rate of fungal colonization.
Pulmonary fungal infection consists of fungal colonization initially as colonization in the pulmonary tract, potentially progressing to invasive pulmonary fungal infection. Considering that Candida spp. is one of the members of the natural microflora of the body, and Aspergillus spp. is one of the common fungi in the environment. Regarding the issue of patient triage, the process of transferring a patient from outside the hospital to the emergency room or from the general wards to the ICU provides an opportunity for the colonization by hospital-acquired pathogens. In the present study, no significant association was found between patient triage status and fungal colonization, but this is one of the points that should be considered in fungal colonization in the tracheobronchial system.
The present study results showed that fungal colonization was detected by microscopic examination or culture in 43 cases. Candida albicans was the most commonly identified fungus in patients. Similar to the present study, Van Bangen et al. (16), Rafat et al. (20), Khodavisi et al. (18), Ahmad et al. (19), Moçin et al. (21), and Roudbary et al. (22) reported that the most commonly identified organism in tracheal secretions of patients was Candida albicans. On the other hand, 12 cases were positive for the presence of fungi with all three diagnostic methods: microscopic examination, culture, and PCR. It should be noted that the PCR technique was performed directly on BAL samples and indicated the presence of fungal DNA in the lavage samples. The direct molecular analysis of BAL samples identified two cases that were culture-positive but PCR-negative, and one case that was culture-negative but PCR-positive for fungal DNA. Hoenigl et al., comparing the lateral-flow-device (LFD) test, a β-D-glucan (BDG) assay, and an Aspergillus-specific PCR assay using BAL fluid samples, reported that the PCR assay achieved 100% sensitivity (23).
Finally, an issue that may be associated with an increased risk of hospital-acquired infections, including fungal infections, is the use of TPN. Studies have shown that TPN can increase the risk of infection, including fungal and candidal infections, in patients. For this reason, some researchers have suggested that TPN and caloric intake should be delayed in ICU patients when clinically feasible (24,25). In the present study, there were no cases of TPN among patients with positive fungal colonization, and among those with negative fungal colonization, only 7 patients were treated with TPN.
5. Conclusion
According to our results, no specific factor was identified as a significant risk factor for fungal colonization] in the target group.
However, patients hospitalized in ICUs, due to prolonged hospitalization, are susceptible to colonization by resistant fungal strains, especially with various species of Candida and Aspergillus, which are the main causes of nosocomial pulmonary fungal infections. Under the influence of additional risk factors, such as prolonged hospitalization and long-term mechanical ventilation, this colonization can predispose patients to invasive fungal diseases. Thus, the clinical significance of airway colonization and its impact on mortality warrant further investigation, and routine laboratory screening for early diagnosis is recommended.
6. Declarations
6.1 Acknowledgments
The authors would like to thank the Vice-Chancellor for Research and Technology at Birjand University of Medical Sciences for supporting this study.
6.2 Ethical Considerations
The study protocol was approved by the Research Ethics Committee of Birjand University of Medical Sciences, Birjand, Iran (Approval Code: IR.BUMS.REC.1401.268).
6.3 Authors' Contributions
All authors contributed to the study design. GhMM and FN were involved in the initial idea of the study. FN, TGh, and S B participated in the data collection process. TGh and FN were involved in the data analysis. TGh, GhMM, FN, and SB contributed to the drafting of the manuscript. All authors have read and approved the content of the manuscript.
6.4 Conflict of Interest
The authors declare no conflicts of interest regarding the publication of this manuscript.
6.5 Fund or Financial Support
This work was supported by personal budget.
6.6 Using Artificial Intelligence Tools (AI Tools)
The authors were not utilized AI Tools.
Background & Objective: Given the high prevalence of fungal colonization in intubated patients and the importance of diagnosing hospital-acquired fungal infections, this study aimed to investigate the prevalence of fungal colonization in the tracheobronchial tree of patients undergoing prolonged mechanical ventilation in the intensive care unit (ICU) and the associated risk factors affecting clinical outcomes.
Materials & Methods: In this cross-sectional study, the medical records of 100 patients admitted to the ICU of Vali Asr and Razi Hospitals in Birjand were reviewed and recorded in a structured checklist. Mini-BAL samples were collected from the endotracheal tube and placed in sterile Falcon tubes containing physiological saline for fungal analysis. Part of the sample was sent for direct microscopy using 10% KOH and culture, while another part was sent in a screw-capped tube at −20°C for molecular testing using polymerase chain reaction (PCR).
Results: In the initial examination, fungi were isolated from 43 samples in direct examination and culture, and fungal DNA was detected in 12 additional samples using PCR. Candida albicans (66.7%) was the most commonly identified species. Also, two cases of Aspergillus flavus were identified by culture and PCR. There was no significant relationship between risk factors and fungal infections. The mortality rate in patients with fungal infections was significantly higher than in those without fungal infections P = 0.019.
Conclusion: Considering the high prevalence of fungal infections in ICU patients, identifying risk factors and using accurate laboratory techniques to diagnose infection and implement effective treatment strategies can prevent the colonization of fungal agents in the tracheobronchial tree.
Keywords: Aspergillosis, Candidiasis, Fungal Colonization, Tracheobronchial Tree, Mechanical Ventilation, Bronchoalveolar Lavage
1. Introduction
Fungal colonization and the resulting infections are a major contributor to morbidity and mortality in the ICU (7). Studies have shown that total parenteral nutrition (TPN), sepsis, and surgeries were risk factors that led to a 60% rate of fungal colonization] in these patients (8,9). One of the common factors related to fungal colonization in ICU patients is the use of respiratory ventilation, which allows the spread of contamination from the endotracheal tube to the tracheobronchial tree and ultimately invasive fungal disease (9,10). Several reports have shown that the mortality rate of ICU patients with candidiasis and aspergillosis ranges from 40% to 42% (8). Candida spp, a component of normal human flora, and Aspergillus spp are common saprophytic fungal agents in the environment whose spores can penetrate the respiratory system and lead to colonization. Studies show that in the case of colonization by this type of fungus, β-D-glucan (BG), a major polysaccharide of the fungal cell wall, can act as a pro-inflammatory factor, causing disruption in the function of macrophages and neutrophils and predisposing individuals to bacterial infections (11-12). In the case of aspergillosis, it can trigger immunological reactions, and allergic bronchopulmonary aspergillosis (ABPA) is one such condition associated with aspergillosis in immunologically healthy individuals (13). The Mucorales family is a rare type that mainly causes pulmonary infections in immunocompromised hosts, and in invasive forms mortality is over 90% (10).
Invasive fungal (IF) infection leads to increased mortality in the case of delayed treatment (14). The lack of high‑sensitivity and high‑specificity diagnostic methods for the timely diagnosis of IF highlights the need for the identification of risk factors and evaluation methods to ensure timely treatment even in the absence of laboratory evidence of infection (15). Thus, treatment strategies for fungal lung diseases rely mainly on antifungal agents, but the emergence of antifungal‑resistant strains poses a substantial global threat and adds complexity to existing therapeutic challenges. In this study, we evaluated the prevalence of fungal colonization and investigated the associated risk factors related to long-term ICU admission.
2. Materials and Methods
2.1 Study Design and Population
In this cross-sectional study, 100 bronchoalveolar lavage (BAL) samples were collected from patients admitted to the ICUs of Razi and Vali Asr Hospitals in Birjand during the years 2022–2023. Demographic information of the patients was collected anonymously in structured checklists and kept confidential by the researcher.
Inclusion Criteria for the Study: All ICU-admitted and mechanically ventilated patients who had been hospitalized for at least 7 days. Informed consent for participation in the study was obtained from the patient or their relatives.
2.2 Exclusion Criteria
Sampling was excluded if it posed a risk to the patient, if the patient’s clinical condition made sampling impossible, or if informed consent was not obtained.
2.3 Sampling
Samples were collected as mini-BAL samples from the tracheobronchial tree through the endotracheal tube and placed in sterile Falcon tubes containing physiological saline for fungal analysis. The samples were immediately homogenized and divided into two parts: One portion was examined by direct microscopy and fungal culture, while the second portion was stored at −20°C in screw‑capped tubes for molecular testing. Only samples positive by both direct microscopy and culture were subjected to PCR analysis.
2.4 Microbiological Investigation
The BAL samples were referred to the laboratory for microscopic examination (16). Initially, to homogenize the sample, 10% trypsin was added and centrifuged at 3000 rpm for 15 minutes. The supernatant was discarded, and the remaining sediment was used for microscopic examination and culture.
The sediment was inoculated under strict sterile conditions onto Sabouraud Dextrose Agar (SDA) and Czapek’s Agar, then incubated at 28 °C for 7 days to allow for fungal growth and sufficient spore production. After this period, the media were examined for growth, and positive samples were identified.
2.5 Molecular Investigation by Polymerase Chain Reaction (PCR)
In this study, PCR was utilized with primers for the ITS1 and ITS4 regions specific for identifying Aspergillus spp., Candida spp., and Mucor spp. (17). Fungal DNA extraction was performed using a DNA extraction kit (Poya Gene Azma).
Positive controls included standard fungal strains of Candida from the microbiology department’s fungal archive, including Candida albicans (ATCC 10231), Candida glabrata (ATCC 2001), and Candida parapsilosis (ATCC 22019). Aspergillus fumigatus (ATCC 46645) and Aspergillus flavus (ATCC 204304) (the most common fungal strains in tracheobronchial colonization) were also considered.
2.6 First-round amplification
To amplify the 18S rDNA gene fragment, primers ITS1 and ITS4 were used. The primers were designed based on sequences available in the GenBank database for each genus of the studied fungi, which were blasted and synthesized from reliable sources.
The 25‑µL PCR mixture contained 2 µL of DNA template, 12.5 µL of master mix, and 1.5 pmol of each primer. (ITS1 5’TCC GTA GGT GAA CCT GCG G 3’ and ITS4 5’TCC TCC GCT TAT TGA TAT GC 3’) were adjusted to a final volume of 25 µL using DEPC water.
Reaction involved 1 cycle at 95˚C for 5 min, followed by 35 cycles with a denaturation step at 95˚C for 30s, an annealing step at 55°C for 1 min, and an extension step at, followed by 1 cycle at 72°C for 6 min.
2.7 Semi-nested amplification
For the second amplification, 1 µL of the first‑round PCR product was used in a 25‑µL semi‑nested PCR reaction mixture containing 12.5 µL of master mix and 1.5 pmol of ITS4 and ITS86 (5’ GTG AAT CAT CGA ATC TTT GAA C 3’), adjusted to a final volume of 25 µL using DEPC water.
Reaction conditions included 1 cycle at 95°C for 5 min, followed by 30 cycles of denaturation at 95°C for 30 s, annealing at 55°C for 30 s, and extension at 72°C for 30 s, followed by a final extension at 72°C for 6 min. The negative control included all PCR components except the DNA template.
The sizes of the amplified fragments for the desired strains with each primer are shown in Table 1. PCR was performed using the PeqSTAR 2X thermal cycler (PEQLAB, Germany). The PCR products were visualized using 2% agarose gel electrophoresis.
2.8 Statistical analysis
Data were entered into SPSS version 22 after collection. Descriptive statistics (central tendency and dispersion indices) were used to report descriptive data. The Kolmogorov-Smirnov test was employed to assess data normality. For data analysis, the Mann-Whitney test, the Chi-square test, or Fisher’s exact test was utilized. A significance level of P < 0.05 was considered statistically significant.
3. Result
3.1 Demographic characteristics of the patients
A total of 100 patients (52% female and 48% male) with a mean age of 66.17 ± 19.13 years were examined in this study. The age group of 60 to 80 years had the highest frequency (46%). The most common infections diagnosed upon admission were sepsis (47%) and pneumonia (26%). Other diagnoses included malignant disorders (n = 3), intoxications (n = 3), gastrointestinal disorders (n = 6), neurological disorders (n = 9), and cardiovascular or other medical conditions (n = 15). Regarding the source of ICU admission, 59 patients were transferred from internal medicine wards and 41 were admitted directly from the emergency departmentt.
3.2 Diagnosis of fungal colonization/ infection
In the initial examination using direct microscopy (using staining) and culture of BAL samples, 43 positive and 57 negative cases were identified for fungal elements (Figure 1A). Forty yeast and three mold isolates were recovered, with Candida albicans (56%, n = 24/43) being the most prevalent, followed by Candida glabrata (35%, n = 15/43) and Aspergillus spp. (7%, n = 3/43). Two mixed cultures containing both C. albicans and C. glabrata were identified (Figure 1B).
To confirm the results of microscopic examination and culture, DNA extraction from BAL samples was performed, followed by PCR testing using specific primers for Candida and Aspergillus species. The PCR results indicated that 12 samples were positive by molecular testing, which identified C. albicans (66.7%, n = 8/12), C. glabrata (16.7%, n = 2/12), and Aspergillus flavus (16.7%, n = 2/12). Notably, one culture-negative sample tested positive for A. flavus DNA via PCR, while two cases with positive Aspergillus cultures yielded negative PCR results. Overall, C. albicans was the predominant species, and two cases of A. flavus colonization were confirmed by molecular analysis.
3.3 Comparison of factors associated with fungal colonization/ infection
The results of the comparison of demographic and clinical conditions showed that there was no significant association between age, sex, or clinical condition and positive fungal colonization (Table 1).
Based on the results of this study, 27 patients survived and were discharged from the ICU, whereas 73 patients died. The mean duration of ICU stay was 24.36 ± 18.21 days, and the mean duration of mechanical ventilation was 23.63 ± 17.54 days.
There was no statistically significant association between the duration of general hospital stay, ICU stay, or mechanical ventilation and the occurrence of fungal colonization (Table 2).
In addition, systemic corticosteroids were administered to 55 patients. There was no statistically significant difference in the rate of fungal colonization between patients receiving antibiotics or corticosteroids and those who did not.
No significant correlation was observed between fungal colonization, other medications, and organ-specific complications (Table 3).
Figure 1. A: Results of laboratory diagnosis from microscopic examination and culture of BAL samples; B: Identification of the frequency (%) of fungal species using the molecular PCR technique on BAL samples. (Prepared by Authors, 2026).
Table 1. Comparison of fungal colonization according to Demographic and Clinical conditionsTable 2. Comparison of fungal colonization according to hospitalization days.
Table 3. Comparison of fungal colonization according to medications and organ complications.
Note: *Taking antibiotics during hospitalization
4. Discussion
Fungal colonization of the tracheobronchial tract is globally responsible for a significant proportion, estimated at one-third, of mortality linked to lung infections. In this study, a total of 100 patients were analyzed; of these, 73 patients died during their ICU stay, and 27 recovered. However, fungal colonization was not detected in any of the surviving patients. Leon et al. reported that the mortality rate in ICU patients with invasive candidiasis was over 50% (9). In a study
conducted by Hamet et al., it was reported that 44% of the studied patients expired (3).
In the study by Khodavisi et al., it was reported that among the patients studied, 46.6% died and 53.3% recovered (18).
The incidence and etiology of pulmonary fungal infection can vary depending on the types of patients, hospital settings, and geographical locations. In this study, the most common
causes of hospitalization of patients in the ICU include sepsis, pneumonia, and cardiovascular diseases, which are
major risk factors contributing to increased mortality. According to studies, the use of broad-spectrum antibiotics, corticosteroid use, long-term use of immunosuppressive agents, diabetes, prolonged hospitalization duration, and long-term intubation and mechanical ventilation are considered important risk factors for fungal colonization in the respiratory tract (19–21). A study by Yi-si Zhao showed that all patients with a positive fungal sample within 48 hours of ICU admission exhibited six major clinical risk factors for fungal colonization. These were: arterial catheter, enteral nutrition, corticosteroids, broad-spectrum antibiotics, urinary catheter, and invasive mechanical ventilation (8). The results of the present study showed no significant association between the evaluated risk factors and fungal colonization (Table 2). Another parameter that increases fungal colonization and fungal pathogenicity is age, because with increasing age and a age-related decline in cell-mediated immunity, it puts them at risk of various fungal, bacterial, or viral infections. In the present study, however, no association was observed between age groups and the rate of fungal colonization.
Pulmonary fungal infection consists of fungal colonization initially as colonization in the pulmonary tract, potentially progressing to invasive pulmonary fungal infection. Considering that Candida spp. is one of the members of the natural microflora of the body, and Aspergillus spp. is one of the common fungi in the environment. Regarding the issue of patient triage, the process of transferring a patient from outside the hospital to the emergency room or from the general wards to the ICU provides an opportunity for the colonization by hospital-acquired pathogens. In the present study, no significant association was found between patient triage status and fungal colonization, but this is one of the points that should be considered in fungal colonization in the tracheobronchial system.
The present study results showed that fungal colonization was detected by microscopic examination or culture in 43 cases. Candida albicans was the most commonly identified fungus in patients. Similar to the present study, Van Bangen et al. (16), Rafat et al. (20), Khodavisi et al. (18), Ahmad et al. (19), Moçin et al. (21), and Roudbary et al. (22) reported that the most commonly identified organism in tracheal secretions of patients was Candida albicans. On the other hand, 12 cases were positive for the presence of fungi with all three diagnostic methods: microscopic examination, culture, and PCR. It should be noted that the PCR technique was performed directly on BAL samples and indicated the presence of fungal DNA in the lavage samples. The direct molecular analysis of BAL samples identified two cases that were culture-positive but PCR-negative, and one case that was culture-negative but PCR-positive for fungal DNA. Hoenigl et al., comparing the lateral-flow-device (LFD) test, a β-D-glucan (BDG) assay, and an Aspergillus-specific PCR assay using BAL fluid samples, reported that the PCR assay achieved 100% sensitivity (23).
Finally, an issue that may be associated with an increased risk of hospital-acquired infections, including fungal infections, is the use of TPN. Studies have shown that TPN can increase the risk of infection, including fungal and candidal infections, in patients. For this reason, some researchers have suggested that TPN and caloric intake should be delayed in ICU patients when clinically feasible (24,25). In the present study, there were no cases of TPN among patients with positive fungal colonization, and among those with negative fungal colonization, only 7 patients were treated with TPN.
5. Conclusion
According to our results, no specific factor was identified as a significant risk factor for fungal colonization] in the target group.
However, patients hospitalized in ICUs, due to prolonged hospitalization, are susceptible to colonization by resistant fungal strains, especially with various species of Candida and Aspergillus, which are the main causes of nosocomial pulmonary fungal infections. Under the influence of additional risk factors, such as prolonged hospitalization and long-term mechanical ventilation, this colonization can predispose patients to invasive fungal diseases. Thus, the clinical significance of airway colonization and its impact on mortality warrant further investigation, and routine laboratory screening for early diagnosis is recommended.
6. Declarations
6.1 Acknowledgments
The authors would like to thank the Vice-Chancellor for Research and Technology at Birjand University of Medical Sciences for supporting this study.
6.2 Ethical Considerations
The study protocol was approved by the Research Ethics Committee of Birjand University of Medical Sciences, Birjand, Iran (Approval Code: IR.BUMS.REC.1401.268).
6.3 Authors' Contributions
All authors contributed to the study design. GhMM and FN were involved in the initial idea of the study. FN, TGh, and S B participated in the data collection process. TGh and FN were involved in the data analysis. TGh, GhMM, FN, and SB contributed to the drafting of the manuscript. All authors have read and approved the content of the manuscript.
6.4 Conflict of Interest
The authors declare no conflicts of interest regarding the publication of this manuscript.
6.5 Fund or Financial Support
This work was supported by personal budget.
6.6 Using Artificial Intelligence Tools (AI Tools)
The authors were not utilized AI Tools.
Type of Study: Original Research Article |
Subject:
Medical Biology
Received: 2025/10/7 | Accepted: 2026/03/17 | Published: 2026/05/20
Received: 2025/10/7 | Accepted: 2026/03/17 | Published: 2026/05/20
References
1. Leroy O, Bailly S, Gangneux JP, Mira JP, Devos P, Dupont H, et al. Systemic antifungal therapy for proven or suspected invasive candidiasis: the AmarCAND 2 study. Ann Intensive Care. 2016;6(1):1-11. [DOI:10.1186/s13613-015-0103-7] [PMID] [PMCID]
2. León C, Ruiz-Santana S, Saavedra P, Galván B, Blanco A, Castro C, et al. Usefulness of the "Candida score" for discriminating between Candida colonization and invasive candidiasis in nonneutropenic critically ill patients: a prospective multicenter study. Crit Care Med. 2009;37(5):1624-33. [DOI:10.1097/CCM.0b013e31819daa14] [PMID]
3. Hamet M, Pavon A, Dalle F, Pechinot A, Prin S, Quenot J-P et al. Candida spp. airway colonization could promote antibiotic-resistant bacteria selection in patients with suspected ventilator-associated pneumonia. Intensive Care Med. 2012;38:1272-9. [DOI:10.1007/s00134-012-2584-2] [PMID]
4. Gupta N, Haque A, Lattif AA, Narayan RP, Mukhopadhyay G, Prasad R. Epidemiology and molecular typing of Candida isolates from burn patients. Mycopathologia. 2004;158(4):397-405. [DOI:10.1007/s11046-004-1820-x] [PMID]
5. Samonis G, Gikas A, Toloudis P, Maraki S, Vrentzos G, Tselentis Y, et al. Prospective study of the impact of broad-spectrum antibiotics on the yeast flora of the human gut. Eur J Clin Microbiol Infect Dis. 1994;(13):665-7. [DOI:10.1007/BF01973996] [PMID]
6. Biswas D, Agarwal S, Sindhwani G, Rawat J. Fungal colonization in patients with chronic respiratory diseases from Himalayan region of India. Ann Clin Microbiol Antimicrob. 2010;9:1-7. [DOI:10.1186/1476-0711-9-28] [PMID] [PMCID]
7. Paramythiotou E, Frantzeskaki F, Flevari A, Armaganidis A, Dimopoulos G. Invasive fungal infections in the ICU: how to approach, how to treat. Molecules. 2014;19(1):1085-119. [DOI:10.3390/molecules19011085] [PMID] [PMCID]
8. Zhao YS, Lai QP, Tang H, Luo RJ, He ZW, Huang W, et al. Identifying the risk factors of ICU-acquired fungal infections: clinical evidence from using machine learning. Front Med. 2024;11(1386161). [DOI:10.3389/fmed.2024.1386161] [PMID] [PMCID]
9. León C, Alvarez-Lerma F, Ruiz-Santana S, León MA, Nolla J, Jordá R, et al. Fungal colonization and/or infection in non-neutropenic critically ill patients: results of the EPCAN observational study. Eur J Clin Microbiol Infect Dis. 2009;28(3):233-42. [DOI:10.1007/s10096-008-0618-z] [PMID]
10. Atwood DN, Kumbla PA, Yuen B, Yuen JC. Management of a Case of Mucor Colonization in Breast Tissue Expander Seroma Pocket. World J Plast Surg. 2018;7(1):109-12.
11. Tan X, Zhu S, Yan D, Chen W, Chen R, Zou J, et al. Candida spp. Airway colonization: A potential risk factor for acinetobacter baumannii ventilator-associated pneumonia. Med Mycol. 2016;54(6):557-66. [DOI:10.1093/mmy/myw009] [PMID]
12. De Pascale, G., Antonelli M. Candida colonization of respiratory tract: to treat or not to treat, will we ever get an answer? Intensive Care Med. 2014;40:1381-1384. [DOI:10.1007/s00134-014-3364-y] [PMID]
13. Moldoveanu B, Gearhart AM, Jalil BA, M S, Guardiola JJ. Pulmonary Aspergillosis: Spectrum of Disease. Am J Med Sci. 2021;361(4):411-9. [DOI:10.1016/j.amjms.2020.12.009] [PMID]
14. Chakraborti A, Jaiswal A, Verma PK SR. A prospective study of fungal colonization and invasive fungal disease in long-term mechanically ventilated patients in a respiratory intensive care unit. Indian J Crit Care Med. 2018;22(8):597. [DOI:10.4103/ijccm.IJCCM_181_18] [PMID] [PMCID]
15. Ferreira EG, Yatsuda F, Pini M, Jarros IC, Veiga FF, de Oliveira AG et al. Implications of the presence of yeasts in tracheobronchial secretions of critically ill intubated patients. EXCLI J. 2019;18:801.
16. van Bang N, Xuan NT, Quang DX, Loi CB, Ngoc Minh NT, Lam NN, et al. Prevalence, species distribution, and risk factors of fungal colonization and infection in patients at a burn intensive care unit in Vietnam. Curr Med Mycol. 2021;6(3):42-9.
17. Ferrer C, Colom F, Frasés S, Mulet E, Abad JL, Alió JL. Detection and identification of fungal pathogens by PCR and by ITS2 and 5.8S ribosomal DNA typing in ocular infections. J Clin Microbiol. 2001;39(8):2873-9. [DOI:10.1128/JCM.39.8.2873-2879.2001] [PMID] [PMCID]
18. Khodavaisy S, Alialy M, Mahdavi Omran S, Habibi MR, Amri P, Monadi M et al. The study on fungal colonization of respiratory tract in patients admitted to intensive care units of sari and Babol hospitals. Med J Mashhad Univ Med Sci. 2011;54(3):177-84.
19. Ahmed MM, Farghaly AA, Raafat RH AEW. Study of the prevalence and pattern of fungal pneumonias in respiratory intensive care units. Egypt J Bronchol. 2019;13:545-50. [DOI:10.4103/ejb.ejb_37_19]
20. Rafat Z, Hashemi SJ, Ashrafi K, Nikokar I, Jafari A, Rahimi Foroushani A et al. Fungal isolates of the respiratory tract in symptomatic patients hospitalized in pulmonary units: a mycological and molecular epidemiologic study. J Multidiscip Healthc. 2020;661-9. [DOI:10.2147/JMDH.S252371] [PMID] [PMCID]
21. Moçin ÖY, Karakurt Z, Aksoy F, Güngör G, Partal M, Adigüzel N et al. Bronchoscopy as an indicator of tracheobronchial fungal infection in non-neutropenic intensive-care unit patients. Clin Microbiol Infect. 2013;19(3):E136-41. [DOI:10.1111/1469-0691.12112] [PMID]
22. Roudbary M, Keyvani H, Mousavi SAJ, Esghaei M, Roudbarmohammadi S, Hedayati N, et al. Investigation of fungal colonization among iranian patients with idiopathic pulmonary fibrosis; Molecular identification and antifungal susceptibility pattern. Arch Clin Infect Dis. 2019;14(2). [DOI:10.5812/archcid.65758]
23. Hoenigl M, Prattes J, Spiess B, Wagner J, Prueller F, Raggam RB, et al. Performance of galactomannan, beta-d-glucan, aspergillus lateral-flow device, conventional culture, and pcr tests with bronchoalveolar lavage fluid for diagnosis of invasive pulmonary aspergillosis. J Clin Microbiol. 2014;52(6):2039-45. [DOI:10.1128/JCM.00467-14] [PMID] [PMCID]
24. Muskett H, Shahin J, Eyres G. Risk factors for invasive fungal disease in critically ill adult patients: a systematic review. Crit Care Med. 2011;15(R287). [DOI:10.1186/cc10574] [PMID] [PMCID]
25. De Vlieger G, Ingels C, Wouters PJ, Debaveye Y, Vanhorebeek I, Wauters J, et al. Impact of supplemental parenteral nutrition early during critical illness on invasive fungal infections: a secondary analysis of the EPaNIC randomized controlled trial. Clin Microbiol Infect. 2019;25(3):359-64. [DOI:10.1016/j.cmi.2018.05.017] [PMID]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |
Copyright Policy
Journal of Advances in Medical and Biomedical Research by Zanjan University of Medical Sciences is licensed under CC BY-NC 4.0