Sat, Oct 3, 2026
[Archive]
Volume 34, Issue 3 (May & June 2026)
J Adv Med Biomed Res 2026, 34(3): 220-229 |
Back to browse issues page

Ethics code: IR.ZUMS.BLC.1402.062


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Hasanzadeh Shoeili Z, Mohsenpour N, Talebi T, Sharafi A. Expression and Purification of a Recombinant Fc-PTPRZ1 Fusion Protein as a Glioblastoma Vaccine Candidate. J Adv Med Biomed Res 2026; 34 (3) :220-229
URL: http://journal.zums.ac.ir/article-1-7941-en.html
URL: http://journal.zums.ac.ir/article-1-7941-en.html


1- Zanjan Pharmaceutical Biotechnology Research Center, Zanjan University of Medical Sciences, Zanjan, Iran
2- Zanjan Pharmaceutical Biotechnology Research Center, Zanjan University of Medical Sciences, Zanjan, Iran ,sharafi.a@gmail.com
2- Zanjan Pharmaceutical Biotechnology Research Center, Zanjan University of Medical Sciences, Zanjan, Iran ,
Full-Text [PDF 509 kb]
(68 Downloads)
| Abstract (HTML) (635 Views)
Table 1. Primer sequences and cleavage sites of the restriction endonucleases.
2.4 Preparation of competent cells
Competent E. coli DH5α cells were generated by inoculating the strain into LB medium lacking antibiotics overnight (12 -16 h).
The cells were inoculated in to fresh LB medium and allowed to grow until the OD600 reached 0.4. The culture was then transferred into a sterile, pre-chilled 50-mL centrifuge tube and centrifuged at 4000 rpm for 5 minutes at 4°C. The supernatant was discarded, and the cell pellets
were gently resuspended in 10 mL of cold, sterile TFB1 transformation buffer.
The suspension was centrifuged again under the same conditions. Subsequently, the pellet was resuspended in 1 mL of cold, sterile TFB2 buffer. The cell suspension was incubated in an ice-water bath for 15 minutes and then aliquoted into 1.5-mL microcentrifuge tubes at 1,000 µL per tube. The competent cells were stored at −70°C until further use.
2.5 Preparation of vector and insert DNA
Plasmid DNA with the template (pET28a-IL13-TNC-PTPRZ1) was isolated from E. coli (DH5α) using the alkaline lysis method. The PTPRZ1 gene was PCR-amplified with Pfu DNA polymerase. The PCR program began with denaturation at 94°C for 5 minutes, followed by 30 cycles of 94°C for 20 seconds, 64°C for 20 seconds, and 72°C for 45 seconds.
A final extension was done at 72°C for 15 minutes. PCR products were analyzed on an agarose gel and purified with a commercial gel extraction kit. DNA fragments were purified from agarose gels through the Addbio® (Korea) kit, following the manufacturer’s instructions. The pET28a-Fc plasmid was also extracted from DH5α using the alkaline lysis method. This plasmid was double-digested with EcoRI and BamHI, then purified by gel extraction and confirmed by agarose gel electrophoresis.
2.6 Ligation and Transformation into E. coli DH5α
Specifically, the PCR-amplified PTPRZ1 fragment and the pET28a-Fc vector were digested with BamHI and EcoRI at 37 °C for 2 hours. Subsequently, the reaction products were purified using a DNA clean-up kit. The insert was then ligated into the vector with T4 DNA ligase at 16 - 22 °C for 2 hours to generate pET28a-Fc-PTPRZ1. After ligation, the mixture was introduced into competent E. coli DH5α cells using the standard heat-shock method. Positive clones were identified by colony PCR with T7 primers and confirmed by restriction digestion analysis.
2.7 Transformation and Expression of Recombinant Protein in E. coli BL21 (DE3)
The recombinant plasmid pET28a-Fc-PTPRZ1 was transformed into E. coli BL21 (DE3) competent cells.
Colonies were cultured in 5 mL of LB broth supplemented with 50 μg/mL kanamycin at 37°C with shaking at 140 rpm until the culture reached an OD₆₀₀ of 0.6.
Protein expression was induced by adding 1 mM IPTG (Isopropyl β-d-1-thiogalactopyranoside) at 37 °C. Cultures were collected at 2, 4, and overnight post-induction, centrifuged at 12,000 rpm for 1 minute, and pellets were stored at −20 °C for later use.
2.8 Protein Purification
The bacterial cells were lysed by sonication at 100% amplitude for 1 second at 2-second intervals, for a total of 3 minutes. After that, the lysate was centrifuged at 13000 rpm and 4°C for 20 minutes. The resulting protein-enriched lysate was then subjected to denaturing purification using Ni-NTA affinity chromatography. To achieve effective extraction, the sample was dissolved in a buffer containing 8 M urea at pH 7.8, then loaded onto the chromatography column. The Fc–PTPRZ1 recombinant protein was eluted in 30 mM and 300 mM imidazole solutions. The fractions were collected and passed through a 0.22-μm-diameter nitrocellulose membrane. Finally, dialysis was used overnight in PBS buffer (pH 7.5) at 4 °C to remove any remaining imidazole and other impurities (17).
2.9 SDS-PAGE protein expression
Recombinant protein expression was evaluated in E. coli BL21 (DE3) using SDS-PAGE with a 12% separating gel. Samples were electrophoresed at 120 V for 120 minutes. The gel was stained with Coomassie Brilliant Blue R-250.
2.10 Western blot analysis
For Western blot analysis, SDS-PAGE was performed for protein separation. Then, the obtained unstained gel was transferred to a PVDF membrane at 100 V for 2 hours. We blocked the membrane with 5% skim milk in Tris-buffered saline (TBS), then incubated it with anti-His tag antibody (Sigma-Aldrich, St. Louis, MO, USA) for 2 hours at 37 °C with gentle shaking. Next, we washed the membrane three times with TBS-Tween (TBST) and incubated it with a horseradish peroxidase (HRP)-conjugated secondary antibody. After more washes with TBST to remove unbound antibodies, obtained PVDF membrane was treated using an HRP substrate solution containing 3, 3′-diaminobenzidine (DAB) and 30% hydrogen peroxide (H₂O₂). To stop the reaction, the membrane was washed three times with distilled water (17).
2.11 Bradford Assay
The concentration of the purified recombinant protein was measured using the Bradford colorimetric assay. A standard curve was generated using bovine serum albumin (BSA) at concentrations ranging from 0 to 20 µg/mL, and absorbance values were recorded at 595 nm. The protein concentration in the eluted fractions was measured using the standard curve.
All concentration measurements were performed three times to ensure reproducibility and improve data accuracy.
3. Result
3.1 Extraction of pET28a-IL13-TNC-PTPRZ1 Plasmid and PCR Amplification of PTPRZ1
Plasmid pET28a-IL13-TNC-PTPRZ1 was efficiently extracted from E. coli DH5α using the alkaline lysis method, and the expected plasmid band was observed on a 1% agarose gel (Figure 1A).
In the present study, only the PTPRZ1 gene was specifically amplified from this plasmid and subsequently cloned into the pET28a-Fc vector. PCR amplification yielded a 465 bp fragment corresponding to the PTPRZ1 gene, as shown in Figure 1B, and this was confirmed by agarose gel electrophoresis. The PCR product was then purified using a gel recovery kit (Figure 1C).
Full-Text: (50 Views)
ABSTRACT
Background & Objective: Glioblastoma multiforme (GBM) is one of the most aggressive primary brain tumors and is characterized by a poor prognosis and limited therapeutic options. Protein tyrosine phosphatase receptor type Z1 (PTPRZ1) is overexpressed in GBM and represents a promising target for immunotherapeutic intervention.
Materials & Methods: In the present study, Fc-fusion technology was employed to enhance the stability and potentially improve the functional activity of the recombinant protein. A PTPRZ1 fragment was inserted into the pET28a expression vector and subsequently transformed into E. coli BL21 (DE3) cells using the heat-shock method. Recombinant protein expression was optimized by evaluating different induction times (2, 4, and overnight), using an IPTG concentration of 1 mM, and incubating the cultures at 37°C for initial growth and induction. Recombinant protein expression in E. coli BL21 (DE3) was confirmed by SDS-PAGE, Bradford assay, and Western blot analysis.
Results: The SDS-PAGE analysis revealed a recombinant protein with an estimated molecular weight of about 46.3 kDa. The protein was subsequently purified under denaturing conditions using Ni-NTA affinity chromatography. The insoluble fraction exhibited the highest protein concentration, approximately 700 µg/mL, as determined by the Bradford assay at 595nm. Western blot analysis further confirmed the recombinant protein, with an approximate molecular weight of 46.3 kDa.
Conclusion: The present findings indicate that Fc-PTPRZ1 fusion proteins may serve as useful tools for the immunotherapy of glioblastoma; however, further in vivo studies are required to evaluated their immunogenicity and therapeutic potential.
Keywords: PTPRZ1, Fc-fusion protein, Glioblastoma, Recombinant protein, Immunotherapy
1. Introduction
Glioblastoma, also referred to as glioblastoma multiforme is one of the most common and aggressive primary brain tumors in adults, accounting for approximately 15%–20% of all primary brain tumors (1). Its annual incidence ranges from 1.9 to 9.6 cases per 100,000 individuals (2, 3). The incidence of GBM increases with age, rising substantially after the age of 40 and peaking among individuals aged 75–84 years, although most cases are diagnosed during the sixth and seventh decades of life. Globally, GBM occurs more frequently in males than in females, with an approximately 1.6-fold higher incidence in men (3). GBM arises from astrocytes, a group of star-shaped glial cells that surround and support neurons in the central nervous system (CNS). GBMs, for the most part, display a dismal prognosis with remarkable clinical challenges. The World Health Organization classifies GBM as a grade IV astrocytoma, characterized by rapid growth, diffuse infiltration of the adjacent cerebral parenchyma, extensive angiogenesis, and pronounced genetic heterogeneity. The heterogeneity of GBM is the source of resistance to available treatments, including radiation, surgery, and chemotherapy (4). Since GBM can start in or spread to a wide range of areas of the brain, a curative surgical procedure is often impossible. Indeed, when feasible, complete tumor removal is rarely achievable, and the detection of residual tumor cells is associated with recurrence in most patients (5). Subsequently, surgical methods are commonly performed in conjunction with radiotherapy and chemotherapy. In terms of chemotherapy, drugs are often designed to prevent cell DNA replication and tumor angiogenesis, such as Temozolomide (TMZ), which is the most widely used option for the treatment of GBM (6). The median survival time for patients diagnosed with GBM is only about 15 months (3). The blood-brain barrier (BBB), which plays a crucial role in maintaining the fundamental stability of brain tissue under normal physiological conditions of the CNS, also poses a notable challenge for delivering therapeutic agents to GBMs, and numerous therapeutic compounds don’t pass through the BBB effectively. Unfortunately, recent treatment approaches have had an exceptionally limited effect on improving the prognosis of GBM patients. Hence, noteworthy challenges and opportunities lie in finding the most viable therapeutic choices against GBM. Since there’s no cure for GBM, this underscores the urgency of developing new treatment methods to improve patient outcomes (7).
Immunotherapy has recently emerged as a rising star in the battle against cancer (8), and tumor vaccination has been among the most remarkable techniques for controlling immune responses, thereby strengthening local immunity and, accordingly, achieving therapeutic effects (9). Enhanced protein stability and extended half-life, achieved through the incorporation of the Fc domain of human IgG, result in Fc-fusion proteins with significant therapeutic potential (10, 11). The Fc region of Fc-fusion proteins enables efficient, cost-effective expression and purification. Other Fc-fusion constructs are also considered important players in preclinical and clinical oncology settings, including Asunercept (CD95-Fc) in GBM (12), chlorotoxin-Fc (13), and IL-12Fc (14).
The PTPRZ1 gene (OMIM #176891) encodes receptor-type tyrosine-protein phosphatase zeta (PTPRZ1), a member of the R5 subfamily of the receptor tyrosine phosphatase family. It is highly overexpressed in CNS glial cells and has been considered a therapeutic target for GBM (1). The human ortholog of PTPRZ, known as PTPRZ1, is highly expressed in malignant gliomas (15, 16). PTPRZ1 overexpression has been reported in other cancers, including cervical, lung, renal, hepatic, and glioblastoma tumors. Its expression is inversely associated with survival in GBM patients. Inhibition of PTPRZ1 attenuates the harmful and pernicious properties of glioblastoma cells, including cell proliferation, in vitro motility, and in vivo tumorigenicity. The above findings indicate that PTPRZ1 is a potential therapeutic target for the management of malignant glioma. In this context, we chose PTPRZ1 as a glioma-associated target (9) and designed, cloned, expressed, and purified a fusion construct comprising the Fc domain of immunoglobulin G1 and the antigen PTPRZ1 (Fc-PTPRZ1) in E. coli for potential applications in targeted GBM immunotherapy.
2. Materials and Methods
2.1 Bacterial Strains and Plasmids
Recombinant protein expression was carried out using E. coli BL21 (DE3) (Novagen, Madison, WI, USA), a high-yield expression strain.
The E. coli DH5α strain was used for cloning and construct validation. The recombinant plasmid pET28a-IL13-TNC-PTPRZ1, constructed and characterized in our previous study (17), served as the template for this work.
Herein, only the PTPRZ1 gene was amplified from this plasmid by PCR and subsequently cloned into the pET28a-Fc expression vector, which includes the Fc domain of immunoglobulin G1, to generate the recombinant construct pET28a-Fc-PTPRZ1.
2.2 Bacterial Culture and Storage
A loop of bacterial cells was placed in 5 mL of Luria-Bertani (LB) medium and incubated overnight at 37°C to maintain E. coli BL21 (DE3) and DH5α strains.
After incubation, the culture was mixed with 15% glycerol and stored in 1.5 mL cryovials at -70°C for long-term storage. For subsequent experiments, bacterial cells were grown at 37°C in 5 mL of LB medium containing kanamycin (50 μg/mL) under sterile conditions.
2.3 PTPRZ1 Primer Design and Preparation
First, we performed a gradient PCR to determine the optimal annealing temperature. We then amplified the DNA with Pfu DNA polymerase (Addbio®, Korea).
We designed the forward and reverse primers for PTPRZ1 using Oligo7 software (v0.4.0;29) and validated them with the BLAST tool (https://www.ncbi.nlm.nih.gov/tools/primer-blast/index.cgi?LINK_LOC=BlastHome).
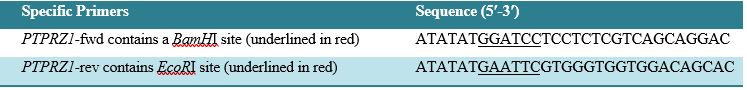
The forward primer contained a BamHI restriction site, whereas the reverse primer contained an EcoRӀ site. Table 1 indicates the primer sequences that were used in this study.
Table 1. Primer sequences and cleavage sites of the restriction endonucleases.
2.4 Preparation of competent cells
Competent E. coli DH5α cells were generated by inoculating the strain into LB medium lacking antibiotics overnight (12 -16 h).
The cells were inoculated in to fresh LB medium and allowed to grow until the OD600 reached 0.4. The culture was then transferred into a sterile, pre-chilled 50-mL centrifuge tube and centrifuged at 4000 rpm for 5 minutes at 4°C. The supernatant was discarded, and the cell pellets
were gently resuspended in 10 mL of cold, sterile TFB1 transformation buffer.
The suspension was centrifuged again under the same conditions. Subsequently, the pellet was resuspended in 1 mL of cold, sterile TFB2 buffer. The cell suspension was incubated in an ice-water bath for 15 minutes and then aliquoted into 1.5-mL microcentrifuge tubes at 1,000 µL per tube. The competent cells were stored at −70°C until further use.
2.5 Preparation of vector and insert DNA
Plasmid DNA with the template (pET28a-IL13-TNC-PTPRZ1) was isolated from E. coli (DH5α) using the alkaline lysis method. The PTPRZ1 gene was PCR-amplified with Pfu DNA polymerase. The PCR program began with denaturation at 94°C for 5 minutes, followed by 30 cycles of 94°C for 20 seconds, 64°C for 20 seconds, and 72°C for 45 seconds.
A final extension was done at 72°C for 15 minutes. PCR products were analyzed on an agarose gel and purified with a commercial gel extraction kit. DNA fragments were purified from agarose gels through the Addbio® (Korea) kit, following the manufacturer’s instructions. The pET28a-Fc plasmid was also extracted from DH5α using the alkaline lysis method. This plasmid was double-digested with EcoRI and BamHI, then purified by gel extraction and confirmed by agarose gel electrophoresis.
2.6 Ligation and Transformation into E. coli DH5α
Specifically, the PCR-amplified PTPRZ1 fragment and the pET28a-Fc vector were digested with BamHI and EcoRI at 37 °C for 2 hours. Subsequently, the reaction products were purified using a DNA clean-up kit. The insert was then ligated into the vector with T4 DNA ligase at 16 - 22 °C for 2 hours to generate pET28a-Fc-PTPRZ1. After ligation, the mixture was introduced into competent E. coli DH5α cells using the standard heat-shock method. Positive clones were identified by colony PCR with T7 primers and confirmed by restriction digestion analysis.
2.7 Transformation and Expression of Recombinant Protein in E. coli BL21 (DE3)
The recombinant plasmid pET28a-Fc-PTPRZ1 was transformed into E. coli BL21 (DE3) competent cells.
Colonies were cultured in 5 mL of LB broth supplemented with 50 μg/mL kanamycin at 37°C with shaking at 140 rpm until the culture reached an OD₆₀₀ of 0.6.
Protein expression was induced by adding 1 mM IPTG (Isopropyl β-d-1-thiogalactopyranoside) at 37 °C. Cultures were collected at 2, 4, and overnight post-induction, centrifuged at 12,000 rpm for 1 minute, and pellets were stored at −20 °C for later use.
2.8 Protein Purification
The bacterial cells were lysed by sonication at 100% amplitude for 1 second at 2-second intervals, for a total of 3 minutes. After that, the lysate was centrifuged at 13000 rpm and 4°C for 20 minutes. The resulting protein-enriched lysate was then subjected to denaturing purification using Ni-NTA affinity chromatography. To achieve effective extraction, the sample was dissolved in a buffer containing 8 M urea at pH 7.8, then loaded onto the chromatography column. The Fc–PTPRZ1 recombinant protein was eluted in 30 mM and 300 mM imidazole solutions. The fractions were collected and passed through a 0.22-μm-diameter nitrocellulose membrane. Finally, dialysis was used overnight in PBS buffer (pH 7.5) at 4 °C to remove any remaining imidazole and other impurities (17).
2.9 SDS-PAGE protein expression
Recombinant protein expression was evaluated in E. coli BL21 (DE3) using SDS-PAGE with a 12% separating gel. Samples were electrophoresed at 120 V for 120 minutes. The gel was stained with Coomassie Brilliant Blue R-250.
2.10 Western blot analysis
For Western blot analysis, SDS-PAGE was performed for protein separation. Then, the obtained unstained gel was transferred to a PVDF membrane at 100 V for 2 hours. We blocked the membrane with 5% skim milk in Tris-buffered saline (TBS), then incubated it with anti-His tag antibody (Sigma-Aldrich, St. Louis, MO, USA) for 2 hours at 37 °C with gentle shaking. Next, we washed the membrane three times with TBS-Tween (TBST) and incubated it with a horseradish peroxidase (HRP)-conjugated secondary antibody. After more washes with TBST to remove unbound antibodies, obtained PVDF membrane was treated using an HRP substrate solution containing 3, 3′-diaminobenzidine (DAB) and 30% hydrogen peroxide (H₂O₂). To stop the reaction, the membrane was washed three times with distilled water (17).
2.11 Bradford Assay
The concentration of the purified recombinant protein was measured using the Bradford colorimetric assay. A standard curve was generated using bovine serum albumin (BSA) at concentrations ranging from 0 to 20 µg/mL, and absorbance values were recorded at 595 nm. The protein concentration in the eluted fractions was measured using the standard curve.
All concentration measurements were performed three times to ensure reproducibility and improve data accuracy.
3. Result
3.1 Extraction of pET28a-IL13-TNC-PTPRZ1 Plasmid and PCR Amplification of PTPRZ1
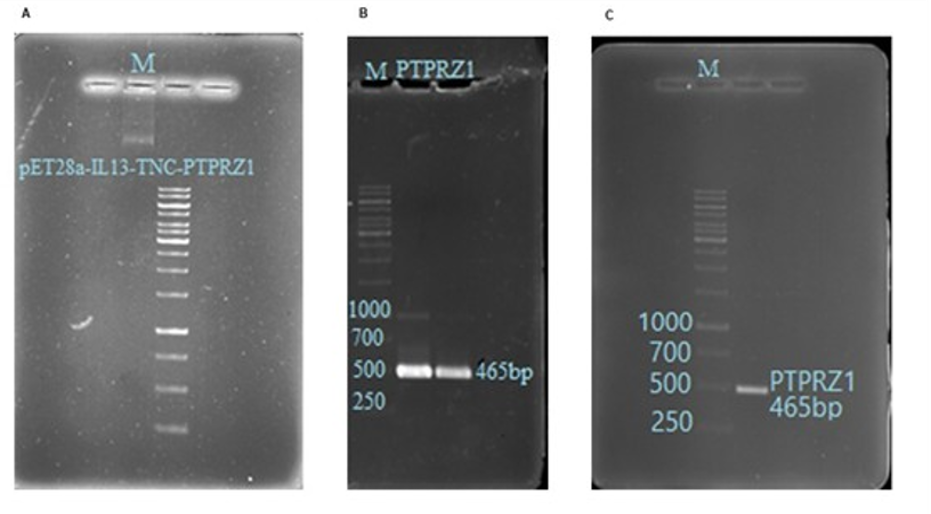
Plasmid pET28a-IL13-TNC-PTPRZ1 was efficiently extracted from E. coli DH5α using the alkaline lysis method, and the expected plasmid band was observed on a 1% agarose gel (Figure 1A).
In the present study, only the PTPRZ1 gene was specifically amplified from this plasmid and subsequently cloned into the pET28a-Fc vector. PCR amplification yielded a 465 bp fragment corresponding to the PTPRZ1 gene, as shown in Figure 1B, and this was confirmed by agarose gel electrophoresis. The PCR product was then purified using a gel recovery kit (Figure 1C).
Figure 1. Extraction and PCR amplification of the PTPRZ1 fragment. (A) Agarose gel image of pET28a-IL13-TNC-PTPRZ1 fragment extracted by the alkaline lysis method from E. coli (DH5α). (B) Amplification of 465bp of the PTRZ1 fragment using Pfu DNA Polymerase (C) Gel Recovery of PCR Product. Lanes M are the size markers (1 kb DNA ladder, SINACLON Co., Cat No: SL7051). (Prepared by Authors, 2026).
3.2 Restriction Enzyme Digestion and Ligation
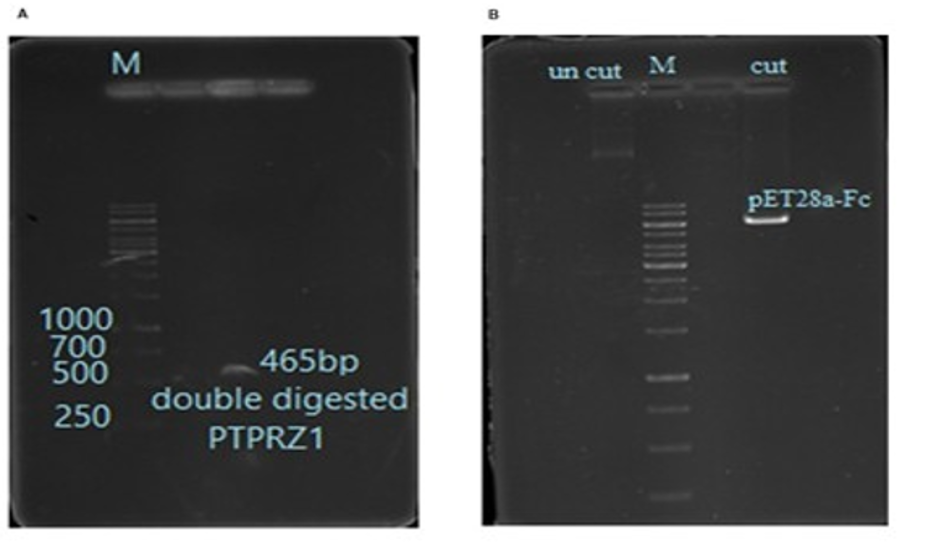
Double digestion of the PTPRZ1 fragment was performed using BamH1 and EcoR1 restriction enzymes to achieve sticky ends, resulting in a band of ~465 bp as expected (Figure 2A). The pET28a-Fc plasmid was also digested with the same enzymes (Figure 2B).
Both the insert and vector were purified, and the ligation reaction was performed using T4 DNA ligase, yielding the recombinant construct pET28a-Fc-PTPRZ1.
Double digestion of the PTPRZ1 fragment was performed using BamH1 and EcoR1 restriction enzymes to achieve sticky ends, resulting in a band of ~465 bp as expected (Figure 2A). The pET28a-Fc plasmid was also digested with the same enzymes (Figure 2B).
Both the insert and vector were purified, and the ligation reaction was performed using T4 DNA ligase, yielding the recombinant construct pET28a-Fc-PTPRZ1.
Figure 2. Restriction digestion of the PTPRZ1 insert and pET28a-Fc vector. (A) Agarose gel (1%) analysis of the digested PTPRZ1 Fragment. (B) Double digestion of pET28a-Fc plasmid with BamHI and EcoRI, showing linearized plasmid and uncut control. Lane M: 1 kb DNA ladder, SINACLON Co., Cat No: SL7051). (Prepared by Authors, 2026).
3.3 Colony PCR of E. coli DH5α Transformants
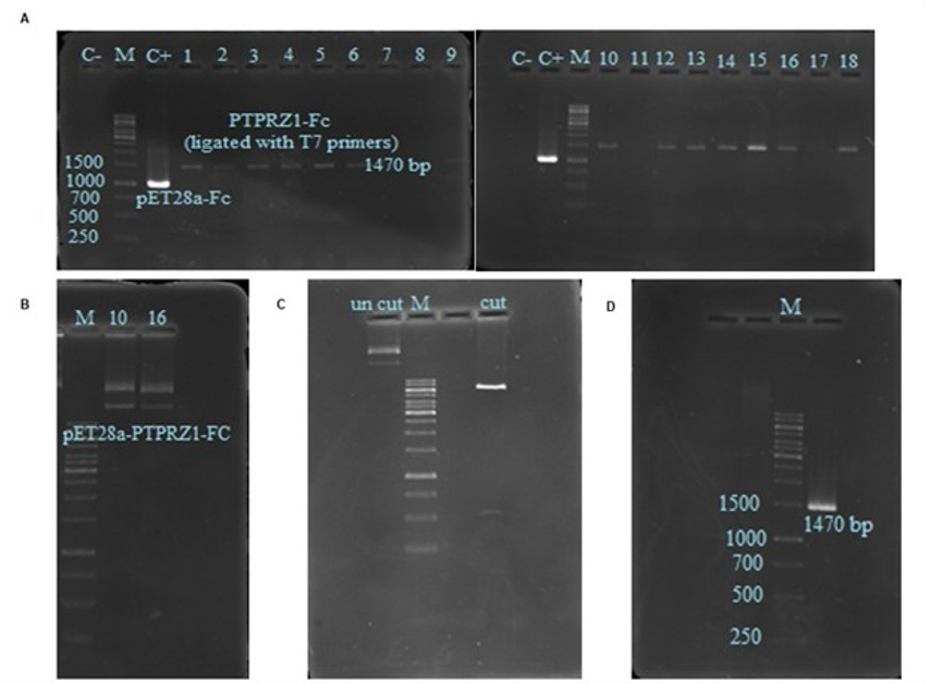
Colony PCR was performed on 18 transformants of E. coli DH5α containing the ligation product. A band of approximately 1470 bp was obtained in multiple colonies, affirming the correct insertion of PTPRZ1 into the pET28a-Fc vector (Figure 3A).
Colonies 10 and 16 were selected for further validation. Plasmid extraction followed by restriction digestion confirmed the presence of the insert (Figures 3B and 3C). Additionally, PCR analysis using T7 primers verified the correct construct size (Figure 3D).
Colony PCR was performed on 18 transformants of E. coli DH5α containing the ligation product. A band of approximately 1470 bp was obtained in multiple colonies, affirming the correct insertion of PTPRZ1 into the pET28a-Fc vector (Figure 3A).
Colonies 10 and 16 were selected for further validation. Plasmid extraction followed by restriction digestion confirmed the presence of the insert (Figures 3B and 3C). Additionally, PCR analysis using T7 primers verified the correct construct size (Figure 3D).
Figure 3. Colony PCR and validation of recombinant pET28a-Fc-PTPRZ1 in E. coli DH5α. (A) Colony PCR of 18 randomly selected colonies using T7 primers. Positive colonies showed a band at ~1470 bp. (B) Plasmid DNA was extracted from positive colonies (10 and 16). (C) Restriction digestion analysis of pET28a-Fc-PTPRZ1, confirming the presence of the insert. (D) PCR confirmation of recombinant plasmid using T7 primers, showing the expected 1470 bp product. Lane M: 1 kb DNA ladder, SINACLON Co., Cat No: SL7051). (Prepared by Authors, 2026).
3.4 Colony PCR of BL21 (DE3) Transformants
The recombinant pET28a-Fc-PTPRZ1 plasmid was transformed into E. coli BL21 (DE3). Analysis of the resulting transformants using colony PCR revealed the expected 1470 bp band on a 1% agarose gel. Colonies 3, 4, and 5 were chosen for further protein expression studies.
3.5 Protein Expression and Purification
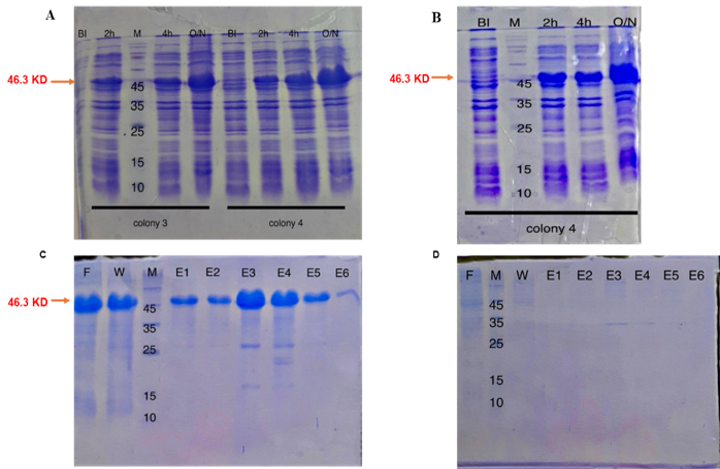
Recombinant protein expression in E. coli BL21 (DE3) was triggered by adding 1 mM IPTG, and samples were collected at 2 h, 4 h, and overnight post-induction. SDS-PAGE analysis demonstrated a clear band of approximately 46.3 kDa, corresponding to the predicted size of the Fc-PTPRZ1 fusion protein (Figures 4A and 4B). Protein purification was performed under both native and denaturing conditions using Ni-NTA affinity chromatography. The recombinant protein was efficiently purified under denaturing conditions in the insoluble fraction (Figure 4C), whereas no band was identified in the soluble fraction (Figure 4D). These findings confirmed that Fc-PTPRZ1 was expressed predominantly as inclusion bodies.
The recombinant pET28a-Fc-PTPRZ1 plasmid was transformed into E. coli BL21 (DE3). Analysis of the resulting transformants using colony PCR revealed the expected 1470 bp band on a 1% agarose gel. Colonies 3, 4, and 5 were chosen for further protein expression studies.
3.5 Protein Expression and Purification
Recombinant protein expression in E. coli BL21 (DE3) was triggered by adding 1 mM IPTG, and samples were collected at 2 h, 4 h, and overnight post-induction. SDS-PAGE analysis demonstrated a clear band of approximately 46.3 kDa, corresponding to the predicted size of the Fc-PTPRZ1 fusion protein (Figures 4A and 4B). Protein purification was performed under both native and denaturing conditions using Ni-NTA affinity chromatography. The recombinant protein was efficiently purified under denaturing conditions in the insoluble fraction (Figure 4C), whereas no band was identified in the soluble fraction (Figure 4D). These findings confirmed that Fc-PTPRZ1 was expressed predominantly as inclusion bodies.
Figure 4. SDS-PAGE analysis and purification of recombinant Fc-PTPRZ1 protein. (A) SDS-PAGE analysis was performed to evaluate the expression of the recombinant protein in LB broth. Lane 1 represents the cell lysate before induction with IPTG. Lane 2 shows the cell lysate after two hours of induction with 1 mM IPTG. Lane 3 corresponds to the molecular weight marker. Lane 4 represents the cell lysate after four hours of induction with 1 mM IPTG. Lane 5 displays the cell lysate after overnight induction with 1 mM IPTG from colony 3. Lanes 6 to 9 show cell lysates from colony 4, both before and after induction with 1 mM IPTG for 2 hours, 4 hours, and overnight, respectively. (B) SDS-PAGE analysis of recombinant protein expression from colony 5. Lane 1 shows the cell lysate before induction with IPTG. Lane 2 is the molecular weight marker. Lanes 3 and 4 represent the cell lysates after two- and four-hour induction with 1 mM IPTG, respectively. Lane 5 shows the cell lysate after overnight induction with 1 mM IPTG. (C) Flow-through and wash fractions (20–30 mM imidazole) showed no significant target protein, confirming the removal of non-specific proteins. The elution fractions with 300 mM imidazole contained a distinct band at ~46.3 kDa representing purified Fc-PTPRZ1. (D) No detectable band was observed in the soluble fraction, confirming that expression occurred in the insoluble phase. BI: before injection, O/N: overnight, F: flow. W: wash, E: elution, Lane M: 1 kb DNA ladder, SINACLON Co., Cat No: SL7051). (Prepared by Authors, 2026).
3.6 Western Blotting Assay
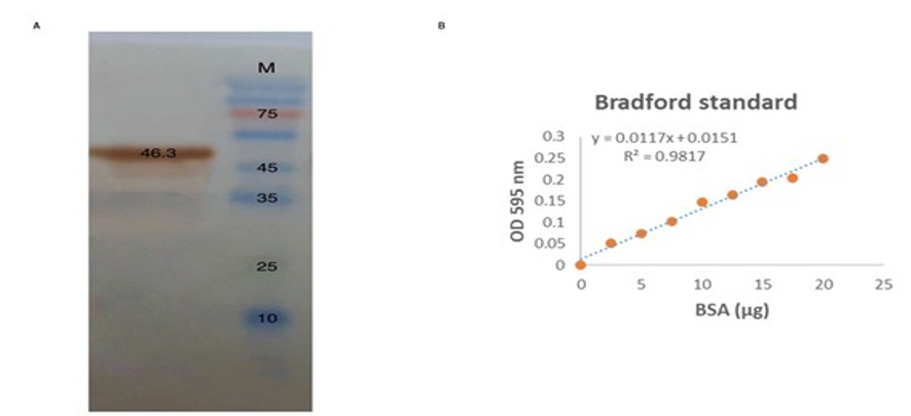
Western blot analysis confirmed successful expression of the recombinant Fc-PTPRZ1 protein, as indicated by a band at ~46.3 kDa with an anti-His antibody (Figure 5A).
3.7 Protein Quantification by Bradford Assay
The concentration of purified Fc-PTPRZ1 protein was determined using the Bradford assay (18). A standard curve prepared with BSA demonstrated high linearity (R² = 0.98). Based on triplicate measurements, the average concentration of purified protein was approximately 700 μg/mL (Figure 5B).
Western blot analysis confirmed successful expression of the recombinant Fc-PTPRZ1 protein, as indicated by a band at ~46.3 kDa with an anti-His antibody (Figure 5A).
3.7 Protein Quantification by Bradford Assay
The concentration of purified Fc-PTPRZ1 protein was determined using the Bradford assay (18). A standard curve prepared with BSA demonstrated high linearity (R² = 0.98). Based on triplicate measurements, the average concentration of purified protein was approximately 700 μg/mL (Figure 5B).
Figure 5. Western blot and Bradford assay of recombinant Fc-PTPRZ1. (A) Western blot analysis detecting recombinant Fc-PTPRZ1 protein at ~46.3 kDa using an anti-His antibody. Lane M: protein marker (SINACLON Co., Cat No: SL7013). (B) Bradford assay standard curve using BSA. The concentration of purified protein was estimated at ~700 μg/mL (mean of three replicates, R² = 0.98). The X-axis shows protein concentration, and the Y-axis indicates the OD value obtained at a wavelength of 595 nm. (Prepared by Authors, 2026).
4. Discussion
The Fc-PTPRZ1 fusion protein was successfully cloned into the Fc-pET28a vector, expressed in E. coli BL21 (DE3), and purified using Ni-NTA affinity chromatography. The recombinant protein was analyzed by SDS-PAGE, which showed a major band at approximately 46.3 kDa. Subsequent Western blotting analysis confirmed successful expression of the purified recombinant protein at the same apparent molecular weight. Bradford assay was used to quantify the purified protein, and the concentration was estimated to be about 700 µg/mL, with high reproducibility across three replicates (R² ≈ 0.98). (The final constructed plasmid map along with information about the fusion protein sequence). A remarkable observation was that the recombinant protein was highly localized to insoluble inclusion bodies,a major limitation to expressing eukaryotic proteins in a prokaryotic expression system. This finding supports the inability of the bacterial system to provide the necessary molecular machinery to support the proper folding of various proteins and their interactions, ultimately leading to the formation of insoluble inclusion bodies due to aggregation. Even after decades of research and creation of advanced treatment modalities, GBM remains a deadly disease, and the median overall survival is less than two years. Recent developments in immunotherapy have renewed interest in using immune-based strategies for cancer treatment (19). Different vaccination approaches for treating GBM use DNA, RNA, or peptides as antigens. Carriers such as dendritic cells (DCs) and heat-shock proteins are used to administer these vaccines via intravenous, intranodal, intradermal, or intramuscular injections (20).
The PTPRZ1 gene encodes receptor-type tyrosine-protein phosphatase zeta, a member of the R5 subfamily of the receptor tyrosine phosphatase family. (1). There are three known splice variants of PTPRZ1, including PTPRZ-A (9.4 kb, full-length transmembrane receptor), PTPRZ-B (6.4 kb, shorter transmembrane variant with deletion in the extracellular region compared to PTPRZ-A), and PTPRZ-S or 6B4 proteoglycan/phosphacan (secretory variant of PTPRZ-A) (21).
The first study to describe a possible relationship between PTPRZ1 and malignant growth found that PTPRZ1 expression in lung adenocarcinomas was reduced relative to normal lung tissue, suggesting a potential role for PTPRZ1 as a tumor suppressor (22). Other reports demonstrate that PTPRZ has an oncogenic effect (12, 19, 20), and its activation promotes tumor growth and migration of tumor cells (23, 24). It also stimulates glioma stem cells (GSCs) to maintain tumorigenicity, contributing to tumor initiation and progression (1, 21, 25, 26). These findings indicate that PTPRZ1 is among the most promising tumor-related antigens for developing glioblastoma immunotherapies, including peptide- and protein-based vaccines. The production of tumor antigens such as PTPRZ1 in E. coli is a rapid, cost-efficient platform for recombinant protein production, simplifying preclinical immunotherapeutic studies and providing a pathway to future applications as a potential diagnostic biomarker and therapeutic target in glioblastoma.
Although expression of soluble proteins in E. coli is frequently clear, major challenges are encountered with many heterologous proteins, particularly those lakingk relevant interaction partners in the bacterial cytoplasm. These proteins regularly shape insoluble aggregates known as inclusion bodies, which complicate downstream processing and decrease the yield of active protein. The use of fusion partners has been developed to extend the solubility, stability, or expression levels of heterologous proteins in E. coli (27).
PTPRZ is a heavily glycosylated membrane protein. It displays special glycosylation features, such as the attachment of chondroitin sulfate chains and branched O-mannosyl (Man) glycans. Compared with normal brain tissues, gliomas express intensely glycosylated forms of PTPRZ. These glycosyl alterations can together affect tumor cell development in gliomas (1). However, E. coli lacks the cellular machinery needed for post-translational glycosylation. This modification is required for protein folding and function in eukaryotic cells (28). As a result, expressing PTPRZ1 in E. coli may limit its full functionality, which is crucial for therapeutic applications.
To compensate for this confinement, Fc-fusion proteins are regularly utilized. These proteins incorporate the IgG Fc domain, which folds independently, contributes to structural stability, and empowers favorable expression and purification (29, 30). This fusion also prolongs serum half-life by rescuing fusion proteins from lysosomal degradation through neonatal Fc receptor (FcRn) mediated recycling (31). In recent years, Fc fusion protein implementation in immunotherapeutic treatments, and more specifically in the context of oncological interventions, has been widely discussed (32, 33). Asunercept is a novel recombinant glycosylated fusion protein that consists of the extracellular region of human CD95 connected to the Fc part of human IgG. This Fc fusion protein specifically binds to CD95L, disrupting CD95/CD95L signaling, which may inhibit glioblastoma progression by interfering with tumor-promoting and immune-evasive pathways (12). Mahmud et al. (34) developed a chlorotoxin peptide fused to the human IgG Fc region lacking the hinge sequence (M-CTX-Fc), which appeared to have a greater growth-inhibitory effect on the glioblastoma cell line A172 compared to the original chlorotoxin peptide. Beffinger et al. (14) designed an IL-12Fc fusion cytokine with a reduced affinity towards FcRn. By specifically inhibiting FcRn, the IL-12Fc fusion protein blocks FcRn-mediated brain export through the blood-brain barrier, thereby enhancing cerebral retention, reducing blood levels, and preventing toxicity.
Although our study focused on the Fc-PTPRZ1 recombinant protein, previous studies have reported PTPRZ1-MET fusions in gliomas (35). These findings emphasize the central role of PTPRZ1 in glioblastoma biology and support its selection as a promising immunotherapy target. Dutoit et al. (36) reported that the PTPRZ1₁₉₅–₂₀₃ and PTPRZ1₁₃₄₇–₁₃₅₅ peptides, which are derived from PTPRZ1, are naturally processed and presented on tumor cell surfaces in WHO grade II and III gliomas. These include astrocytomas and oligodendrogliomas. In addition, spontaneous CD8⁺ T-cells targeting these epitopes were reported in a subset of patients. These findings prove that the immune system can identify PTPRZ1 as a tumor antigen and provide strong evidence of the use of PTPRZ1-derived antigens as immunotherapy against glioblastoma.
The goal of immunotherapeutic strategies is to redirect immune cells toward targeting the tumor by harnessing the immune system of the patient. Numerous immunotherapies, such as immune checkpoint inhibitors (ICIs) and chimeric antigen receptor (CAR) T-cell therapy, have demonstrated significant potential in other aggressive malignancies and are currently being explored as therapeutic options in glioblastoma (37). However, so far, peptide vaccines have not shown a statistically significant clinical advantage in GBM patients, which can be partly explained by the instability of the peptides and by their poor immunogenicity (19). Generally, five major peptide vaccines aimed at GBM are currently being examined in different clinical trials, including rindopepimut, Sur VaxM, IMA950, heat shock protein–peptide complexes 96 (HSPPC-96)-specific vaccine, and personalized neoantigen vaccines (20). The preclinical and early-phase clinical trials have shown that these immunotherapeutic approaches can induce both innate and adaptive immune responses, convert immune-cold tumors into immunologically active (hot) tumors, cross the blood-brain barrier, and, in some specific cases, provide a survival benefit to patients (38).
In our study, given the noteworthy role of PTPRZ1 in GBM aggressiveness and signaling, a fusion construct containing the PTPRZ1 antigen with the Fc domain was designed and expressed to enhance its solubility and stability, aiming to improve its uptake by antigen-presenting cells via Fc receptor-mediated endocytosis, boost immunogenicity, and eventually focus on glioblastoma immunotherapy and future vaccine development. The current study has indicated that the recombinant protein was predominantly separated in the insoluble fraction. However, the lack of post-translational changes, including glycosylation, may hinder some of its biological functions. It is worth noting that no functional or in vivo experiments were done to assess the immunogenicity or therapeutic efficacy of the recombinant protein. Subsequent in vivo studies should be done to determine the immunogenicity and efficacy of the recombinant Fc-PTPRZ1 in animal models of glioblastoma, such as murine GL26 glioma-bearing mice. Quantitative and qualitative analysis of the antibody response against the recombinant protein using traditional immunoassays, such as ELISA, would help explain the immunogenic potential of the vaccine. Additionally, to enhance solubility and maximize expression of recombinant proteins, SUMO (Small Ubiquitin-like Modifier) tags should be considered in future constructions.
5. Conclusion
Together, our data indicate the possibility of producing of Fc-PTPRZ1 at moderate yields in E. coli.
Also, to prove the immunogenicity and therapeutic efficacy of Fc-PTPRZ1 in glioblastoma models, extensive preclinical in vivo studies will be necessary.
Moreover, preclinical studies are needed to evaluate the safety profile of Fc-PTPRZ1 and investigate its potential off-target effects and immune-mediated reactions. Such studies are essential to assess its therapeutic feasibility and ensure patient safety (30).
6. Declarations
6.1 Acknowledgments
The authors would like to thank the School of Pharmacy, Zanjan University of Medical Sciences, Zanjan, Iran. This study was conducted under project code A-12-848-43.
6.2 Ethical Considerations
This study received approval from the Ethics Committee of Zanjan University of Medical Sciences, Zanjan, Iran (approval code: IR.ZUMS.BLC.1402.062).
6.3 Authors' Contributions
ASH: Conceptualization, methodology, supervision, writing, editing; ZH: Investigation, laboratory techniques, interpretation of data, validation; TT: Investigation, data curation, writing original draft; NMP: Investigation, interpretation of data for the work, writing and revising; All authors contributed to data interpretation and approved the final manuscript for publication.
6.4 Conflict of Interest
The authors declare no conflict of interest.
6.5 Fund or Financial Support
The authors received no financial support or funding for this study.
6.6 Using Artificial Intelligence Tools (AI Tools)
The authors utilized Grammarly solely for language polishing, proofreading, and minor grammatical corrections. No generative AI tools were employed for data analysis, content generation, or scientific writing.
Type of Study: Original Research Article |
Subject:
Life Science
Received: 2026/02/21 | Accepted: 2026/06/2 | Published: 2026/06/29
Received: 2026/02/21 | Accepted: 2026/06/2 | Published: 2026/06/29
References
1. Nagai K, Fujii M, Kitazume S. Protein tyrosine phosphatase receptor type Z in central nervous system disease. Int J Mol Sci. 2022;23(8):4414. [DOI:10.3390/ijms23084414] [PMID] [PMCID]
2. Zhang H, Wang Z, Qiao X, Wu J, Cheng C. Investigating potential drug targets for the treatment of glioblastoma: a Mendelian randomization study. BMC cancer. 2025;25(1):654. [DOI:10.1186/s12885-025-13979-3] [PMID] [PMCID]
3. Grzegorzewski J, Michalak M, Wołoszczuk M, Bulicz M, Majchrzak-Celińska A. Nanotherapy of glioblastoma-Where hope grows. Int J Mol Sci. 2025;26(5):1814. [DOI:10.3390/ijms26051814] [PMID] [PMCID]
4. Sipos D, Raposa BL, Freihat O, Simon M, Mekis N, Cornacchione P, et al. Glioblastoma: Clinical presentation, multidisciplinary management, and long-term outcomes. Cancers. 2025;17(1):146. [DOI:10.3390/cancers17010146] [PMID] [PMCID]
5. Patel V, Chavda V. Intraoperative glioblastoma surgery-current challenges and clinical trials: An update. Cancer Pathog Ther. 2024;2(04):256-67. [DOI:10.1016/j.cpt.2023.11.006] [PMID] [PMCID]
6. Cruz JVR, Batista C, Afonso BdH, Alexandre-Moreira MS, Dubois LG, Pontes B, et al. Obstacles to glioblastoma treatment two decades after temozolomide. Cancers. 2022;14(13):3203. [DOI:10.3390/cancers14133203] [PMID] [PMCID]
7. Huang B, Li X, Li Y, Zhang J, Zong Z, Zhang H. Current immunotherapies for glioblastoma multiforme. Front Immunol. 2021;11:603911. [DOI:10.3389/fimmu.2020.603911] [PMID] [PMCID]
8. Sener U, Ruff MW, Campian JL. Immunotherapy in glioblastoma: current approaches and future perspectives. Int J Mol Sci. 2022;23(13):7046. [DOI:10.3390/ijms23137046] [PMID] [PMCID]
9. Zhao B, Wu J, Li H, Wang Y, Wang Y, Xing H, et al. Recent advances and future challenges of tumor vaccination therapy for recurrent glioblastoma. Cell Commun. Signal. 2023;21(1):74. [DOI:10.1186/s12964-023-01098-0] [PMID] [PMCID]
10. Strohl WR. Fusion proteins for half-life extension of biologics as a strategy to make biobetters. Bio Drugs. 2015;29(4):215-39. [DOI:10.1007/s40259-015-0133-6] [PMID] [PMCID]
11. Czajkowsky DM, Hu J, Shao Z, Pleass RJ. Fc‐fusion proteins: new developments and future perspectives. EMBO Mol Med. 2012;4(10):1015-28. [DOI:10.1002/emmm.201201379] [PMID] [PMCID]
12. Krendyukov A, Gieffers C. Asunercept as an innovative therapeutic approach for recurrent glioblastoma and other malignancies. Cancer Manag Res. 2019:8095-100. [DOI:10.2147/CMAR.S216675] [PMID] [PMCID]
13. El-Ghlban S, Kasai T, Shigehiro T, Yin HX, Sekhar S, Ida M, et al. Chlorotoxin‐Fc fusion inhibits release of MMP‐2 from pancreatic cancer cells. Bio Med Res Int. 2014;2014(1):152659. [DOI:10.1155/2014/152659] [PMID] [PMCID]
14. Beffinger M, Schellhammer L, Taskoparan B, Deplazes S, Salazar U, Tatari N, et al. FcRn-silencing of IL-12Fc prevents toxicity of local IL-12 therapy and prolongs survival in experimental glioblastoma. Nat Commun. 2025;16(1):4751. [DOI:10.1038/s41467-025-59971-0] [PMID] [PMCID]
15. Müller S, Kunkel P, Lamszus K, Ulbricht U, Lorente GA, Nelson AM, et al. A role for receptor tyrosine phosphataseζ in glioma cell migration. Oncogene. 2003;22(43):6661-8. [DOI:10.1038/sj.onc.1206763] [PMID]
16. Ulbricht U, Brockmann MA, Aigner A, Eckerich C, Müller S, Fillbrandt R, et al. Expression and function of the receptor protein tyrosine phosphatase ζ and its ligand pleiotrophin in human astrocytomas. J Neuropathol Exp Neurol. 2003;62(12):1265-75. [DOI:10.1093/jnen/62.12.1265] [PMID]
17. Gharbavi M, Danafar H, Amani J, Sharafi A. Immuno-informatics analysis and expression of a novel multi-domain antigen as a vaccine candidate against glioblastoma. Int Immunopharmacol. 2021;91:107265. [DOI:10.1016/j.intimp.2020.107265] [PMID] [PMCID]
18. Kruger NJ. The Bradford method for protein quantitation. The protein protocols handbook. 2009:17-24. [DOI:10.1007/978-1-59745-198-7_4]
19. Salvato I, Marchini A. Immunotherapeutic strategies for the treatment of glioblastoma: current challenges and future perspectives. Cancers. 2024;16(7):1276. [DOI:10.3390/cancers16071276] [PMID] [PMCID]
20. Frederico SC, Hancock JC, Brettschneider EE, Ratnam NM, Gilbert MR, Terabe M. Making a cold tumor hot: the role of vaccines in the treatment of glioblastoma. Front. Oncol. 2021;11:672508. [DOI:10.3389/fonc.2021.672508] [PMID] [PMCID]
21. Fujikawa A, Sugawara H, Tanaka T, Matsumoto M, Kuboyama K, Suzuki R, et al. Targeting PTPRZ inhibits stem cell-like properties and tumorigenicity in glioblastoma cells. Sci. Rep. 2017;7(1):5609. [DOI:10.1038/s41598-017-05931-8] [PMID] [PMCID]
22. Gaits F, Li R, Ragab A, Selves J, Ragab-Thomas J, Chap H. Implication of a protein-tyrosine-phosphatase in human lung cancer. Cell Mol Biol. (Noisy-le-Grand, France). 1994;40(5):677-85.
23. Fujikawa A, Nagahira A, Sugawara H, Ishii K, Imajo S, Matsumoto M, et al. Small-molecule inhibition of PTPRZ reduces tumor growth in a rat model of glioblastoma. Sci Rep. 2016;6(1):20473. [DOI:10.1038/srep20473] [PMID] [PMCID]
24. Ulbricht U, Eckerich C, Fillbrandt R, Westphal M, Lamszus K. RNA interference targeting protein tyrosine phosphatase ζ/receptor‐type protein tyrosine phosphatase β suppresses glioblastoma growth in vitro and in vivo. J Neurochem. 2006;98(5):1497-506. [DOI:10.1111/j.1471-4159.2006.04022.x] [PMID]
25. Shi Y, Ping YF, Zhou W, He ZC, Chen C, Bian BS-J, et al. Tumour-associated macrophages secrete pleiotrophin to promote PTPRZ1 signalling in glioblastoma stem cells for tumour growth. Nat Commun. 2017;8(1):15080. [DOI:10.1038/ncomms15080] [PMID] [PMCID]
26. Qin EY, Cooper DD, Abbott KL, Lennon J, Nagaraja S, Mackay A, et al. Neural precursor-derived pleiotrophin mediates subventricular zone invasion by glioma. Cell. 2017;170(5):845-59. e19. [DOI:10.1016/j.cell.2017.07.016] [PMID] [PMCID]
27. Sørensen HP, Mortensen KK. Advanced genetic strategies for recombinant protein expression in Escherichia coli. J Biotechnol. 2005;115(2):113-28. [DOI:10.1016/j.jbiotec.2004.08.004] [PMID]
28. Rosano GL, Ceccarelli EA. Recombinant protein expression in Escherichia coli: advances and challenges. Front Microbiol. 2014;5:172. [DOI:10.3389/fmicb.2014.00172]
29. Huang C. Receptor-Fc fusion therapeutics, traps, and MIMETIBODY™ technology. Curr Opin Biotechnol. 2009;20(6):692-9. [DOI:10.1016/j.copbio.2009.10.010] [PMID]
30. Hirasawa S, Kitahara Y, Okamatsu Y, Fujii T, Nakayama A, Ueno S, et al. Facile and efficient chemoenzymatic semisynthesis of Fc-fusion compounds for half-life extension of pharmaceutical components. Bioconjug Chem. 2019;30(9):2323-31. [DOI:10.1021/acs.bioconjchem.9b00235] [PMID]
31. Rath T, Baker K, Dumont JA, Peters RT, Jiang H, Qiao SW, et al. Fc-fusion proteins and FcRn: structural insights for longer-lasting and more effective therapeutics. Crit Rev Biotechnol. 2015;35(2):235-54. [DOI:10.3109/07388551.2013.834293] [PMID] [PMCID]
32. Alleva DG, Delpero AR, Scully MM, Murikipudi S, Ragupathy R, Greaves EK, et al. Development of an IgG-Fc fusion COVID-19 subunit vaccine, AKS-452. Vaccine. 2021;39(45):6601-13. [DOI:10.1016/j.vaccine.2021.09.077] [PMID] [PMCID]
33. Niu YX, Xu ZX, Yu LF, Lu YP, Wang Y, Wu C, et al. Advances of research of Fc-fusion protein that activate NK cells for tumor immunotherapy. Int Immunopharmacol. 2022;109:108783. [DOI:10.1016/j.intimp.2022.108783] [PMID]
34. Mahmud H, Kasai T, Khayrani AC, Asakura M, Oo AKK, Du J, et al. Targeting glioblastoma cells expressing CD44 with liposomes encapsulating doxorubicin and displaying chlorotoxin-IgG Fc fusion protein. Int J Mol Sci. 2018;19(3):659. [DOI:10.3390/ijms19030659] [PMID] [PMCID]
35. Huang R, Liu Y, Wang K, Wang Z, Zhang C, Zhang W, et al. High‐sensitive clinical diagnostic method for PTPRZ1‐MET and the characteristic protein structure contributing to ligand‐independent MET activation. CNS Neurosci. 2021;27(5):617-28. [DOI:10.1111/cns.13627] [PMID] [PMCID]
36. Dutoit V, Migliorini D, Ranzanici G, Marinari E, Widmer V, Lobrinus JA, et al. Antigenic expression and spontaneous immune responses support the use of a selected peptide set from the IMA950 glioblastoma vaccine for immunotherapy of grade II and III glioma. Oncoimmunology. 2018;7(2):e1391972. [DOI:10.1080/2162402X.2017.1391972] [PMID] [PMCID]
37. Yu MW, Quail DF. Immunotherapy for glioblastoma: current progress and challenges. Front Immunol. 2021;12:676301. [DOI:10.3389/fimmu.2021.676301] [PMID] [PMCID]
38. Kong X, Ou S, Wei Z, Ye X, Chen S, Shi X, et al. Transforming the "cold" tumors to "hot" tumors: strategies for immune activation. Biochem Pharmacol. 2025:117194. [DOI:10.1016/j.bcp.2025.117194] [PMID]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |
Copyright Policy
Journal of Advances in Medical and Biomedical Research by Zanjan University of Medical Sciences is licensed under CC BY-NC 4.0