Fri, Sep 25, 2026
[Archive]
Volume 34, Issue 3 (May & June 2026)
J Adv Med Biomed Res 2026, 34(3): 238-250 |
Back to browse issues page



Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Zakeri S, Jafarian M, Alavi S, Rahmani S, Mortazavi Y. Assessment of TPMT Gene Polymorphisms and its Enzyme Activity in Pediatric Acute Lymphoblastic Leukemia Patients Receiving 6-Mercaptopurine: Correlation with Myelosuppression and Hepatotoxicity. J Adv Med Biomed Res 2026; 34 (3) :238-250
URL: http://journal.zums.ac.ir/article-1-7944-en.html
URL: http://journal.zums.ac.ir/article-1-7944-en.html


1- Department of Medical and Molecular Genetics, Nobel Pathobiology and Genetics Laboratory, Isfahan, Iran
2- Department of Molecular Medicine and Genetics, Faculty of Medicine, Zanjan University of Medical Sciences, Zanjan, Iran
3- Pediatric Conjenital Hematologic Disorders Research Center, Research Institute of Children's Health, Shahid Beheshti University of Medical Sciences, Tehran, Iran
4- Department of Medical Laboratory Sciences, School of Allied Medicine, Kermanshah University of Medical Sciences, Kermanshah, Iran
5- Department of Molecular Medicine and Genetics, Faculty of Medicine, Zanjan University of Medical Sciences, Zanjan, Iran ,yousef1mortazavi@gmail.com
2- Department of Molecular Medicine and Genetics, Faculty of Medicine, Zanjan University of Medical Sciences, Zanjan, Iran
3- Pediatric Conjenital Hematologic Disorders Research Center, Research Institute of Children's Health, Shahid Beheshti University of Medical Sciences, Tehran, Iran
4- Department of Medical Laboratory Sciences, School of Allied Medicine, Kermanshah University of Medical Sciences, Kermanshah, Iran
5- Department of Molecular Medicine and Genetics, Faculty of Medicine, Zanjan University of Medical Sciences, Zanjan, Iran ,
Keywords: Acute Lymphoblastic Leukemia, Thiopurine Methyltransferase, Polymorphism, Pharmacogenetics, 6-Mercaptopurine, Leukopenia
Full-Text [PDF 515 kb]
(65 Downloads)
| Abstract (HTML) (436 Views)
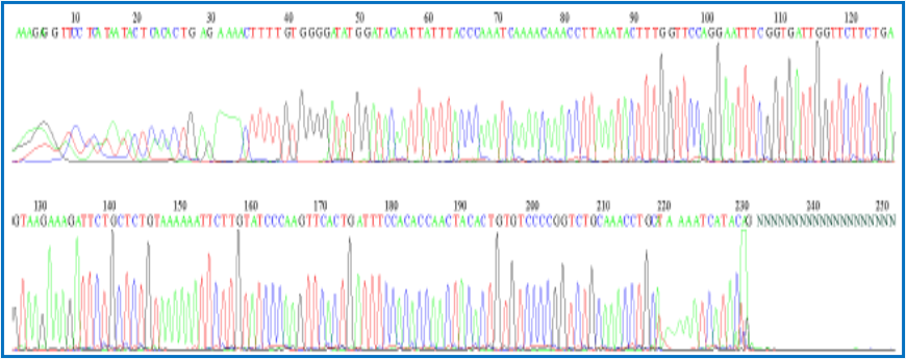
Figure 2. Sequencing results of the amplified fragment for analysis of the TPMT*2 polymorphism. (Prepared by Authors, 2026).
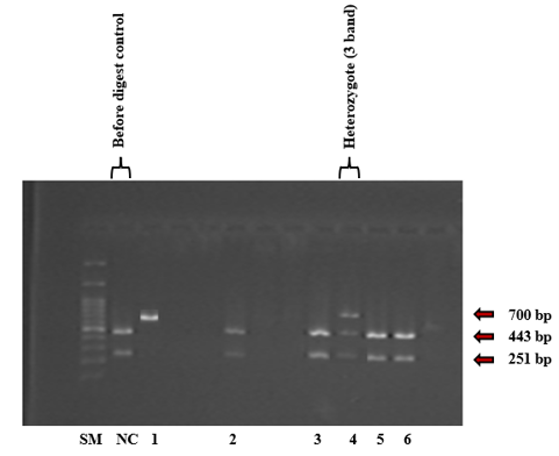
Figure 3. Electrophoresis of PCR products for TPMT*3B polymorphism, SM denotes the Size Marker. (Prepared by Authors, 2026).
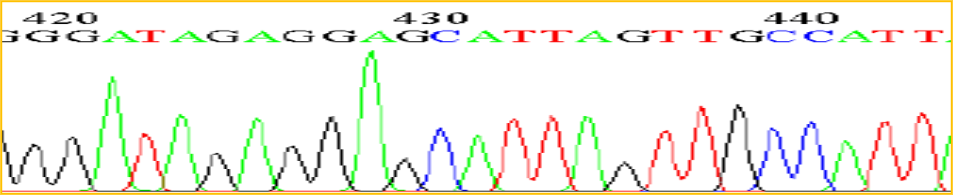
Figure 4. Sequence analysis of the TPMT*10 (430G>C) variant. The chromatogram demonstrates the presence of the wild-type G nucleotide at position 430, indicating the absence of the TPMT*10 (430G>C) variant. The corresponding sequence is GGGATAGAGGAGCATTAGTTGCC. (Prepared by Authors, 2026).
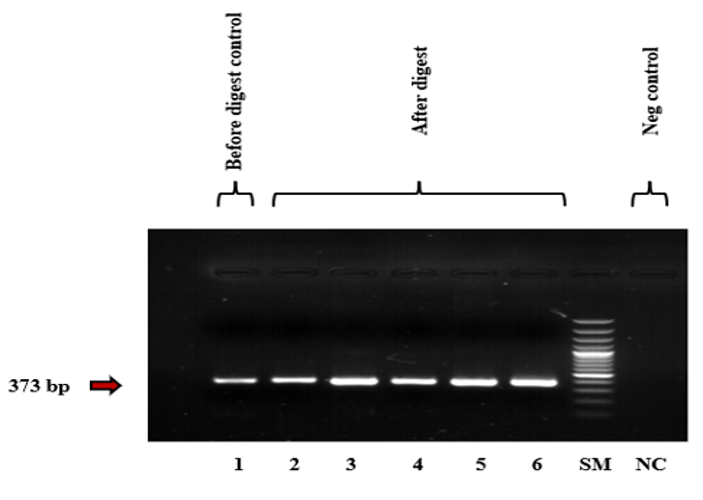
Figure 5. Electrophoretic analysis of TPMT*3C (719A>G) PCR products before and after AccI restriction enzyme digestion on a 1.5% agarose gel. Lane 1 shows the undigested PCR product (373 bp) and serves as the uncut control. Lanes 2–6 contain PCR products digested with AccI. No restriction fragments (238 bp and 90 bp) were detected in any of the digested samples; all retained the undigested 373 bp fragment, indicating the absence of the TPMT*3C (719A>G) polymorphism. (Prepared by Authors, 2026).
3.10 Sequencing analysis of exon 10
To verify the identity of the amplified TPMT exon 10 fragment, 19 patient samples with either reduced TPMT enzyme levels or evidence of myelosuppression (leukopenia and/or neutropenia) were subjected to Sanger sequencing. BLAST sequence alignment showed 99% sequence identity with the reference TPMT exon 10 sequence, confirming the specificity and accuracy of the PCR assay. The amplified exon 10 fragment encompassed the TPMT*3C (719A>G) variant as well as the rare TPMT*4 (626G>A), TPMT*7 (681T>G), and TPMT*8 (644G>A) variants. Variant analysis was performed using the NCBI SNP database and Chromas Lite software. None of these variants were detected in the 19 sequenced samples (data not shown).
3.11 TPMT enzyme activity
TPMT enzyme levels were measured in plasma samples from 70 of the 98 patients using a commercial ELISA kit (KazuoBio, Japan). Enzyme concentrations were calculated from a standard curve generated using optical density measurements at 450 nm. Among the analyzed patients, 8 (11.4%) exhibited low TPMT enzyme levels, 10 (14.3%) had intermediate levels, and 52 (74.3%) had high enzyme levels.
3.12 Frequency of TPMT variants
Among the 98 patients, one patient (1.0%) carried the TPMT*1/*3B heterozygous genotype, corresponding to an allele frequency of 0.71%. No TPMT*2, TPMT*3A, or TPMT*3C variants were detected in the study population. In addition, the rare TPMT*4, TPMT*7, TPMT*8, and TPMT*10 variants were not identified in the 19 patients evaluated by sequencing.
3.13 Genotype–phenotype correlation
The association between TPMT genotype and enzyme phenotype was evaluated in the 70 patients for whom both genotyping and plasma enzyme measurements were available. Among the 69 patients with the wild-type genotype, 7 exhibited low TPMT enzyme levels. The single patient carrying the TPMT*1/*3B heterozygous genotype also had reduced TPMT enzyme activity. No significant association was observed between TPMT genotype and enzyme phenotype.
3.14 Association between myelosuppression and hepatotoxicity before and during 6-mercaptopurine therapy
Among the 70 patients whose plasma TPMT enzyme levels were measured, the association between myelosuppression, including leukopenia and neutropenia, and hepatotoxicity before and during 6-MP therapy was evaluated. Hematological and hepatic toxicity were assessed using WBC count, absolute neutrophil count (ANC), and liver enzyme levels (ALT and AST). The results are summarized in Table 3.
As previously noted, TPMT allele frequencies vary considerably among populations and even within individual countries. An Israeli study evaluating TPMT*3A and *3C across several ethnic groups including Arabs, Jews, Druze, Kurds, and individuals of African descent reported the highest prevalence of TPMT polymorphisms in the Druze population (80.4% wild-type, 17.4% heterozygous, and 2.2% homozygous variants). In contrast, Jewish and Kurdish populations exhibited much lower frequencies, with 98.2% wild-type and 1.6% heterozygous genotypes. TPMT*3C predominated among individuals of African descent (5.3%), whereas TPMT*3A was the most frequent variant in the remaining groups (26). In the United States, sequencing-based analysis reported allele frequencies of 4.5% for TPMT*3A and 0.7% for TPMT*3C (27). A Palestinian study of 56 ALL patients identified only one TPMT*3A carrier (allele frequency 0.89%) (28), while in Japan TPMT*3C occurred at a frequency of 0.3% (29). The 0.71% allele frequency observed in our cohort is therefore consistent with previous reports.
4.2 Rare TPMT variants and inter-ethnic differences
Recent studies have increasingly focused on rare TPMT variants. In our cohort, four rare alleles (*4, *7, *8, and *10) were screened in 19 patients with low enzyme activity or myelosuppression, but none were detected. Similarly, a Polish study using HRMA reported TPMT*3A at 3.28%, whereas rare alleles (*30, *31, and *15) each occurred at a frequency of only 0.18% (30). In Korea, sequencing of 900 healthy individuals identified TPMT*3C in 2.8% and rare variants (*6, *16, and *32) in a combined 0.6% (31). Overall, TPMT deficiency demonstrates marked ethnic variability. TPMT*3A and *3B are most common in Caucasian (3.36% and 0.07%) and Hispanic populations (2.9% and 0.1%) (32–33), whereas TPMT*3C predominates in Asian and African populations, with reported frequencies of 2.21% and 4.57%, respectively (34).
4.3 TPMT enzyme phenotype evaluation
To evaluate TPMT phenotype, plasma enzyme concentrations were measured. For patients receiving long-term 6-MP maintenance therapy, therapeutic monitoring of TPMT activity and drug metabolites is recommended at weeks 14, 24, 34, 44, and 54 after treatment initiation (35). A U.S. study reported substantial ethnic differences in TPMT phenotype, with Americans showing the highest proportion of intermediate or low enzyme activity (10.3%) and the lowest methylated metabolite levels (0.33%), suggesting an increased risk of 6-MP toxicity (27). Asians had the lowest proportion of reduced TPMT activity (4.5%), whereas Caucasian and Hispanic populations showed intermediate activity in 7.45% of cases (36, 27). Reis et al. also demonstrated a trimodal distribution of TPMT activity, with 90% of individuals showing activity >11.3 units/μm³ RBCs, 9.8% between 5 and 11.3 units, and 0.3% exhibiting near-complete deficiency (<0.17 units) (37).
In the present study, TPMT activity was measured by ELISA in 70 patients. Eight (11.4%) had low enzyme activity, whereas 62 (88.6%) showed intermediate or high activity. Although direct comparison with metabolite concentrations would strengthen interpretation, our results were generally consistent with previous studies, showing no significant association between metabolite levels and enzyme activity (P = 0.81, OR [95% CI] = 1.25 [0.45–3.1]). Genotype–phenotype analysis likewise showed no significant association (P = 1, OR [95% CI] = 1). Among 69 patients with the wild-type genotype, seven had low enzyme activity, while one heterozygous TPMT*3B/*1 carrier also demonstrated low activity. Similar genotype–phenotype variability has been reported by Schaeffeler et al., who studied 1,214 German Caucasians and found genotype frequencies of TPMT*3A (4.4%), TPMT*3C (0.4%), and TPMT*2 (0.2%), alongside phenotypic distributions of 0.6% deficient, 9.9% intermediate, and 89.5% normal activity (38). Among 17 individuals with initial genotype–phenotype discordance, sequencing identified rare variants in four patients, including TPMT*9 (n = 2), TPMT*16 (n = 1), TPMT*17 (n = 1), and TPMT*18 (n = 1), increasing concordance from 86% to 89%. In the remaining 13 patients, undetected intronic or regulatory variants, including promoter mutations, may explain the reduced enzyme activity. Conversely, seven heterozygous patients exhibited unexpectedly high TPMT activity, suggesting the influence of physiological or environmental factors. Given the large size of the TPMT gene (34 kb, 10 exons), additional rare and population-specific variants are likely. TPMT*2 is more prevalent in Caucasians, whereas TPMT*6 and TPMT*8 occur more frequently in African and Asian populations (36, 27). Although TPMT*8 was initially considered rare, its frequency reaches 5.1–5.3% in African populations (34). These observations suggest that rare alleles may contribute to the genotype–phenotype discordance observed in our cohort. Although four uncommon variants (TPMT*4, *7, *8, and *10) were investigated, larger studies using comprehensive sequencing approaches are needed to define the full spectrum of TPMT polymorphisms in the Iranian population. Residual discordance may also reflect physiological variation or environmental influences (35).
4.4 Relationship between 6-MP side effects and TPMT phenotype/genotype
Pharmacogenetic studies in acute lymphoblastic leukemia have consistently shown that thiopurine S-methyltransferase (TPMT) activity influences the toxicity of 6-MP. Previous studies by Pui et al. (39) and Kim et al. (40) demonstrated that, despite favorable treatment outcomes, drug resistance and treatment failure related to adverse effects and myelosuppression occur in more than 20% of ALL patients. Leukopenia and neutropenia were reported in 7.28% of patients, comparable to the frequencies observed in our cohort (5.28% and 8.32%, respectively). Although Kim et al. found no significant association between TPMT polymorphisms and myelosuppressive toxicity, our findings suggest that reduced TPMT activity is associated with an increased risk of hematologic toxicity. Among eight patients with low TPMT activity, five developed leukopenia, whereas only three maintained normal white blood cell counts. In contrast, leukopenia occurred in 15 of 62 patients with intermediate or high TPMT activity. Likewise, neutropenia developed in six of eight patients with low TPMT activity compared with 17 of 62 patients with intermediate or high activity (P = 0.02). These findings indicate a significant relationship between reduced TPMT activity and susceptibility to leukopenia and neutropenia. Similar observations have been reported by Halvaty et al. in a cohort of 220 Slovak patients treated with 6-MP, in which 93% carried the wild-type TPMT genotype, 6% were heterozygous, and 1% were homozygous for mutant alleles. Patients with heterozygous or homozygous variants and intermediate TPMT activity experienced markedly greater reductions in white blood cell counts than those with wild-type genotypes and high enzyme activity (87% vs. 30%), supporting the value of TPMT genotype–phenotype assessment before treatment (41). These findings are consistent with our results and previous reports emphasizing the clinical utility of pre-treatment TPMT testing (38). Gisbert et al. evaluated 99 patients with inflammatory bowel disease receiving 6-MP and found that 93% had the wild-type TPMT genotype with high enzyme activity, whereas 7% carried polymorphic alleles associated with reduced activity. Bone marrow suppression occurred in four patients, although only one had low TPMT activity, indicating that hematologic toxicity is not exclusively determined by TPMT status (42).
Nevertheless, in our study, low plasma TPMT concentrations were significantly associated with 6-MP-induced myelosuppression, specifically leukopenia (<2000 WBC/µL) and neutropenia (<1000 neutrophils/µL). In contrast, no significant association was observed between TPMT activity and hepatotoxicity. TPMT*1/TPMT*3B was the most frequently detected polymorphism (1%). Adam et al. investigated 66 French patients with ALL and reported that elevated 6-MP metabolite concentrations were associated with hepatotoxicity in 95.7% of cases (43). In contrast, our study found no significant relationship between TPMT activity and elevated AST or ALT levels. Similarly, Xin et al. demonstrated that myelosuppressive toxicity differed significantly between patients with normal and reduced TPMT activity (P < 0.05), whereas hepatotoxicity showed no significant association with TPMT status, further supporting our findings (44).
5. Conclusion
Our findings demonstrate that reduced TPMT activity is significantly associated with an increased risk of 6-MP-induced myelosuppression, particularly leukopenia and neutropenia, whereas no significant association was observed with hepatotoxicity. Although common TPMT polymorphisms showed limited correlation with enzyme activity, the identification of rare variants improved genotype–phenotype concordance, highlighting the contribution of uncommon and potentially population-specific alleles to thiopurine metabolism. These findings support the clinical value of pre-treatment TPMT phenotyping together with comprehensive genotyping, including both common and rare TPMT variants, to individualize 6-MP dosing, reduce treatment-related toxicity, and improve the safety of thiopurine therapy in pediatric patients with acute lymphoblastic leukemia.
6. Declarations
6.1 Acknowledgments
The authors would like to express their sincere gratitude to the children and their parents for their participation and cooperation in this study. The authors also thank the physicians, nurses, and staff of the Hematology Department at Mofid Children's Hospital for their valuable assistance and support throughout the study.
6.2 Ethical Considerations
This study was approved by the Ethics Committee of Zanjan University of Medical Sciences.
All study procedures were conducted in accordance with the ethical principles of the Declaration of Helsinki and its subsequent amendments.
6.3 Authors' Contributions
Y.M., S.A., and M.J. contributed to the study conception and design, developed the methodology, and drafted the manuscript. S.Z. and S.R. contributed to the study conception, software development, formal data analysis, and critical revision of the manuscript.
All authors reviewed, approved, and agreed to the published version of the manuscript.
6.4 Conflict of Interest
The authors declare that they have no conflicts of interest.
6.5 Fund or Financial Support
This study was derived from an MSc dissertation and was financially supported by the Deputy for Research and Technology of Zanjan University of Medical Sciences under Grant No. A-11-190-5.
6.6 Using Artificial Intelligence Tools (AI Tools)
The authors used artificial intelligence (AI) tools to assist in drafting and improving the language of selected sections of the manuscript.
Full-Text: (33 Views)
ABSTRACT
Background & Objective: Thiopurine S-methyltransferase (TPMT) is a key enzyme in the metabolism of thiopurine drugs, including 6-mercaptopurine (6-MP). By methylating and inactivating 6-MP, TPMT regulates the accumulation of active metabolites and influences the risk of treatment-related toxicities, particularly myelosuppression. This study evaluated common TPMT polymorphisms (TPMT*2, TPMT*3A, TPMT*3B, and TPMT*3C), plasma TPMT enzyme levels, and their associations with 6-MP-induced adverse effects in pediatric ALL patients.
Materials & Methods: Ninety-eight patients with ALL receiving maintenance therapy with 6-MP under a standard-risk protocol were enrolled. TPMT*3B (460G>A) and TPMT*3C (719A>G) variants were analyzed by PCR-RFLP, while TPMT*2 (238G>C) was detected using allele-specific PCR. Sequencing was performed to confirm amplification of exons 7 and 10 in 19 samples each and exon 5 in two samples. Plasma TPMT enzyme levels were measured in 70 patients using ELISA. Associations between TPMT genotype, enzyme levels, and 6-MP-related toxicities, including leukopenia, neutropenia, and hepatotoxicity, were evaluated.
Results: The TPMT*3B variant was detected in one patient (allele frequency, 0.71%; heterozygous TPMT*3B/*1 genotype, 1.1%). No TPMT*2, TPMT*3A, TPMT*3C, or rare variants (TPMT*4, TPMT*7, TPMT*8, and TPMT*10) were identified. Sequencing confirmed the absence of these variants in the analyzed samples. Among the 70 patients assessed for TPMT activity, eight (11.4%) exhibited low enzyme levels. No significant association was observed between TPMT genotype and enzyme phenotype (P = 1.0). However, low TPMT enzyme levels were significantly associated with leukopenia (P = 0.04) and neutropenia (P = 0.02), but not hepatotoxicity (P = 0.12).
Conclusion: Low plasma TPMT enzyme activity was associated with an increased risk of 6-MP-induced myelosuppression in some patients with ALL. These findings suggest that assessment of TPMT enzyme activity, together with genotyping for common and rare TPMT variants, may improve prediction of thiopurine toxicity and support individualized 6-MP therapy.
Keywords: Pediatric Acute Lymphoblastic Leukemia, Thiopurine Methyltransferase, Polymorphism, Pharmacogenetics, 6-Mercaptopurine, Leukopenia
Background & Objective: Thiopurine S-methyltransferase (TPMT) is a key enzyme in the metabolism of thiopurine drugs, including 6-mercaptopurine (6-MP). By methylating and inactivating 6-MP, TPMT regulates the accumulation of active metabolites and influences the risk of treatment-related toxicities, particularly myelosuppression. This study evaluated common TPMT polymorphisms (TPMT*2, TPMT*3A, TPMT*3B, and TPMT*3C), plasma TPMT enzyme levels, and their associations with 6-MP-induced adverse effects in pediatric ALL patients.
Materials & Methods: Ninety-eight patients with ALL receiving maintenance therapy with 6-MP under a standard-risk protocol were enrolled. TPMT*3B (460G>A) and TPMT*3C (719A>G) variants were analyzed by PCR-RFLP, while TPMT*2 (238G>C) was detected using allele-specific PCR. Sequencing was performed to confirm amplification of exons 7 and 10 in 19 samples each and exon 5 in two samples. Plasma TPMT enzyme levels were measured in 70 patients using ELISA. Associations between TPMT genotype, enzyme levels, and 6-MP-related toxicities, including leukopenia, neutropenia, and hepatotoxicity, were evaluated.
Results: The TPMT*3B variant was detected in one patient (allele frequency, 0.71%; heterozygous TPMT*3B/*1 genotype, 1.1%). No TPMT*2, TPMT*3A, TPMT*3C, or rare variants (TPMT*4, TPMT*7, TPMT*8, and TPMT*10) were identified. Sequencing confirmed the absence of these variants in the analyzed samples. Among the 70 patients assessed for TPMT activity, eight (11.4%) exhibited low enzyme levels. No significant association was observed between TPMT genotype and enzyme phenotype (P = 1.0). However, low TPMT enzyme levels were significantly associated with leukopenia (P = 0.04) and neutropenia (P = 0.02), but not hepatotoxicity (P = 0.12).
Conclusion: Low plasma TPMT enzyme activity was associated with an increased risk of 6-MP-induced myelosuppression in some patients with ALL. These findings suggest that assessment of TPMT enzyme activity, together with genotyping for common and rare TPMT variants, may improve prediction of thiopurine toxicity and support individualized 6-MP therapy.
Keywords: Pediatric Acute Lymphoblastic Leukemia, Thiopurine Methyltransferase, Polymorphism, Pharmacogenetics, 6-Mercaptopurine, Leukopenia
1. Introduction
Acute lymphoblastic leukemia is the most common childhood malignancy and a hematologic cancer characterized by the clonal proliferation of immature lymphoid progenitor cells in the bone marrow. Advances in risk stratification, supportive care, and chemotherapy have transformed ALL from a highly fatal disease into one with long-term cure rates approaching 70–80% worldwide (1–3). Patients commonly present with fatigue, easy bruising or bleeding, recurrent infections, bone and joint pain, fever, lymphadenopathy, anemia, recurrent epistaxis and weight loss (4). The diagnosis and classification of ALL follow the World Health Organization (WHO) criteria, integrating morphologic, immunophenotypic, cytogenetic, molecular, and clinical characteristics (5). Current treatment consists of induction, consolidation, and maintenance phases using multimodal therapy, including chemotherapy, corticosteroids, radiotherapy in selected cases, hematopoietic stem cell transplantation for high-risk patients, and supportive care. Maintenance therapy, typically lasting 2–3 years, is primarily based on daily 6-mercaptopurine (6-MP) and weekly methotrexate, with intermittent vincristine and corticosteroids according to established treatment protocols (2, 6). Thiopurines, particularly 6-MP and azathioprine (AZA), have been widely used as antineoplastic and immunosuppressive agents for more than five decades. However, considerable inter-individual variability exists in treatment efficacy and toxicity. Patients with reduced thiopurine S-methyltransferase (TPMT) activity are at increased risk of severe myelosuppression, hepatotoxicity, hypersensitivity reactions, and other adverse effects, even at conventional doses (3, 7). Genetic variation plays a central role in determining drug metabolism and therapeutic response, and approximately 15–28% of patients receiving thiopurines experience adverse drug reactions requiring dose reduction or treatment discontinuation (8–10). Consequently, pharmacogenetically guided personalized therapy has become increasingly important for optimizing treatment efficacy while minimizing toxicity (11). In addition to ALL, thiopurines are widely prescribed for autoimmune diseases, inflammatory bowel disease, and organ transplantation (12). 6-Mercaptopurine is a prodrug that requires intracellular activation, whereas TPMT catalyzes the S-methylation and inactivation of thiopurines, thereby limiting the accumulation of active cytotoxic metabolites (13-14). The TPMT gene, located on chromosome 6p22.3, spans approximately 34 kb, contains 10 exons, and exhibits autosomal codominant inheritance. More than 60 TPMT allelic variants have been identified, although only a few account for most clinically significant cases of TPMT deficiency. Reduced TPMT activity results in excessive thiopurine metabolite accumulation and increased susceptibility to myelosuppression and hepatotoxicity (13-15, 16).
Pre-treatment TPMT genotyping or phenotyping is therefore recommended to individualize thiopurine dosing and reduce treatment-related toxicity (16). Patients carrying homozygous non-functional TPMT variants generally require marked dose reduction or alternative therapy, whereas heterozygous individuals exhibit intermediate enzyme activity and remain at increased risk of adverse drug reactions (17). Mutations affecting coding, intronic, or regulatory regions may impair TPMT expression or function (18). Among the reported polymorphisms, TPMT2, TPMT3A, TPMT3B, and TPMT3C are the most extensively investigated and clinically relevant variants, while TPMT*1 represents the wild-type allele with normal enzymatic activity (19). The present study aimed to determine the frequencies of TPMT2, TPMT3A, TPMT3B, and TPMT3C polymorphisms and evaluate their association with TPMT enzymatic activity in pediatric patients with acute lymphoblastic leukemia receiving 6-mercaptopurine maintenance therapy. In addition, the relationships between TPMT genotypes, white blood cell counts, and liver enzyme levels were investigated to assess the clinical impact of TPMT polymorphisms on thiopurine-induced myelosuppression, hepatotoxicity, and treatment outcomes.
2. Materials and Methods
2.1 Study population
A total of 98 children aged 1–9 years with acute lymphoblastic leukemia were enrolled in this study. Patients were either receiving 6-mercaptopurine (6-MP) maintenance therapy or had been newly diagnosed and were scheduled to receive 6-MP as part of their treatment protocol. All patients had a pre-B-cell immunophenotype, were classified as having standard-risk ALL, had no underlying comorbidities, and were treated according to standard therapeutic protocols.
Patients with hepatitis or any medical condition that could interfere with the study were excluded. High-risk patients with ALL were excluded, including those with a leukocyte count >50 × 10⁹/L, hypodiploidy, age <1 year, t (9; 22) translocation, 11q23 rearrangement, a history of hematopoietic stem cell transplantation, or other significant underlying diseases. Patients were recruited from the Department of Hematology and Oncology at Mofid Children's Hospital, Tehran, Iran. The diagnosis of ALL was established based on clinical findings, cytomorphology, immunophenotyping, and molecular analyses. Clinical and laboratory data, including white blood cell (WBC) count, absolute neutrophil count (ANC), and liver enzyme levels (ALT and AST), were obtained from the patients' medical records.
Peripheral blood samples were collected in EDTA from all participants and stored at −20°C until genomic DNA extraction. Written informed consent was obtained from the parents or legal guardians of all participants prior to enrollment.
2.2 Polymerase chain reaction (PCR)
PCR amplification was performed using the primer pairs listed in Table 1.
Pre-treatment TPMT genotyping or phenotyping is therefore recommended to individualize thiopurine dosing and reduce treatment-related toxicity (16). Patients carrying homozygous non-functional TPMT variants generally require marked dose reduction or alternative therapy, whereas heterozygous individuals exhibit intermediate enzyme activity and remain at increased risk of adverse drug reactions (17). Mutations affecting coding, intronic, or regulatory regions may impair TPMT expression or function (18). Among the reported polymorphisms, TPMT2, TPMT3A, TPMT3B, and TPMT3C are the most extensively investigated and clinically relevant variants, while TPMT*1 represents the wild-type allele with normal enzymatic activity (19). The present study aimed to determine the frequencies of TPMT2, TPMT3A, TPMT3B, and TPMT3C polymorphisms and evaluate their association with TPMT enzymatic activity in pediatric patients with acute lymphoblastic leukemia receiving 6-mercaptopurine maintenance therapy. In addition, the relationships between TPMT genotypes, white blood cell counts, and liver enzyme levels were investigated to assess the clinical impact of TPMT polymorphisms on thiopurine-induced myelosuppression, hepatotoxicity, and treatment outcomes.
2. Materials and Methods
2.1 Study population
A total of 98 children aged 1–9 years with acute lymphoblastic leukemia were enrolled in this study. Patients were either receiving 6-mercaptopurine (6-MP) maintenance therapy or had been newly diagnosed and were scheduled to receive 6-MP as part of their treatment protocol. All patients had a pre-B-cell immunophenotype, were classified as having standard-risk ALL, had no underlying comorbidities, and were treated according to standard therapeutic protocols.
Patients with hepatitis or any medical condition that could interfere with the study were excluded. High-risk patients with ALL were excluded, including those with a leukocyte count >50 × 10⁹/L, hypodiploidy, age <1 year, t (9; 22) translocation, 11q23 rearrangement, a history of hematopoietic stem cell transplantation, or other significant underlying diseases. Patients were recruited from the Department of Hematology and Oncology at Mofid Children's Hospital, Tehran, Iran. The diagnosis of ALL was established based on clinical findings, cytomorphology, immunophenotyping, and molecular analyses. Clinical and laboratory data, including white blood cell (WBC) count, absolute neutrophil count (ANC), and liver enzyme levels (ALT and AST), were obtained from the patients' medical records.
Peripheral blood samples were collected in EDTA from all participants and stored at −20°C until genomic DNA extraction. Written informed consent was obtained from the parents or legal guardians of all participants prior to enrollment.
2.2 Polymerase chain reaction (PCR)
PCR amplification was performed using the primer pairs listed in Table 1.
Table 1. Primers used for detection of multiple TPMT variants.
| Variant | Primer Name | Sequence (5' → 3') |
| TPMT*2 | A*2f238 (Forward – Allele A) | GTATGATTTTATGCAGGTTTG |
| M*2f238 (Forward – Allele M) | GTATGATTTTATGCAGGTTTC | |
| B*2R238 (Reverse) | TAAATAGGAACCATCGGACAC | |
| TPMT*3B | C*3f460 (Forward) | AGGCAGCTAGGGAAAAAGAAAGGTG |
| D*3R460 (Reverse) | CAAGCCTTATAGCCTTACACCCAGG | |
| TPMT*3C | E*3f719 (Forward) | GAGACAGAGTTTCACCATCTTGG |
| F*3R719 (Reverse) | CAGGCTTTAGCATAATTTTCAATTCCTC |
2.3 PCR amplification protocol
PCR amplification was performed in a total reaction volume of 50 µL. Each reaction contained 5 µL of 10× PCR buffer (final concentration 1×), 1.5 µL of MgCl₂ (50 mM) (final concentration 1.5 mM), 1 µL of dNTP mix (10 mM) (final concentration 200 µM), 1 µL each of forward and reverse primers (10 µM) (final concentration 0.2 µM each), and 0.2 µL of Taq DNA polymerase (5 U/µL), providing 1 U of enzyme per reaction. The remaining volume was adjusted with nuclease-free water, and genomic DNA was added as the PCR template. PCR amplification was carried out in a thermal cycler (Eppendorf, Germany) under the following conditions. For TPMT*2 and TPMT*3C polymorphisms, the program consisted of an initial denaturation at 94°C for 5 min, followed by 33 cycles of denaturation at 94°C for 30 s, annealing at 58°C for 30 s, and extension at 72°C for 1 min, with a final extension at 72°C for 5 min. For the TPMT*3B polymorphism, PCR amplification was performed using an initial denaturation at 94°C for 5 min, followed by 33 cycles of denaturation at 94°C for 30 s, annealing at 62°C for 30 s, and extension at 72°C for 30 s, followed by a final extension at 72°C for 5 min.
2.4 Molecular analysis of TPMT polymorphisms
TPMT*2 was genotyped using the amplification refractory mutation system polymerase chain reaction (ARMS-PCR). Two allele-specific forward primers were employed: one specific for the mutant allele (G238C) and the other for the wild-type allele, each generating a 235 bp amplicon. Amplification with only the wild-type primer indicated the absence of the TPMT*2 variant, amplification with only the mutant-specific primer indicated homozygosity for the mutation, and amplification with both primer sets identified heterozygous individuals. TPMT*3B and TPMT*3C polymorphisms were analyzed by PCR-RFLP. For TPMT*3B, the 700 bp PCR product was digested with MwoI, which cleaves the wild-type allele. Digestion into 443 bp and 251 bp fragments indicated the wild-type genotype, the presence of 700 bp, 443 bp, and 251 bp fragments indicated heterozygosity, and an undigested 700 bp fragment indicated homozygosity for the mutation. For TPMT*3C, the 373 bp PCR product was digested with AccI, which specifically cleaves the mutant allele. Digestion into 238 bp and 90 bp fragments indicated the presence of the mutation, whereas an undigested 373 bp fragment indicated the wild-type genotype. Individuals carrying both TPMT*3B and TPMT*3C variants were classified as having the TPMT*3A allele. Positive and negative controls were included in all PCR assays to ensure the accuracy and reliability of genotyping.
2.4 Measurement of TPMT protein levels by ELISA
TPMT protein levels were quantified using a commercially available quantitative sandwich ELISA. Briefly, microplate wells were pre-coated with a monoclonal antibody specific for thiopurine S-methyltransferase (TPMT). Standards and samples were added to the wells, allowing TPMT present in the samples to bind to the immobilized capture antibody. Following incubation, the wells were washed to remove unbound material. A biotin-conjugated anti-TPMT detection antibody was then added, followed by incubation and washing. Subsequently, avidin conjugated to horseradish peroxidase (HRP) was added to bind the biotinylated detection antibody. After three additional washing steps to remove unbound enzyme conjugate, the substrate solution was added, resulting in a colorimetric reaction proportional to the amount of TPMT bound in each well. The reaction was terminated after the specified incubation period, and absorbance was measured to determine TPMT concentrations based on the standard curve. The assay detection range was 1.56–100 mU/mL.
3. Result
3.1 Gender distribution in the study population
Of the 98 ALL patients, 52 were females (53.1%) and 46 were males (46.9%). No significant difference was observed in the gender distribution of the study population. Laboratory parameters were compared between male and female patients before and during 6-mercaptopurine (6-MP) therapy. No statistically significant gender-related differences were observed for any of the measured laboratory parameters (Table 2).
PCR amplification was performed in a total reaction volume of 50 µL. Each reaction contained 5 µL of 10× PCR buffer (final concentration 1×), 1.5 µL of MgCl₂ (50 mM) (final concentration 1.5 mM), 1 µL of dNTP mix (10 mM) (final concentration 200 µM), 1 µL each of forward and reverse primers (10 µM) (final concentration 0.2 µM each), and 0.2 µL of Taq DNA polymerase (5 U/µL), providing 1 U of enzyme per reaction. The remaining volume was adjusted with nuclease-free water, and genomic DNA was added as the PCR template. PCR amplification was carried out in a thermal cycler (Eppendorf, Germany) under the following conditions. For TPMT*2 and TPMT*3C polymorphisms, the program consisted of an initial denaturation at 94°C for 5 min, followed by 33 cycles of denaturation at 94°C for 30 s, annealing at 58°C for 30 s, and extension at 72°C for 1 min, with a final extension at 72°C for 5 min. For the TPMT*3B polymorphism, PCR amplification was performed using an initial denaturation at 94°C for 5 min, followed by 33 cycles of denaturation at 94°C for 30 s, annealing at 62°C for 30 s, and extension at 72°C for 30 s, followed by a final extension at 72°C for 5 min.
2.4 Molecular analysis of TPMT polymorphisms
TPMT*2 was genotyped using the amplification refractory mutation system polymerase chain reaction (ARMS-PCR). Two allele-specific forward primers were employed: one specific for the mutant allele (G238C) and the other for the wild-type allele, each generating a 235 bp amplicon. Amplification with only the wild-type primer indicated the absence of the TPMT*2 variant, amplification with only the mutant-specific primer indicated homozygosity for the mutation, and amplification with both primer sets identified heterozygous individuals. TPMT*3B and TPMT*3C polymorphisms were analyzed by PCR-RFLP. For TPMT*3B, the 700 bp PCR product was digested with MwoI, which cleaves the wild-type allele. Digestion into 443 bp and 251 bp fragments indicated the wild-type genotype, the presence of 700 bp, 443 bp, and 251 bp fragments indicated heterozygosity, and an undigested 700 bp fragment indicated homozygosity for the mutation. For TPMT*3C, the 373 bp PCR product was digested with AccI, which specifically cleaves the mutant allele. Digestion into 238 bp and 90 bp fragments indicated the presence of the mutation, whereas an undigested 373 bp fragment indicated the wild-type genotype. Individuals carrying both TPMT*3B and TPMT*3C variants were classified as having the TPMT*3A allele. Positive and negative controls were included in all PCR assays to ensure the accuracy and reliability of genotyping.
2.4 Measurement of TPMT protein levels by ELISA
TPMT protein levels were quantified using a commercially available quantitative sandwich ELISA. Briefly, microplate wells were pre-coated with a monoclonal antibody specific for thiopurine S-methyltransferase (TPMT). Standards and samples were added to the wells, allowing TPMT present in the samples to bind to the immobilized capture antibody. Following incubation, the wells were washed to remove unbound material. A biotin-conjugated anti-TPMT detection antibody was then added, followed by incubation and washing. Subsequently, avidin conjugated to horseradish peroxidase (HRP) was added to bind the biotinylated detection antibody. After three additional washing steps to remove unbound enzyme conjugate, the substrate solution was added, resulting in a colorimetric reaction proportional to the amount of TPMT bound in each well. The reaction was terminated after the specified incubation period, and absorbance was measured to determine TPMT concentrations based on the standard curve. The assay detection range was 1.56–100 mU/mL.
3. Result
3.1 Gender distribution in the study population
Of the 98 ALL patients, 52 were females (53.1%) and 46 were males (46.9%). No significant difference was observed in the gender distribution of the study population. Laboratory parameters were compared between male and female patients before and during 6-mercaptopurine (6-MP) therapy. No statistically significant gender-related differences were observed for any of the measured laboratory parameters (Table 2).
Table 2. Blood indices in ALL patients
| Laboratory Parameter | Time | Total Population (Mean [Range]) | Male | Female | p-value |
| WBC (×10⁹/L) | Before 6-MP | 8.2 [1.2 - 9.8] | 8.2 [1.7 - 8.2] | 5.2 [1.2 - 9.8] | 0.6 |
| Neutrophil (×10⁹/L) | Before 6-MP | 2.7 [1 - 2.7] | 2.7 [1.1 - 2.7] | 2.5 [1 - 2.2] | 0.25 |
| ALT (IU/L) | Before 6-MP | 24 [8 - 173] | 24 [11 - 173] | 22 [8 - 97] | 0.2 |
| AST (IU/L) | Before 6-MP | 27.8 [6 - 210] | 26.9 [9 - 210] | 27.5 [6 - 119] | 0.13 |
| WBC (×10⁹/L) | During 6-MP | 2.4 [1 - 4.2] | 2.6 [1.6 - 5.7] | 2.3 [1 - 3.2] | 0.3 |
| Neutrophil (×10⁹/L) | During 6-MP | 2.1 [0.5 - 7] | 2 [1 - 6.6] | 2.3 [0.5 - 7] | 0.23 |
| ALT (IU/L) | During 6-MP | 25 [8 - 180] | 24 [8 - 135] | 27 [10 - 180] | 0.7 |
| AST (IU/L) | During 6-MP | 28 [18 - 230] | 28 [18 - 230] | 27 [18 - 92] | 0.55 |
Note: This table presents the evaluation of hematologic indices in patients with ALL, before and during treatment with 6-MP. Parameters are reported for males, females, and the total population, along with corresponding p-values to assess statistical significance between sexes. No statistically significant differences (p < 0.05) were observed between male and female patients for any parameter.
3.2. PCR analysis of the TPMT*2 wild-type allele
The TPMT*2 polymorphism was analyzed in all 98 patients using AS-PCR. Representative electrophoretic analysis of PCR products amplified with primers specific for the wild-type allele is shown in Figure 1. A single amplicon of approximately 235 bp was detected in the positive samples.
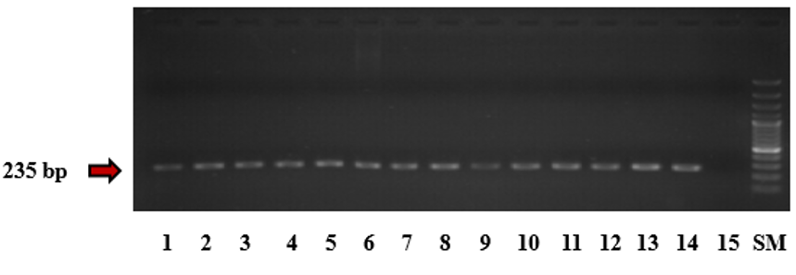
Figure 1. Electrophoretic analysis of PCR products amplified with wild-type allele-specific primers for detection of the TPMT*2 polymorphism on a 1.5% agarose gel. Lanes 1–14 show the expected 235 bp amplicon, indicating the presence of at least one wild-type allele (homozygous wild-type or heterozygous genotype). Final genotype assignment was determined by comparison with PCR results obtained using mutant allele-specific primers. Lane 15 represents the negative control, and SM denotes the 50 bp DNA ladder. (Prepared by Authors, 2026).
The TPMT*2 polymorphism was analyzed in all 98 patients using AS-PCR. Representative electrophoretic analysis of PCR products amplified with primers specific for the wild-type allele is shown in Figure 1. A single amplicon of approximately 235 bp was detected in the positive samples.
Figure 1. Electrophoretic analysis of PCR products amplified with wild-type allele-specific primers for detection of the TPMT*2 polymorphism on a 1.5% agarose gel. Lanes 1–14 show the expected 235 bp amplicon, indicating the presence of at least one wild-type allele (homozygous wild-type or heterozygous genotype). Final genotype assignment was determined by comparison with PCR results obtained using mutant allele-specific primers. Lane 15 represents the negative control, and SM denotes the 50 bp DNA ladder. (Prepared by Authors, 2026).
3.3 PCR analysis of the TPMT*2 mutant allele
PCR amplification using mutant allele-specific primers for the TPMT*2 polymorphism was performed for all 98 patient samples
No amplification products were detected in any of the samples, indicating the absence of the TPMT*2 mutant allele in the study population (data not shown).
3.4 Sequence confirmation of the TPMT*2 PCR product
To verify the identity of the amplified TPMT*2 PCR product, two randomly selected patient samples were subjected to Sanger sequencing. Sequence alignment using the BLAST demonstrated 99% sequence identity with the reference TPMT*2 sequence, confirming the specificity and accuracy of the PCR amplification (Figure 2).
PCR amplification using mutant allele-specific primers for the TPMT*2 polymorphism was performed for all 98 patient samples
No amplification products were detected in any of the samples, indicating the absence of the TPMT*2 mutant allele in the study population (data not shown).
3.4 Sequence confirmation of the TPMT*2 PCR product
To verify the identity of the amplified TPMT*2 PCR product, two randomly selected patient samples were subjected to Sanger sequencing. Sequence alignment using the BLAST demonstrated 99% sequence identity with the reference TPMT*2 sequence, confirming the specificity and accuracy of the PCR amplification (Figure 2).
Figure 2. Sequencing results of the amplified fragment for analysis of the TPMT*2 polymorphism. (Prepared by Authors, 2026).
3.5 PCR-RFLP analysis
The TPMT*3B polymorphism was analyzed by PCR-RFLP. PCR amplification of exon 7 of the TPMT gene generated the expected 700 bp amplicon.
The PCR products were subsequently digested with the restriction enzyme MwoI, which specifically cleaves the wild-type allele into 443 bp and 251 bp fragments. Genotypes were determined according to the restriction fragment pattern. Samples displaying 443 bp and 251 bp fragments were classified as wild-type, indicating the absence of the TPMT*3B polymorphism. Samples exhibiting 700 bp, 443 bp, and 251 bp fragments were identified as heterozygous, whereas samples showing only the undigested 700 bp fragment were classified as homozygous for the TPMT*3B variant (Figure 3). As shown in Figure 3, digestion of the TPMT*3B PCR products with MwoI generated the expected 443 bp and 251 bp fragments in wild-type samples (lanes 1, 2, 3, 5, and 6). In contrast, lane 4 displayed three fragments (700 bp, 443 bp, and 251 bp), consistent with a heterozygous TPMT*3B genotype.
The TPMT*3B polymorphism was analyzed by PCR-RFLP. PCR amplification of exon 7 of the TPMT gene generated the expected 700 bp amplicon.
The PCR products were subsequently digested with the restriction enzyme MwoI, which specifically cleaves the wild-type allele into 443 bp and 251 bp fragments. Genotypes were determined according to the restriction fragment pattern. Samples displaying 443 bp and 251 bp fragments were classified as wild-type, indicating the absence of the TPMT*3B polymorphism. Samples exhibiting 700 bp, 443 bp, and 251 bp fragments were identified as heterozygous, whereas samples showing only the undigested 700 bp fragment were classified as homozygous for the TPMT*3B variant (Figure 3). As shown in Figure 3, digestion of the TPMT*3B PCR products with MwoI generated the expected 443 bp and 251 bp fragments in wild-type samples (lanes 1, 2, 3, 5, and 6). In contrast, lane 4 displayed three fragments (700 bp, 443 bp, and 251 bp), consistent with a heterozygous TPMT*3B genotype.
Figure 3. Electrophoresis of PCR products for TPMT*3B polymorphism, SM denotes the Size Marker. (Prepared by Authors, 2026).
3.6 Sequencing analysis of the TPMT*3B polymorphism
To verify the identity of the amplified TPMT*3B PCR product, 19 samples were randomly selected for Sanger sequencing. Sequence alignment using BLAST demonstrated 98% sequence identity with the reference TPMT exon 7 sequence, confirming the specificity and accuracy of the PCR assay (data not shown).
Sequence analysis confirmed the presence of the TPMT*3B variant (460G>A) in heterozygous samples. The sequencing chromatogram showed overlapping G and A peaks at nucleotide position 460, consistent with a **TPMT1/3B heterozygous genotype. This finding was in agreement with the PCR-RFLP results, in which three restriction fragments (700 bp, 443 bp, and 251 bp) were observed.
3.7 Frequency distribution of the TPMT*3B polymorphism
Among the 98 patients analyzed, one patient (1.0%) was heterozygous for the TPMT*3B variant (**TPMT1/3B), whereas the remaining 97 patients (99.0%) had the wild-type genotype (**TPMT1/1). The allele frequency of TPMT*3B was 0.71%, indicating that this variant is rare in the study population.
3.8 Analysis of the TPMT*10 (430G>C) variant
The TPMT*10 (430G>C) variant was evaluated in 18 patients with either reduced TPMT enzyme activity or evidence of myelosuppression, including leukopenia and neutropenia. Sequence analysis identified the wild-type G nucleotide in all patients, and no TPMT*10 variants were detected (Figure 4).
To verify the identity of the amplified TPMT*3B PCR product, 19 samples were randomly selected for Sanger sequencing. Sequence alignment using BLAST demonstrated 98% sequence identity with the reference TPMT exon 7 sequence, confirming the specificity and accuracy of the PCR assay (data not shown).
Sequence analysis confirmed the presence of the TPMT*3B variant (460G>A) in heterozygous samples. The sequencing chromatogram showed overlapping G and A peaks at nucleotide position 460, consistent with a **TPMT1/3B heterozygous genotype. This finding was in agreement with the PCR-RFLP results, in which three restriction fragments (700 bp, 443 bp, and 251 bp) were observed.
3.7 Frequency distribution of the TPMT*3B polymorphism
Among the 98 patients analyzed, one patient (1.0%) was heterozygous for the TPMT*3B variant (**TPMT1/3B), whereas the remaining 97 patients (99.0%) had the wild-type genotype (**TPMT1/1). The allele frequency of TPMT*3B was 0.71%, indicating that this variant is rare in the study population.
3.8 Analysis of the TPMT*10 (430G>C) variant
The TPMT*10 (430G>C) variant was evaluated in 18 patients with either reduced TPMT enzyme activity or evidence of myelosuppression, including leukopenia and neutropenia. Sequence analysis identified the wild-type G nucleotide in all patients, and no TPMT*10 variants were detected (Figure 4).
Figure 4. Sequence analysis of the TPMT*10 (430G>C) variant. The chromatogram demonstrates the presence of the wild-type G nucleotide at position 430, indicating the absence of the TPMT*10 (430G>C) variant. The corresponding sequence is GGGATAGAGGAGCATTAGTTGCC. (Prepared by Authors, 2026).
3.9 Analysis of the TPMT*3C polymorphism
The TPMT*3C polymorphism (719A>G) was analyzed by PCR-RFLP. PCR amplification of exon 10 of the TPMT gene generated the expected 373 bp amplicon. The PCR products were subsequently digested with the restriction enzyme AccI, which specifically cleaves the mutant allele, producing fragments of 238 bp and 90 bp.
Genotypes were determined according to the restriction fragment pattern. Samples showing only the 373 bp fragments were classified as wild-type, indicating the absence of the TPMT*3C polymorphism.Samples displaying 238 bp and 90 bp fragments were classified as homozygous for the mutant allele, whereas samples exhibiting 373 bp, 238 bp, and 90 bp fragments were considered heterozygous. As shown in Figure 5, all samples exhibited only the undigested 373 bp fragment following AccI digestion, indicating the absence of the TPMT*3C (719A>G) polymorphism in the study population.
The TPMT*3C polymorphism (719A>G) was analyzed by PCR-RFLP. PCR amplification of exon 10 of the TPMT gene generated the expected 373 bp amplicon. The PCR products were subsequently digested with the restriction enzyme AccI, which specifically cleaves the mutant allele, producing fragments of 238 bp and 90 bp.
Genotypes were determined according to the restriction fragment pattern. Samples showing only the 373 bp fragments were classified as wild-type, indicating the absence of the TPMT*3C polymorphism.Samples displaying 238 bp and 90 bp fragments were classified as homozygous for the mutant allele, whereas samples exhibiting 373 bp, 238 bp, and 90 bp fragments were considered heterozygous. As shown in Figure 5, all samples exhibited only the undigested 373 bp fragment following AccI digestion, indicating the absence of the TPMT*3C (719A>G) polymorphism in the study population.
Figure 5. Electrophoretic analysis of TPMT*3C (719A>G) PCR products before and after AccI restriction enzyme digestion on a 1.5% agarose gel. Lane 1 shows the undigested PCR product (373 bp) and serves as the uncut control. Lanes 2–6 contain PCR products digested with AccI. No restriction fragments (238 bp and 90 bp) were detected in any of the digested samples; all retained the undigested 373 bp fragment, indicating the absence of the TPMT*3C (719A>G) polymorphism. (Prepared by Authors, 2026).
3.10 Sequencing analysis of exon 10
To verify the identity of the amplified TPMT exon 10 fragment, 19 patient samples with either reduced TPMT enzyme levels or evidence of myelosuppression (leukopenia and/or neutropenia) were subjected to Sanger sequencing. BLAST sequence alignment showed 99% sequence identity with the reference TPMT exon 10 sequence, confirming the specificity and accuracy of the PCR assay. The amplified exon 10 fragment encompassed the TPMT*3C (719A>G) variant as well as the rare TPMT*4 (626G>A), TPMT*7 (681T>G), and TPMT*8 (644G>A) variants. Variant analysis was performed using the NCBI SNP database and Chromas Lite software. None of these variants were detected in the 19 sequenced samples (data not shown).
3.11 TPMT enzyme activity
TPMT enzyme levels were measured in plasma samples from 70 of the 98 patients using a commercial ELISA kit (KazuoBio, Japan). Enzyme concentrations were calculated from a standard curve generated using optical density measurements at 450 nm. Among the analyzed patients, 8 (11.4%) exhibited low TPMT enzyme levels, 10 (14.3%) had intermediate levels, and 52 (74.3%) had high enzyme levels.
3.12 Frequency of TPMT variants
Among the 98 patients, one patient (1.0%) carried the TPMT*1/*3B heterozygous genotype, corresponding to an allele frequency of 0.71%. No TPMT*2, TPMT*3A, or TPMT*3C variants were detected in the study population. In addition, the rare TPMT*4, TPMT*7, TPMT*8, and TPMT*10 variants were not identified in the 19 patients evaluated by sequencing.
3.13 Genotype–phenotype correlation
The association between TPMT genotype and enzyme phenotype was evaluated in the 70 patients for whom both genotyping and plasma enzyme measurements were available. Among the 69 patients with the wild-type genotype, 7 exhibited low TPMT enzyme levels. The single patient carrying the TPMT*1/*3B heterozygous genotype also had reduced TPMT enzyme activity. No significant association was observed between TPMT genotype and enzyme phenotype.
3.14 Association between myelosuppression and hepatotoxicity before and during 6-mercaptopurine therapy
Among the 70 patients whose plasma TPMT enzyme levels were measured, the association between myelosuppression, including leukopenia and neutropenia, and hepatotoxicity before and during 6-MP therapy was evaluated. Hematological and hepatic toxicity were assessed using WBC count, absolute neutrophil count (ANC), and liver enzyme levels (ALT and AST). The results are summarized in Table 3.
Table 3. Association of myelosuppression and hepatotoxicity before and during 6-MP therapy in pediatric ALL patients.
| Adverse Event | Before 6-MP, n (%) | During 6-MP, n (%) | P Value | OR (95% CI) |
| Leukopenia (WBC <2,000 cells/µL) | ||||
| Present | 9 (12.9) | 20 (28.6) | 0.04* | 7.2 (5.6–13.1) |
| Absent | 61 (87.1) | 50 (71.4) | — | — |
| Neutropenia (ANC <1,000 cells/µL) | ||||
| Present | 11 (15.7) | 23 (32.9) | 0.03* | 6.2 (5.9–16.1) |
| Absent | 59 (84.3) | 47 (67.1) | — | — |
| Hepatotoxicity (ALT >50 U/L) | ||||
| Present | 5 (7.1) | 13 (18.6) | 0.07 | 2.96 (1.8–8.8) |
| Absent | 65 (92.9) | 57 (81.4) | — | — |
| Hepatotoxicity (AST >50 U/L) | ||||
| Present | 4 (5.7) | 12 (17.1) | 0.06 | 3.4 (1.04–11.16) |
| Absent | 66 (94.3) | 58 (82.9) | — | — |
Note: Statistically significant results are indicated by an asterisk (*; P < 0.05). Associations between 6-mercaptopurine (6-MP)-related adverse effects and clinical variables were analyzed using the χ² test, and odds ratios (ORs) with 95% confidence intervals (95% CIs) were calculated. During maintenance therapy for ALL, a WBC count of 2,000–3,000 cells/µL is considered the target therapeutic range, whereas a WBC count of <2,000 cells/µL was defined as leukopenia attributable to 6-MP therapy. An absolute neutrophil count (ANC) of <1,000 cells/µL was considered indicative of neutropenia. Serum AST and ALT levels >50 U/L were considered elevated and indicative of hepatotoxicity.
3.15 Association of myelosuppression and hepatotoxicity with 6-mercaptopurine therapy
Compared with baseline, 6-MP therapy was associated with a significant increase in myelosuppression. The incidence of leukopenia increased significantly after treatment (OR = 2.6, 95% CI: 1.16–5.90; P = 0.03), as did the incidence of neutropenia (OR = 2.7, 95% CI: 1.13–6.50; P = 0.04). These findings indicate that treatment with 6-MP significantly increased the risk of hematological toxicity. An increase in liver enzyme levels was also observed during 6-MP therapy, although the associations did not reach statistical significance. Elevated ALT was associated with an OR of 3.3 (95% CI: 1.0–8.8; P = 0.07), while elevated AST showed an OR of 3.4 (95% CI: 1.04–11.16; P = 0.06). These results suggest a trend toward 6-MP-induced hepatotoxicity.
3.16 Association between TPMT enzyme concentration and myelosuppression (leukopenia and neutropenia)
Before initiation of 6-MP therapy, leukopenia was observed in 2 of 8 patients (25.0%) with low TPMT enzyme levels and in 7 of 62 patients (11.3%) with intermediate or high TPMT enzyme levels. Similarly, neutropenia was present in 2 of 8 patients (25.0%) with low TPMT enzyme levels and in 9 of 62 patients (14.5%) with intermediate or high enzyme levels. No significant association was observed between TPMT enzyme concentration and either leukopenia (OR = 2.6, 95% CI: 0.4–15.5; P = 0.27) or neutropenia (OR = 1.9, 95% CI: 0.34–11.3; P = 0.45) at baseline. During 6-MP therapy, a substantially higher proportion of patients with low TPMT enzyme levels developed myelosuppression. Leukopenia occurred in 5 of 8 patients (62.5%) with low TPMT enzyme levels compared with 15 of 62 patients (24.2%) with intermediate or high enzyme levels. Low TPMT enzyme concentration was significantly associated with an increased risk of leukopenia (OR = 5.22, 95% CI: 1.1–24.5; P = 0.04). Likewise, neutropenia developed in 6 of 8 patients (75.0%) with low TPMT enzyme levels compared with 17 of 62 patients (27.4%) with intermediate or high enzyme levels. Low TPMT enzyme activity was significantly associated with an increased risk of neutropenia (OR = 7.9, 95% CI: 1.5–43.2; P = 0.02). Overall, these findings indicate that low TPMT enzyme activity is associated with a significantly increased risk of 6-MP-induced myelosuppression, particularly leukopenia and neutropenia, during maintenance therapy for acute lymphoblastic leukemia. In contrast, no significant association between TPMT enzyme concentration and either leukopenia or neutropenia was observed before treatment. These results suggest that reduced TPMT activity may predispose patients to hematologic toxicity following exposure to 6-MP.
3.17 Association between TPMT enzyme concentration and hepatotoxicity
Before treatment, 1 of 8 patients (12.5%) with low TPMT enzyme levels had elevated AST, compared with 3 of 62 patients (4.8%) with intermediate or high enzyme levels. No significant association was observed between TPMT enzyme concentration and elevated AST before treatment (OR = 2.8, 95% CI: 0.28–30.8; P = 0.40). Similarly, elevated ALT was detected in 2 of 8 patients (25.0%) with low TPMT enzyme levels versus 3 of 62 patients (4.8%) with intermediate or high levels. Although the odds ratio suggested a higher likelihood of ALT elevation in patients with low TPMT enzyme activity, the association was not statistically significant (OR = 6.44, 95% CI: 0.9–46.0; P = 0.06). During 6-MP therapy, elevated AST occurred in 3 of 8 patients (37.5%) with low TPMT enzyme levels and 9 of 62 patients (14.5%) with intermediate or high levels. This difference was not statistically significant (OR = 3.5, 95% CI: 0.72–17.4; P = 0.12). Likewise, elevated ALT occurred in 3 of 8 patients (37.5%) with low TPMT enzyme levels compared with 5 of 62 patients (8.1%) with intermediate or high levels. Although ALT elevation was more frequent among patients with low TPMT activity, the association was not statistically significant (OR = 3.1, 95% CI: 0.64–15.2; P = 0.16). Overall, no statistically significant association was identified between TPMT enzyme concentration and hepatotoxicity before or during 6-MP therapy. However, consistently higher odds ratios for AST and ALT elevations among patients with low TPMT activity suggest a possible trend toward increased hepatotoxicity susceptibility that warrants investigation in larger cohorts.
4. Discussion
Thiopurine S-methyltransferase is a cytosolic enzyme that catalyzes the methylation and inactivation of thiopurines, including 6-MP and 6-thioguanine. As a cornerstone of maintenance therapy for childhood ALL, 6-MP is administered daily for up to three years (14, 20). Following intracellular activation to thioguanine nucleotides, TPMT converts these metabolites into the inactive metabolite 6-methylmercaptopurine (3, 20). Patients with reduced or absent TPMT activity accumulate excessive thioguanine nucleotides, predisposing them to severe adverse effects, particularly myelosuppression and hepatotoxicity (20-21). Consequently, TPMT testing has become an important component of individualized thiopurine therapy (13-14). TPMT activity is largely determined by genetic polymorphisms. Approximately 89% of individuals have normal enzyme activity, about 11% are heterozygous with intermediate activity, and less than 1% are homozygous for variant alleles with little or no enzyme activity (14). TPMT activity is commonly measured in erythrocytes by ELISA or HPLC, although plasma concentrations can also be determined by ELISA. Because the distribution of TPMT variants differs among ethnic populations, numerous studies have investigated allele frequencies and their relationship with thiopurine toxicity, underscoring the clinical value of TPMT-guided treatment. The present study is one of the few conducted in Iran to simultaneously evaluate common TPMT polymorphisms, plasma TPMT enzyme levels, and 6-MP-related toxicities, including leukopenia, neutropenia, and hepatotoxicity, in children with ALL.
4.1 TPMT genotyping analysis
Ninety-eight children with standard-risk ALL were screened for the common TPMT alleles (TPMT*2, TPMT*3B, TPMT*3C, and TPMT*3A) using allele-specific PCR and PCR-RFLP. The TPMT*3B variant was identified in one patient (allele frequency 0.71%) with the TPMT*1/*3B genotype, whereas TPMT*2, TPMT*3C, and TPMT*3A were not detected. Sequencing of 40 selected samples including patients with low TPMT enzyme activity or clinical evidence of leukopenia or neutropenia confirmed all PCR findings. Rare variants (TPMT*4, TPMT*7, TPMT*8, and TPMT*10) were also examined but were not identified. As shown in Table 4, previous studies have reported variable frequencies of TPMT polymorphisms in the Iranian population. Azad et al. found allele frequencies of TPMT*3A (2.18%), TPMT*3C (2.47%), and TPMT*2 as the predominant variant, while TPMT*3B was not detected; approximately 7.1% of individuals carried at least one variant allele (22).
In southern Iran, Bahari et al. reported frequencies of TPMT*2 (2.15%), TPMT*3A (1.68%), TPMT*3B (1.62%), and TPMT*3C (0.54%), with an overall polymorphism frequency of approximately 6% (23). Moini et al. observed TPMT*1/*3C in 5% and TPMT*1/*2 in 0.2% of healthy individuals, with no TPMT*3A or TPMT*3B variants detected, findings that more closely resemble those of the present study (24). These differences likely reflect ethnic and regional variation in allele distribution within Iran. A major strength of the present study is the confirmation of PCR-based genotyping by DNA sequencing, the reference standard for mutation analysis, which enhances the reliability of the results.
Although genotype frequencies did not differ significantly from those reported in healthy Iranian populations, direct comparisons should be interpreted cautiously because our cohort consisted exclusively of children with ALL receiving a standardized treatment protocol. Similarly, El-Kaffash et al. reported that 97.5% of pediatric ALL patients carried the TPMT*1/*1 genotype and 2.5% carried TPMT*1/*3A, while 32.5% experienced hepatotoxicity and/or myelosuppression during 6-MP therapy (25).
Compared with previous Iranian studies, our work provides a more comprehensive evaluation by integrating TPMT genotyping, plasma enzyme phenotyping, systematic assessment of treatment-related toxicities, and screening for both common and rare TPMT variants (Table 4).
Compared with baseline, 6-MP therapy was associated with a significant increase in myelosuppression. The incidence of leukopenia increased significantly after treatment (OR = 2.6, 95% CI: 1.16–5.90; P = 0.03), as did the incidence of neutropenia (OR = 2.7, 95% CI: 1.13–6.50; P = 0.04). These findings indicate that treatment with 6-MP significantly increased the risk of hematological toxicity. An increase in liver enzyme levels was also observed during 6-MP therapy, although the associations did not reach statistical significance. Elevated ALT was associated with an OR of 3.3 (95% CI: 1.0–8.8; P = 0.07), while elevated AST showed an OR of 3.4 (95% CI: 1.04–11.16; P = 0.06). These results suggest a trend toward 6-MP-induced hepatotoxicity.
3.16 Association between TPMT enzyme concentration and myelosuppression (leukopenia and neutropenia)
Before initiation of 6-MP therapy, leukopenia was observed in 2 of 8 patients (25.0%) with low TPMT enzyme levels and in 7 of 62 patients (11.3%) with intermediate or high TPMT enzyme levels. Similarly, neutropenia was present in 2 of 8 patients (25.0%) with low TPMT enzyme levels and in 9 of 62 patients (14.5%) with intermediate or high enzyme levels. No significant association was observed between TPMT enzyme concentration and either leukopenia (OR = 2.6, 95% CI: 0.4–15.5; P = 0.27) or neutropenia (OR = 1.9, 95% CI: 0.34–11.3; P = 0.45) at baseline. During 6-MP therapy, a substantially higher proportion of patients with low TPMT enzyme levels developed myelosuppression. Leukopenia occurred in 5 of 8 patients (62.5%) with low TPMT enzyme levels compared with 15 of 62 patients (24.2%) with intermediate or high enzyme levels. Low TPMT enzyme concentration was significantly associated with an increased risk of leukopenia (OR = 5.22, 95% CI: 1.1–24.5; P = 0.04). Likewise, neutropenia developed in 6 of 8 patients (75.0%) with low TPMT enzyme levels compared with 17 of 62 patients (27.4%) with intermediate or high enzyme levels. Low TPMT enzyme activity was significantly associated with an increased risk of neutropenia (OR = 7.9, 95% CI: 1.5–43.2; P = 0.02). Overall, these findings indicate that low TPMT enzyme activity is associated with a significantly increased risk of 6-MP-induced myelosuppression, particularly leukopenia and neutropenia, during maintenance therapy for acute lymphoblastic leukemia. In contrast, no significant association between TPMT enzyme concentration and either leukopenia or neutropenia was observed before treatment. These results suggest that reduced TPMT activity may predispose patients to hematologic toxicity following exposure to 6-MP.
3.17 Association between TPMT enzyme concentration and hepatotoxicity
Before treatment, 1 of 8 patients (12.5%) with low TPMT enzyme levels had elevated AST, compared with 3 of 62 patients (4.8%) with intermediate or high enzyme levels. No significant association was observed between TPMT enzyme concentration and elevated AST before treatment (OR = 2.8, 95% CI: 0.28–30.8; P = 0.40). Similarly, elevated ALT was detected in 2 of 8 patients (25.0%) with low TPMT enzyme levels versus 3 of 62 patients (4.8%) with intermediate or high levels. Although the odds ratio suggested a higher likelihood of ALT elevation in patients with low TPMT enzyme activity, the association was not statistically significant (OR = 6.44, 95% CI: 0.9–46.0; P = 0.06). During 6-MP therapy, elevated AST occurred in 3 of 8 patients (37.5%) with low TPMT enzyme levels and 9 of 62 patients (14.5%) with intermediate or high levels. This difference was not statistically significant (OR = 3.5, 95% CI: 0.72–17.4; P = 0.12). Likewise, elevated ALT occurred in 3 of 8 patients (37.5%) with low TPMT enzyme levels compared with 5 of 62 patients (8.1%) with intermediate or high levels. Although ALT elevation was more frequent among patients with low TPMT activity, the association was not statistically significant (OR = 3.1, 95% CI: 0.64–15.2; P = 0.16). Overall, no statistically significant association was identified between TPMT enzyme concentration and hepatotoxicity before or during 6-MP therapy. However, consistently higher odds ratios for AST and ALT elevations among patients with low TPMT activity suggest a possible trend toward increased hepatotoxicity susceptibility that warrants investigation in larger cohorts.
4. Discussion
Thiopurine S-methyltransferase is a cytosolic enzyme that catalyzes the methylation and inactivation of thiopurines, including 6-MP and 6-thioguanine. As a cornerstone of maintenance therapy for childhood ALL, 6-MP is administered daily for up to three years (14, 20). Following intracellular activation to thioguanine nucleotides, TPMT converts these metabolites into the inactive metabolite 6-methylmercaptopurine (3, 20). Patients with reduced or absent TPMT activity accumulate excessive thioguanine nucleotides, predisposing them to severe adverse effects, particularly myelosuppression and hepatotoxicity (20-21). Consequently, TPMT testing has become an important component of individualized thiopurine therapy (13-14). TPMT activity is largely determined by genetic polymorphisms. Approximately 89% of individuals have normal enzyme activity, about 11% are heterozygous with intermediate activity, and less than 1% are homozygous for variant alleles with little or no enzyme activity (14). TPMT activity is commonly measured in erythrocytes by ELISA or HPLC, although plasma concentrations can also be determined by ELISA. Because the distribution of TPMT variants differs among ethnic populations, numerous studies have investigated allele frequencies and their relationship with thiopurine toxicity, underscoring the clinical value of TPMT-guided treatment. The present study is one of the few conducted in Iran to simultaneously evaluate common TPMT polymorphisms, plasma TPMT enzyme levels, and 6-MP-related toxicities, including leukopenia, neutropenia, and hepatotoxicity, in children with ALL.
4.1 TPMT genotyping analysis
Ninety-eight children with standard-risk ALL were screened for the common TPMT alleles (TPMT*2, TPMT*3B, TPMT*3C, and TPMT*3A) using allele-specific PCR and PCR-RFLP. The TPMT*3B variant was identified in one patient (allele frequency 0.71%) with the TPMT*1/*3B genotype, whereas TPMT*2, TPMT*3C, and TPMT*3A were not detected. Sequencing of 40 selected samples including patients with low TPMT enzyme activity or clinical evidence of leukopenia or neutropenia confirmed all PCR findings. Rare variants (TPMT*4, TPMT*7, TPMT*8, and TPMT*10) were also examined but were not identified. As shown in Table 4, previous studies have reported variable frequencies of TPMT polymorphisms in the Iranian population. Azad et al. found allele frequencies of TPMT*3A (2.18%), TPMT*3C (2.47%), and TPMT*2 as the predominant variant, while TPMT*3B was not detected; approximately 7.1% of individuals carried at least one variant allele (22).
In southern Iran, Bahari et al. reported frequencies of TPMT*2 (2.15%), TPMT*3A (1.68%), TPMT*3B (1.62%), and TPMT*3C (0.54%), with an overall polymorphism frequency of approximately 6% (23). Moini et al. observed TPMT*1/*3C in 5% and TPMT*1/*2 in 0.2% of healthy individuals, with no TPMT*3A or TPMT*3B variants detected, findings that more closely resemble those of the present study (24). These differences likely reflect ethnic and regional variation in allele distribution within Iran. A major strength of the present study is the confirmation of PCR-based genotyping by DNA sequencing, the reference standard for mutation analysis, which enhances the reliability of the results.
Although genotype frequencies did not differ significantly from those reported in healthy Iranian populations, direct comparisons should be interpreted cautiously because our cohort consisted exclusively of children with ALL receiving a standardized treatment protocol. Similarly, El-Kaffash et al. reported that 97.5% of pediatric ALL patients carried the TPMT*1/*1 genotype and 2.5% carried TPMT*1/*3A, while 32.5% experienced hepatotoxicity and/or myelosuppression during 6-MP therapy (25).
Compared with previous Iranian studies, our work provides a more comprehensive evaluation by integrating TPMT genotyping, plasma enzyme phenotyping, systematic assessment of treatment-related toxicities, and screening for both common and rare TPMT variants (Table 4).
Table 4. Frequency of common TPMT variant alleles reported in Iranian populations.
| Reference | TPMT*2 (%) | TPMT*3A (%) | TPMT*3B (%) | TPMT*3C (%) | TPMT*4 (%) | TPMT*7 (%) | TPMT*8 (%) | TPMT*10 (%) | Total Variant Alleles (%) | |
| Azad et al., (22) | 3.94 | 0.79 | 0 | 1.57 | – | – | – | – | 6.30 | |
| Bahari et al., (23) | 2.16 | 1.68 | 1.62 | 0.54 | – | – | – | – | 6.00 | |
| Moini et al., (24) | 0.10 | 0 | 0 | 2.50 | – | – | – | – | 2.60 | |
| Present study | 0 | 0 | 0.71 | 0 | 0 | 0 | 0 | 0 | 0.71 |
As previously noted, TPMT allele frequencies vary considerably among populations and even within individual countries. An Israeli study evaluating TPMT*3A and *3C across several ethnic groups including Arabs, Jews, Druze, Kurds, and individuals of African descent reported the highest prevalence of TPMT polymorphisms in the Druze population (80.4% wild-type, 17.4% heterozygous, and 2.2% homozygous variants). In contrast, Jewish and Kurdish populations exhibited much lower frequencies, with 98.2% wild-type and 1.6% heterozygous genotypes. TPMT*3C predominated among individuals of African descent (5.3%), whereas TPMT*3A was the most frequent variant in the remaining groups (26). In the United States, sequencing-based analysis reported allele frequencies of 4.5% for TPMT*3A and 0.7% for TPMT*3C (27). A Palestinian study of 56 ALL patients identified only one TPMT*3A carrier (allele frequency 0.89%) (28), while in Japan TPMT*3C occurred at a frequency of 0.3% (29). The 0.71% allele frequency observed in our cohort is therefore consistent with previous reports.
4.2 Rare TPMT variants and inter-ethnic differences
Recent studies have increasingly focused on rare TPMT variants. In our cohort, four rare alleles (*4, *7, *8, and *10) were screened in 19 patients with low enzyme activity or myelosuppression, but none were detected. Similarly, a Polish study using HRMA reported TPMT*3A at 3.28%, whereas rare alleles (*30, *31, and *15) each occurred at a frequency of only 0.18% (30). In Korea, sequencing of 900 healthy individuals identified TPMT*3C in 2.8% and rare variants (*6, *16, and *32) in a combined 0.6% (31). Overall, TPMT deficiency demonstrates marked ethnic variability. TPMT*3A and *3B are most common in Caucasian (3.36% and 0.07%) and Hispanic populations (2.9% and 0.1%) (32–33), whereas TPMT*3C predominates in Asian and African populations, with reported frequencies of 2.21% and 4.57%, respectively (34).
4.3 TPMT enzyme phenotype evaluation
To evaluate TPMT phenotype, plasma enzyme concentrations were measured. For patients receiving long-term 6-MP maintenance therapy, therapeutic monitoring of TPMT activity and drug metabolites is recommended at weeks 14, 24, 34, 44, and 54 after treatment initiation (35). A U.S. study reported substantial ethnic differences in TPMT phenotype, with Americans showing the highest proportion of intermediate or low enzyme activity (10.3%) and the lowest methylated metabolite levels (0.33%), suggesting an increased risk of 6-MP toxicity (27). Asians had the lowest proportion of reduced TPMT activity (4.5%), whereas Caucasian and Hispanic populations showed intermediate activity in 7.45% of cases (36, 27). Reis et al. also demonstrated a trimodal distribution of TPMT activity, with 90% of individuals showing activity >11.3 units/μm³ RBCs, 9.8% between 5 and 11.3 units, and 0.3% exhibiting near-complete deficiency (<0.17 units) (37).
In the present study, TPMT activity was measured by ELISA in 70 patients. Eight (11.4%) had low enzyme activity, whereas 62 (88.6%) showed intermediate or high activity. Although direct comparison with metabolite concentrations would strengthen interpretation, our results were generally consistent with previous studies, showing no significant association between metabolite levels and enzyme activity (P = 0.81, OR [95% CI] = 1.25 [0.45–3.1]). Genotype–phenotype analysis likewise showed no significant association (P = 1, OR [95% CI] = 1). Among 69 patients with the wild-type genotype, seven had low enzyme activity, while one heterozygous TPMT*3B/*1 carrier also demonstrated low activity. Similar genotype–phenotype variability has been reported by Schaeffeler et al., who studied 1,214 German Caucasians and found genotype frequencies of TPMT*3A (4.4%), TPMT*3C (0.4%), and TPMT*2 (0.2%), alongside phenotypic distributions of 0.6% deficient, 9.9% intermediate, and 89.5% normal activity (38). Among 17 individuals with initial genotype–phenotype discordance, sequencing identified rare variants in four patients, including TPMT*9 (n = 2), TPMT*16 (n = 1), TPMT*17 (n = 1), and TPMT*18 (n = 1), increasing concordance from 86% to 89%. In the remaining 13 patients, undetected intronic or regulatory variants, including promoter mutations, may explain the reduced enzyme activity. Conversely, seven heterozygous patients exhibited unexpectedly high TPMT activity, suggesting the influence of physiological or environmental factors. Given the large size of the TPMT gene (34 kb, 10 exons), additional rare and population-specific variants are likely. TPMT*2 is more prevalent in Caucasians, whereas TPMT*6 and TPMT*8 occur more frequently in African and Asian populations (36, 27). Although TPMT*8 was initially considered rare, its frequency reaches 5.1–5.3% in African populations (34). These observations suggest that rare alleles may contribute to the genotype–phenotype discordance observed in our cohort. Although four uncommon variants (TPMT*4, *7, *8, and *10) were investigated, larger studies using comprehensive sequencing approaches are needed to define the full spectrum of TPMT polymorphisms in the Iranian population. Residual discordance may also reflect physiological variation or environmental influences (35).
4.4 Relationship between 6-MP side effects and TPMT phenotype/genotype
Pharmacogenetic studies in acute lymphoblastic leukemia have consistently shown that thiopurine S-methyltransferase (TPMT) activity influences the toxicity of 6-MP. Previous studies by Pui et al. (39) and Kim et al. (40) demonstrated that, despite favorable treatment outcomes, drug resistance and treatment failure related to adverse effects and myelosuppression occur in more than 20% of ALL patients. Leukopenia and neutropenia were reported in 7.28% of patients, comparable to the frequencies observed in our cohort (5.28% and 8.32%, respectively). Although Kim et al. found no significant association between TPMT polymorphisms and myelosuppressive toxicity, our findings suggest that reduced TPMT activity is associated with an increased risk of hematologic toxicity. Among eight patients with low TPMT activity, five developed leukopenia, whereas only three maintained normal white blood cell counts. In contrast, leukopenia occurred in 15 of 62 patients with intermediate or high TPMT activity. Likewise, neutropenia developed in six of eight patients with low TPMT activity compared with 17 of 62 patients with intermediate or high activity (P = 0.02). These findings indicate a significant relationship between reduced TPMT activity and susceptibility to leukopenia and neutropenia. Similar observations have been reported by Halvaty et al. in a cohort of 220 Slovak patients treated with 6-MP, in which 93% carried the wild-type TPMT genotype, 6% were heterozygous, and 1% were homozygous for mutant alleles. Patients with heterozygous or homozygous variants and intermediate TPMT activity experienced markedly greater reductions in white blood cell counts than those with wild-type genotypes and high enzyme activity (87% vs. 30%), supporting the value of TPMT genotype–phenotype assessment before treatment (41). These findings are consistent with our results and previous reports emphasizing the clinical utility of pre-treatment TPMT testing (38). Gisbert et al. evaluated 99 patients with inflammatory bowel disease receiving 6-MP and found that 93% had the wild-type TPMT genotype with high enzyme activity, whereas 7% carried polymorphic alleles associated with reduced activity. Bone marrow suppression occurred in four patients, although only one had low TPMT activity, indicating that hematologic toxicity is not exclusively determined by TPMT status (42).
Nevertheless, in our study, low plasma TPMT concentrations were significantly associated with 6-MP-induced myelosuppression, specifically leukopenia (<2000 WBC/µL) and neutropenia (<1000 neutrophils/µL). In contrast, no significant association was observed between TPMT activity and hepatotoxicity. TPMT*1/TPMT*3B was the most frequently detected polymorphism (1%). Adam et al. investigated 66 French patients with ALL and reported that elevated 6-MP metabolite concentrations were associated with hepatotoxicity in 95.7% of cases (43). In contrast, our study found no significant relationship between TPMT activity and elevated AST or ALT levels. Similarly, Xin et al. demonstrated that myelosuppressive toxicity differed significantly between patients with normal and reduced TPMT activity (P < 0.05), whereas hepatotoxicity showed no significant association with TPMT status, further supporting our findings (44).
5. Conclusion
Our findings demonstrate that reduced TPMT activity is significantly associated with an increased risk of 6-MP-induced myelosuppression, particularly leukopenia and neutropenia, whereas no significant association was observed with hepatotoxicity. Although common TPMT polymorphisms showed limited correlation with enzyme activity, the identification of rare variants improved genotype–phenotype concordance, highlighting the contribution of uncommon and potentially population-specific alleles to thiopurine metabolism. These findings support the clinical value of pre-treatment TPMT phenotyping together with comprehensive genotyping, including both common and rare TPMT variants, to individualize 6-MP dosing, reduce treatment-related toxicity, and improve the safety of thiopurine therapy in pediatric patients with acute lymphoblastic leukemia.
6. Declarations
6.1 Acknowledgments
The authors would like to express their sincere gratitude to the children and their parents for their participation and cooperation in this study. The authors also thank the physicians, nurses, and staff of the Hematology Department at Mofid Children's Hospital for their valuable assistance and support throughout the study.
6.2 Ethical Considerations
This study was approved by the Ethics Committee of Zanjan University of Medical Sciences.
All study procedures were conducted in accordance with the ethical principles of the Declaration of Helsinki and its subsequent amendments.
6.3 Authors' Contributions
Y.M., S.A., and M.J. contributed to the study conception and design, developed the methodology, and drafted the manuscript. S.Z. and S.R. contributed to the study conception, software development, formal data analysis, and critical revision of the manuscript.
All authors reviewed, approved, and agreed to the published version of the manuscript.
6.4 Conflict of Interest
The authors declare that they have no conflicts of interest.
6.5 Fund or Financial Support
This study was derived from an MSc dissertation and was financially supported by the Deputy for Research and Technology of Zanjan University of Medical Sciences under Grant No. A-11-190-5.
6.6 Using Artificial Intelligence Tools (AI Tools)
The authors used artificial intelligence (AI) tools to assist in drafting and improving the language of selected sections of the manuscript.
Type of Study: Original Research Article |
Subject:
Medical Biology
Received: 2026/01/24 | Accepted: 2026/03/17 | Published: 2026/06/29
Received: 2026/01/24 | Accepted: 2026/03/17 | Published: 2026/06/29
References
1. Pagliaro L, Chen SJ, Herranz D, Mecucci C, Harrison CJ, Mullighan CG, et al. Acute lymphoblastic leukaemia. Nat Rev Dis Primers. 2024;1 0(1):41. [DOI:10.1038/s41572-024-00525-x] [PMID]
2. Inaba H, Pui CH. Advances in the diagnosis and treatment of pediatric acute lymphoblastic leukemia. J Clin Med. 2021; 10(9):1926. [DOI:10.3390/jcm10091926] [PMID] [PMCID]
3. Terwilliger T, Abdul-Hay M. Acute lymphoblastic leukemia: a comprehensive review and 2017 update. Blood Cancer J. 2017; 7(6):e577. [DOI:10.1038/bcj.2017.53] [PMID] [PMCID]
4. Ian X, Wu J, Liao Z, Wu Y, Hu R. Prevalence of symptoms in children with acute lymphoblastic leukaemia: a systematic review and meta-analysis. BMC Cancer. 2023; 23:1113. [DOI:10.1186/s12885-023-11581-z] [PMID] [PMCID]
5. Alaggio R, Amador C, Anagnostopoulos I, Au WY, Chan JKC, Chen BJ, et al. The 5th edition of the World Health Organization Classification of Haematolymphoid Tumours: lymphoid neoplasms. Leukemia. 2022; 36:1720-1748. [DOI:10.1038/s41375-022-01620-2] [PMID]
6. Kantarjian H, Thomas D, Jabbour E. Acute lymphocytic leukaemia. Lancet. 2025; 405(10344):1234-1245. [DOI:10.1016/S0140-6736(25)00864-5] [PMID]
7. Ataseven E, Yılmaz S, Yıldız Y, Kurugöl Z, Kantar M. Thiopurine S-methyltransferase gene polymorphism and drug-related toxicity in children treated for acute leukemia and non-Hodgkin lymphoma. J Pediatr Res. 2022; 9(1):1-6 [DOI:10.4274/jpr.galenos.2021.35492]
8. Relling MV, Schwab M, Whirl-Carrillo M, Suarez-Kurtz G, Pui CH, Stein CM, et al. Clinical Pharmacogenetics implementation consortium (CPIC) guideline for thiopurine dosing based on TPMT and NUDT15 genotypes: 2024 update. Clin Pharmacol Ther. 2024;115(2):232-43.
9. Lubis IS, Anggadiredja K, Artarini AA, Sari NM, Suryawan N, Zazuli Z. NUDT15 pharmacogenetics in acute lymphoblastic leukemia: synthesizing progress for personalized thiopurine therapy. Med Sci (Basel). 2025;13(3):112. [DOI:10.3390/medsci13030112] [PMID] [PMCID]
10. Li L, Atkinson N, Crews KR, Molinelli AR. Determination of thiopurine S-methyltransferase (TPMT) activity in human erythrocytes by liquid chromatography-tandem mass spectrometry (LC-MS/MS). In: Schaeffeler E, Schwab M, editors. Pharmacogenetics: Methods and Protocols. New York (NY): Humana Press; 2024. p. 465-472. [DOI:10.1007/978-1-0716-3541-4_43] [PMID]
11. Guo HL, Zhang Y, Li X, Lin J, Zhang L, Sun Y, et al. Optimizing thiopurine therapy in children with acute lymphoblastic leukemia: a promising MINT sequencing strategy and therapeutic DNA-TG monitoring. Front Pharmacol. 2022; 13:941182. [DOI:10.3389/fphar.2022.941182] [PMID] [PMCID]
12. Dickson AL, Daniel LL, Zanussi J, Plummer WD, Wei WQ, Liu G, et al. TPMT and NUDT15 variants predict discontinuation of azathioprine for myelotoxicity in patients with inflammatory disease: real-world clinical results. Clin Pharmacol Ther. 2022; 111(1):263-71. [DOI:10.1002/cpt.2428] [PMID] [PMCID]
13. Ali AM, Damin AS, Mustafa AM, Engidawork E, Howe R, Abula T, et al. Genetic variants of genes involved in thiopurine metabolism and 6-mercaptopurine-related toxicities in acute lymphoblastic leukemia. Front Pharmacol. 2023; 14:1159307. [DOI:10.3389/fphar.2023.1159307] [PMID] [PMCID]
14. Relling MV, Schwab M, Whirl-Carrillo M, Suarez-Kurtz G, Pui Ch, Stein Ch, et al. Clinical Pharmacogenetics Implementation Consortium guideline for thiopurine methyltransferase genotype and thiopurine dosing: 2024 update. Clin Pharmacol Ther. 2024; 115(2):232-43.
15. Brouwer C, Ronney A, Abreu D, Lambooy L, Ament K, Riet P, et al. Thiopurine methyltransferase in acute lymphoblastic leukaemia: biochemical and molecular biological aspects. Eur J Cancer. 2005; 41:613-23. [DOI:10.1016/j.ejca.2004.10.027] [PMID]
16. El-Kaffasha D, Hassab H, AbouZeida A, Swelem R, Tahoun M, et al. TPMT gene polymorphism detection by conventional PCR in pediatric acute lymphoblastic leukemia and its toxic effect. Egypt J Haematol. 2014; 3 9:86-90. [DOI:10.4103/1110-1067.139775]
17. Wang J, Wang X, Hao G, Cheng Y, Lu H, Suo T. Relationship between NUDT15 gene polymorphism and tolerance to treatment with 6-mercaptopurine in children with acute lymphoblastic leukemia. J Leuk Lymphoma. 2022; 31(5):286-89.
18. Pratt VM, Cavallari LH, Fulmer ML, Gaedigk A, Hachad H, Ji Y, Kalman L, et al. TPMT and NUDT15 Genotyping Recommendations: A Joint Consensus Recommendation of the Association for Molecular Pathology, Clinical Pharmacogenetics Implementation Consortium, College of American Pathologists, Dutch Pharmacogenetics Working Group of the Royal Dutch Pharmacists Association, European Society for Pharmacogenomics and Personalized Therapy, and Pharmacogenomics Knowledgebase. J Mol Diagn. 2022;24 (10):1051-63. [DOI:10.1016/j.jmoldx.2022.06.007] [PMID] [PMCID]
19. Jantararoungtong T, Wiwattanakul S. TPMT*3C as a predictor of 6-mercaptopurine-induced myelotoxicity in Thai children with acute lymphoblastic leukemia. J Pers Med. 2021; 11(8):783. [DOI:10.3390/jpm11080783] [PMID] [PMCID]
20. Du S, Zhang Y, Liu W, Mao M , Chen M, Zhang R, et al. Association of NUDT15 gene polymorphism with mercaptopurine-induced adverse reactions in children with acute lymphoblastic leukemia. Haematologica. 2024; 109(5):1234-42.
21. Khera S, Trehan A, Bhatia P, Singh M , Bansal D, Varma N, et al. Prevalence of TPMT, ITPA and NUDT15 genetic polymorphisms and their relation to 6-mercaptopurine toxicity in North Indian children with acute lymphoblastic leukemia. Cancer Chemother Pharmacol. 2019; 83 (2):341-48. [DOI:10.1007/s00280-018-3732-3] [PMID]
22. Azad M, Kaviani S, Soleymani M, Nourouzinia M, Hajfathali A. Common polymorphisms of thiopurine S-methyltransferase (TPMT) in the Iranian population. Yakhteh Med J. 2009; 11(3):311-16.
23. Bahari A, Hashemi M, Bari Z, Moazeni-Roodi A, Kaykhaei MA, Narouie B. Frequency of thiopurine S-methyltransferase (TPMT) alleles in the southeast Iranian population. Nucleosides Nucleotides Nucleic Acids. 2010; 2 9 (3):237-44. [DOI:10.1080/15257771003720418] [PMID]
24. Moini M, Ghaderi F, Sagheb MM, Tavassoli AR, Azarpira N, Darai M, et al. The frequency and distribution of thiopurine S-methyltransferase alleles in the south Iranian population. Mol Biol Rep. 2012; 39(4):4581-4587. [DOI:10.1007/s11033-011-1248-6] [PMID]
25. El-Kaffash D, Hassab H, Abou Zeid A. TPMT gene polymorphism detection by conventional PCR in pediatric acute lymphoblastic leukemia and its toxic effect. Egypt J Haematol. 2014; 39 (2):86-90. [DOI:10.4103/1110-1067.139775]
26. Ronen O, Bar Cohen S, Rund D. Evaluating frequencies of thiopurine S-methyltransferase (TPMT) variant alleles in Israeli ethnic subpopulations using DNA analysis. Isr Med Assoc J. 2010; 12: 721-725.
27. Almoguera B, Vazquez L, Connolly J, et al. Imputation of TPMT defective alleles for the identification of patients with high-risk phenotypes. Front Genet. 2014;5: 1-7. [DOI:10.3389/fgene.2014.00096] [PMID] [PMCID]
28. Ayesh B, Harb W, Abed A. Thiopurine methyltransferase genotyping in Palestinian childhood acute lymphoblastic leukemia patients. BMC Hematol. 2013; 13(1):3. [DOI:10.1186/2052-1839-13-3] [PMID] [PMCID]
29. Kubota T, Chiba K. Frequencies of thiopurine S-methyltransferase mutant alleles (TPMT*2, *3A, *3B and 3C) in 151 healthy Japanese subjects and inheritance of TPMT3C in the family of a propositus. Br J Clin Pharmacol. 2001; 51:475-77. [DOI:10.1046/j.1365-2125.2001.01371.x] [PMID] [PMCID]
30. Skrzypczak-Zielińska M, Boruń P, Milanowska K, Zakerska O, Zachwieja A, Plawski A,et al. High-resolution melting analysis of the TPMT gene: a study in the Polish population. Genet Test Mol Biomarkers. 2013; 17(2):153-59. [DOI:10.1089/gtmb.2012.0192] [PMID] [PMCID]
31. Kim H, Lee SS, Lee M, Kim JW, Kim YK, Kim MJ, et al. Complete sequence-based screening of TPMT variants in the Korean population. Pharmacogenet Genomics. 2015; 25(3):143-46. [DOI:10.1097/FPC.0000000000000117] [PMID]
32. Appell ML, Berg J, Duley J, Evans WE, Kennedy MA, Lennard L, et al. Nomenclature for alleles of the thiopurine methyltransferase gene. Pharmacogenet Genomics. 2013; 23(4):242-48. [DOI:10.1097/FPC.0b013e32835f1cc0] [PMID] [PMCID]
33. Wang L, Pelleymounter L, Weinshilboum R, Johnson JA, Hebert JM, Altman RB, et al. Very important pharmacogene summary: thiopurine S-methyltransferase. Pharmacogenet Genomics. 2010; 20(6):401-405. [DOI:10.1097/FPC.0b013e3283352860] [PMID] [PMCID]
34. Gallardo-Cóndor J, Cevallos-Robalino D, Rodríguez-Acosta A, et al. Population-specific distribution of TPMT deficiency variants and ancestry proportions in Ecuadorian ethnic groups: towards personalized medicine. Pharmacogenomics J. 2023; 23(1):1-10. [DOI:10.2147/TCRM.S432856] [PMID] [PMCID]
35. Zimdahl Kahlin A, Helander S, Skoglund K, Söderkvist P, Mårtensson L, Lindqvist Appell M. Comprehensive study of thiopurine methyltransferase genotype, phenotype, and genotype-phenotype discrepancies in Sweden. Biochem Pharmacol. 2019;164:263-272. [DOI:10.1016/j.bcp.2019.04.020] [PMID]
36. Oliveira E, Quental S, Alves S, Amorim A, Prata MJ. Do the distribution patterns of polymorphisms at the thiopurine S-methyltransferase locus in sub-Saharan populations need revision? Hints from Cabinda and Mozambique. Eur J Clin Pharmacol. 2007; 63(7):703-706. [DOI:10.1007/s00228-007-0310-8] [PMID]
37. Reis M, Santoro A, Suarez-Kurtz G. Thiopurine methyltransferase phenotypes and genotypes in Brazilians. Pharmacogenetics. 2003; 13(6):371-373. [DOI:10.1097/00008571-200306000-00009] [PMID]
38. Schaeffeler E, Fischer C, Brockmeier D, Wernet D, Moerike K, Eichelbaum M, et al. Comprehensive analysis of thiopurine S-methyltransferase phenotype-genotype correlation in a large population of German Caucasians and identification of novel TPMT variants. Pharmacogenetics. 2004; 14(7):407-417. [DOI:10.1097/01.fpc.0000114745.08559.db] [PMID]
39. Pui CH, Robison LL, Look AT. Acute lymphoblastic leukaemia. Lancet. 2008; 371(9617):1030-43. [DOI:10.1016/S0140-6736(08)60457-2] [PMID]
40. Kim H, You S, Park Y, Choi JY, Ma Y, Hong KT,et al. Interplay between IL6 and CRIM1 in thiopurine intolerance due to hematological toxicity in leukemic patients with wild-type NUDT15 and TPMT. Sci Rep. 2021;11:9676. [DOI:10.1038/s41598-021-88963-5] [PMID] [PMCID]
41. Hlavaty T, Batovsky M, Balakova D, Pav I, Celec P, Gregus M,et al. The impact of thiopurine S-methyltransferase genotype on adverse drug reactions to azathioprine in patients with inflammatory bowel disease. Bratisl Lek Listy. 2013; 114(4):199-205. [DOI:10.4149/BLL_2013_042] [PMID]
42. Gisbert JP, Niño P, Rodrigo L, Cara C, Guijarro LG. Thiopurine methyltransferase (TPMT) activity and adverse effects of azathioprine in inflammatory bowel disease: long-term follow-up study of 394 patients. Am J Gastroenterol. 2006; 101(12):2769-2776. [DOI:10.1111/j.1572-0241.2006.00843.x] [PMID]
43. Adam de Beaumais T, Fakhoury M, Medard Y, Azougagh S, Zhang D, Yakouben K, et al. Determinants of mercaptopurine toxicity in paediatric acute lymphoblastic leukemia maintenance therapy. Br J Clin Pharmacol. 2011; 71(4):575-84. [DOI:10.1111/j.1365-2125.2010.03867.x] [PMID] [PMCID]
44. Xin HW, Xiong H, Wu XC, Li Q, Xiong L , Yu A, et al. Relationships between thiopurine S-methyltransferase polymorphism and azathioprine-related adverse drug reactions in Chinese renal transplant recipients. Eur J Clin Pharmacol. 2009; 65(3):249-55. [DOI:10.1007/s00228-008-0589-0] [PMID]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |
Copyright Policy
Journal of Advances in Medical and Biomedical Research by Zanjan University of Medical Sciences is licensed under CC BY-NC 4.0