Sun, Sep 20, 2026
[Archive]
Volume 34, Issue 3 (May & June 2026)
J Adv Med Biomed Res 2026, 34(3): 213-219 |
Back to browse issues page

Ethics code: IR.TUMS.IKHC.REC.1399.145


Download citation:
BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:


BibTeX | RIS | EndNote | Medlars | ProCite | Reference Manager | RefWorks
Send citation to:
Jalili N, Abtahi H, Rahimi B. Phenotype evaluation in patients with obstructive sleep apnea (AHI>15). J Adv Med Biomed Res 2026; 34 (3) :213-219
URL: http://journal.zums.ac.ir/article-1-7961-en.html
URL: http://journal.zums.ac.ir/article-1-7961-en.html


1- Department of internal medicine, Zanjan university of medical science. Zanjan, Iran , dr.nooshinjalili@zums.ac.ir
2- Advanced thoracic research, Tehran University of Medical Sciences
3- Advanced thoracic research, Tehran University of Medical Sciences, Tehran. Iran
2- Advanced thoracic research, Tehran University of Medical Sciences
3- Advanced thoracic research, Tehran University of Medical Sciences, Tehran. Iran
Full-Text [PDF 320 kb]
(37 Downloads)
| Abstract (HTML) (436 Views)
Table 3. The frequency and percentage of surgical compliance and instrument preparation in patients with OSA.
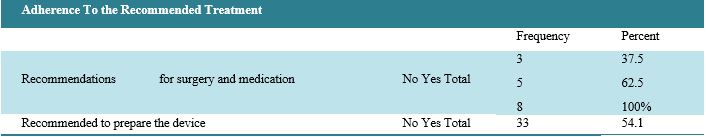
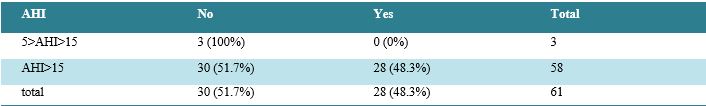
Table 4. Frequency and percentage of patients with OSA who purchased the instrument based on the AHI group.
Among device users, 27 of 28 patients used the device for ≥4 hours per night. Additionally, 25 patients (89.2%) continued therapy for more than three months. Patients with an AHI <5 demonstrated slightly better long‑term adherence, with all using the device ≥4 hours per night and the majority continuing therapy beyond three months. A significant association was observed between ESS score and AHI (Figure 1).
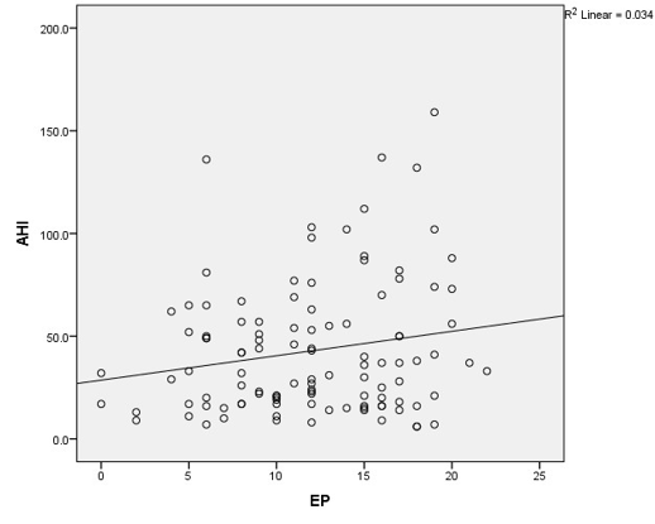
Figure 1. Relationship between Ep and AHI. (Prepared by Authors, 2026).
4. Discussion
Obstructive sleep apnea is the most common sleep-disordered breathing disorder, characterized by repeated obstruction of the upper airways (pharynx) during sleep, which can lead to decreased arterial oxygen saturation or arousal, after which respiratory status returns to normal by increasing breathing amplitude and depth (11). Therefore, this study aimed to evaluate the phenotype in patients suffering from obstructive sleep apnea with AHI> 15. The study consisted of 59 females and 53 males (112 patients). Pelosi et al. Also studied 138 patients consisting of 54.4% male and 45.6% female (12). In the Ernas study, the proportion was 54.8% male and 45.2% female (13). Previous studies have reported that the prevalence of the disease varies by sex, and the Male/Female ratio has been 3.1 to 5.1 and even 8.1 to 10.1 (14). In our study, the gender percentage differed from some studies, but the higher percentage of women in this study may be due to the choice of patients in the sleep clinic.
In the present study, the mean age of the patients was 51±13.4 years. Pelosi et al reported a mean age of 58 ± 11 years (12), while a study by Ernas et al reported a mean age of 54.7 (13). In 2012, Dipoosu et al. conducted a study on 488 people with a mean age of 53 ± 11 (15).
The mean age obtained in our study was similar to that in other studies. Furthermore, 99.1% of the patients in this study had no history of smoking or psychotropic substance use. Olayemi et al. (16) and Ernas et al. (13) reported that 8% and 16.6% of patients had a history of smoking, respectively, which may be due to cultural issues. In this study, 32.1% of OSA patients had a history of HTN. Ernas et al, reported a history of HTN in 30.6% of subjects (13). Another study reported HTN in 23.5% (16), which was similar to this study.
The mean BMI of patients in the present study was 31.84 ± 7.55. In other studies, BMI was reported as 33.1 ± 6 (12), 28.2 ± 5 (13) and 30.2 ± 5 (14). However, some studies reported BMI above 42.6 (17) and below 23.9 (16). BMI in this study was higher in women than in men (34 to 29.3), which was similar to the results of other studies. In one study, women had a BMI of 31.39 ± 7.12 versus 29.82 in men (P> 0.001) (13). The mean neck circumference of patients in the present study was 40.83. In other studies, similar results were reported where the mean neck circumference of patients was reported to be 42.4 ±3.4 (17) and 43.9 (13); these findings are similar to this study. In comparison between men and women, the BMI and neck circumference of women were lower than those of men.
The mean ODI in the present study was 36.1, which was higher in women than in men. In another study, women experienced a more severe ODI. In one study, the mean ODI in men and women was reported as 8.6 and 4.7, respectively, which showed a statistically significant difference (P = 0.001) (18). The mean EP worth Scale in the present study was 11.98 ± 5, which was similar to Kim's study with EP of 5.6±5 (19). The mean AHI of patients was 43.14±31.96 in the current study. In other studies, AHI was reported to be 45.5 ± 26.56 (12) and 38.4 (20), which were similar to the results obtained in our study. In another study, AHI was reported in men and women at 7.7 ± 5.2l and 10.4 ± 9.5 (P <0.001), which differed from our results, but like the results of our study, AHI was more commonly reported in men (13).
Among 112 patients, 61 were recommended to use positive airway pressure, of which 28 (45.9%) provided the instrument, and 27 (96.4%) of the 28 patients who provided the instrument used the instrument for at least 4 hours at night, and 25 patients (89.2%) continued to use the instrument for more than 3 months. Of the 28 patients who provided the instrument and all had AHI above 15, 15 had apnea below 5 and 13 had apnea above 5. Of the 15 people with apnea less than 5, all used the instrument for more than 4 hours, and 14 people continued its use after 3 months. The results of a study also showed that 81% of people used CPAP for at least 2 hours and 70% for more than 4 hours (21). Another study comprising 69 patients diagnosed with OSA by polysomnography between 2002 and 2007 reported that 41 patients (59.4%) were satisfied with positive airway pressure (PAP) therapy after 1 month, while 34.7% continued using PAP for more than 3 months. (19). The results of another study showed that 46% of patients treated with continuous positive airway pressure (CPAP) continued to use the device for at least 4 hours per night, while at least 70% continued its use at night (22). Another study reported that 34.7% of patients continued treatment for more than 3 months (20). Comparison of these findings suggests that device adherence among our patients was comparable to that reported in previous studies. In this study, compliance was compared based on age, BMI, AHI, smoking, and alcohol consumption. AHI was 47.6 in the group with good compliance and 40.52 in the group with low compliance (P = 0.2). Also, a negative relationship between ESS and night time use has been observed, and the type of mask does not affect compliance (12).
Another study was performed to identify the risk factors for treatment failure and lack of compliance in patients with the sleep apnea/hypopnea syndrome (SAHS) treated by CPAP, where 131 of 949 identified patients underwent follow-up, and compliance was at least 4 hours per night in 70% of the nights, of which 48 patients did not have CPAP treatment compliance. In aforementioned study, low AHI was identified as a risk factor for lack of compliance (P = 0.004), but no relationship was found between compliance and other factors such as age, Oxygen saturation (O2Sat), sex, alcohol use, and ESS (17). Most studies in Europe have reported 46-80% compliance (22).
Some other studies have emphasized the lack of association between primary AHI and compliance (23) and also noted that improvement in sleep quality at the start of CPAP treatment was the most important predictor of its use. Regular follow-up and effective interventions also increased compliance (24). Conversely, some studies have reported a positive effect of AHI on compliance (25).
5. Conclusion
This study demonstrates that phenotype-based classification enhances the clinical utility of CPAP therapy in patients with moderate to severe OSA. Among patients with AHI >15, those with greater hypoxic burden and lower apnea index exhibited higher adherence to positive airway pressure therapy, both in nightly usage and long‑term continuation.
These findings reinforce the limitation of relying solely on AHI to guide treatment decisions and highlight the importance of incorporating apnea index and hypoxemia‑related parameters into routine clinical assessment. A phenotype‑driven approach may improve patient selection for CPAP therapy, optimize resource allocation, and ultimately enhance adherence and clinical outcomes. Future studies with larger cohorts and longitudinal follow-up are warranted to validate these findings and to further refine phenotype‑guided treatment algorithms. Integrating simple polysomnographic markers into personalized OSA management holds promise for improving both patient experience and therapeutic effectiveness.
6. Declarations
6.1 Acknowledgments
We would like to sincerely thank the sleep testing department of Imam Khomeini Hospital for their cooperation in implementing the project.
6.2 Ethical Considerations
The study was approved by the Research Council of the Medical School and the institutional ethics committee (Ethical approval code: IR.TUMS.IKHC.REC.1399.145). Written informed consent was obtained from all participants. Patient confidentiality was strictly maintained in accordance with the Declaration of Helsinki and local ethical guidelines.
6.3 Authors' Contributions
project management and validation: Dr Hamidreza Abtahi, research and writing Nooshin Jalili, drafting, review, and editing, supervision: Besharat Rahimi
6.4 Conflict of Interest
The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
6.5 Fund or Financial Support
This research received no external funding
6.6 Using Artificial Intelligence Tools (AI Tools)
The authors were not utilized AI Tools.
Full-Text: (20 Views)
ABSTRACT
Background & Objective: Obstructive sleep apnea (OSA) is a common sleep-related breathing disorder characterized by recurrent upper airway obstruction during sleep, leading to arousal and reduced arterial oxygen saturation. This study compared patients with an apnea index <5 and >5 among individuals with moderate-to-severe OSA (AHI >15).
Materials & Methods: This cross-sectional study was conducted at Imam Khomeini Hospital Sleep Laboratory in Tehran, Iran, between 2023 and 2024. Demographic and clinical characteristics of all the patients were recorded. Sleep-related variables included excessive daytime sleepiness assessed using the Epworth Sleepiness Scale, snoring, oxygen desaturation index (ODI), apnea index, apnea hypopnea index (AHI), and the duration of nocturnal oxygen saturation below 90%. Prescribed treatments, including medication, surgery, continuous positive airway pressure (CPAP), or bilevel positive airway pressure (BiPAP), treatment adherence, and the duration of device use were also assessed. Data were analyzed using SPSS version 22.
Results: Among 112 patients, 52.7% were female and 47.3% were male, with a mean age of 51±13.4 years. Overall, 32.1% had hypertension. The mean BMI was 31.84±7.55, mean neck circumference was 40.83 cm, mean ODI was 36.1, mean Epworth Sleepiness Scale score was 11.98±5, and mean AHI was 43.14±31.96. BMI and neck circumference were lower in women, whereas ODI was higher in women. Among 28 patients who received a device, 15 had an apnea index <5 and 13 had an index >5. All patients in the <5 group used the device for >4 hours, compared with 12 patients in the >5 group.
Conclusion: Our findings indicate that addressing barriers to obtaining and using treatment devices may improve treatment adherence. Although a considerable number of patients did not obtain the prescribed device, adherence among those who did was generally favorable, with most patients using the device for at least 4 hours per night.
Keywords: Phenotype, Obstructive sleep apnea, Apnea Hypopnea Index
Background & Objective: Obstructive sleep apnea (OSA) is a common sleep-related breathing disorder characterized by recurrent upper airway obstruction during sleep, leading to arousal and reduced arterial oxygen saturation. This study compared patients with an apnea index <5 and >5 among individuals with moderate-to-severe OSA (AHI >15).
Materials & Methods: This cross-sectional study was conducted at Imam Khomeini Hospital Sleep Laboratory in Tehran, Iran, between 2023 and 2024. Demographic and clinical characteristics of all the patients were recorded. Sleep-related variables included excessive daytime sleepiness assessed using the Epworth Sleepiness Scale, snoring, oxygen desaturation index (ODI), apnea index, apnea hypopnea index (AHI), and the duration of nocturnal oxygen saturation below 90%. Prescribed treatments, including medication, surgery, continuous positive airway pressure (CPAP), or bilevel positive airway pressure (BiPAP), treatment adherence, and the duration of device use were also assessed. Data were analyzed using SPSS version 22.
Results: Among 112 patients, 52.7% were female and 47.3% were male, with a mean age of 51±13.4 years. Overall, 32.1% had hypertension. The mean BMI was 31.84±7.55, mean neck circumference was 40.83 cm, mean ODI was 36.1, mean Epworth Sleepiness Scale score was 11.98±5, and mean AHI was 43.14±31.96. BMI and neck circumference were lower in women, whereas ODI was higher in women. Among 28 patients who received a device, 15 had an apnea index <5 and 13 had an index >5. All patients in the <5 group used the device for >4 hours, compared with 12 patients in the >5 group.
Conclusion: Our findings indicate that addressing barriers to obtaining and using treatment devices may improve treatment adherence. Although a considerable number of patients did not obtain the prescribed device, adherence among those who did was generally favorable, with most patients using the device for at least 4 hours per night.
Keywords: Phenotype, Obstructive sleep apnea, Apnea Hypopnea Index
1. Introduction
Breathing and sleep are both fundamental to human survival. On average, approximately one‑third of life is spent sleeping, during which physiological changes may predispose individuals to various sleep disorders (1). Obstructive sleep apnea is one of the most common sleep -related breathing disorders. It is estimated to affect approximately 4% of men and 2% of women in the general population (2). OSA results from recurrent upper airway obstruction during sleep and is associated with intermittent hypoxemia and sleep fragmentation (2). Common clinical manifestations of OSA include obesity, excessive daytime sleepiness, loud snoring, and a range of neurocognitive
and psychological impairments (3). The prevalence of OSA increases with age and is higher among individuals with obesity (3). In adults, apnea is defined as complete cessation of airflow for at least 10 seconds, accompanied by a ≥90% reduction in airflow from baseline. Complete upper airway collapse results in apnea, whereas partial obstruction leads to hypopnea (4).
OSA is characterized by persistent respiratory effort during sleep, which can be identified by paradoxical thoracoabdominal movements using thoracic and abdominal respiratory inductance plethysmography (5).
The average number of apneas and hypopneas per hour of sleep, known as the Apnea–Hypopnea Index (AHI), is widely used to determine disease severity (6). Polysomnography (PSG) is used to diagnose OSA (7). Classic clinical features include snoring and excessive daytime sleepiness; however, Clinical manifestations are often heterogeneous, and some patients with moderate to severe OSA may show few symptoms.
Given the heterogeneity and complexity of OSA, AHI alone may be insufficient for comprehensive patient classification (8). Increasing evidence suggests that OSA consists of distinct phenotypes and endotypes influenced by multiple anatomical and non‑anatomical factors. Identification of clinically relevant phenotypes may facilitate personalized, mechanism‑based treatment and improve long‑term adherence to therapy, particularly continuous positive airway pressure (CPAP) (9).
CPAP therapy, the mainstay non‑invasive treatment for OSA, delivers positive airway pressure to prevent upper airway collapse during sleep. Despite its proven efficacy, patient acceptance and long‑term adherence remain suboptimal, with reported adherence rates of approximately 50% (10). OSA leads to decreased arterial oxygen saturation or arousal, after which respiratory status returns to normal by increasing the breathing amplitude and depth of respiration (11). Prior studies have identified several predictors of CPAP compliance, including BMI, AHI, Epworth Sleepiness Scale (ESS) score, sex, and age. (10, 14-15). Therefore, the present study aimed to evaluate clinical phenotypes and treatment compliance in patients with OSA and AHI >15, stratified by apnea index (<5 vs ≥5).
2. Materials and Methods
2.1 Study Design and Population
This cross‑sectional study was conducted among patients diagnosed with OSA at the sleep laboratory of Imam Khomeini Hospital, Tehran, Iran, between 2023and 2024. Data were collected using a structured questionnaire and review of medical records.
2.2 Inclusion and Exclusion Criteria
The inclusion criteria were a confirmed diagnosis of obstructive sleep apnea based on polysomnography, an apnea hypopnea index (AHI) >15 events/hour, and provision of written informed consent. Patients were excluded if they had incomplete clinical or polysomnographic data or if follow-up was not possible.
2.3 Sample Size and Data collection
Patients with confirmed OSA over the preceding two years were included using a census sampling method.
After obtaining informed consent, demographic and clinical data were recorded, including age, sex, menopausal status, body mass index (BMI), neck circumference, blood pressure status, history of smoking, alcohol consumption, and use of psychotropic substances.
Sleep‑related parameters extracted from PSG included AHI, apnea index, oxygen desaturation index, duration of oxygen saturation <90%, and snoring duration. Patients with AHI >15 were further categorized based on apnea index (<5 vs ≥5). Excessive daytime sleepiness was assessed using the Epworth Sleepiness Scale (ESS). Treatment modality (medical therapy, surgery, CPAP, or bilevel positive airway pressure [BiPAP]), compliance with the recommended treatment, average nightly usage (hours), and duration of device use (months) were recorded.
2.4 Epworth Sleepiness Scale
The ESS is a validated self‑administered questionnaire consisting of eight items assessing the likelihood of dozing in common daily situations. Each item is scored from 0 (no chance of dozing) to 3 (high chance of dozing), yielding a total score ranging from 0 to 24. A score >10 indicates excessive daytime sleepiness.
2.5 Statistical Analysis
Quantitative variables were expressed as mean ± standard deviation, and qualitative variables as frequency and percentage. Parametric or non‑parametric tests were applied based on data normality. Statistical analyses were performed using SPSS software version 22. A p‑value <0.05 was considered statistically significant.
3. Result
A total of 112 patients were included, comprising 59 women (52.7%) and 53 men (47.3%). The mean age was 51 ± 13.4 years (range: 18–85 years). Nearly all participants (99.1%) reported no history of smoking, psychotropic substance use, or alcohol consumption. The mean BMI was 31.84 ± 7.55 kg/m², and the mean neck circumference was 40.83 ± 3.38 cm (range: 34–55 cm). Among female participants, 85% were postmenopausal. According to the ESS, 69 patients (61.6%) experienced excessive daytime sleepiness. The mean AHI was 31.96 ± 43.14 events/hour (range: 6.3–159.5), and the mean ODI was 36.1 ± 29.88 events/hour (range: 1.3–140.6). The mean snoring duration during the sleep study was 308.9 ± 249.78 (range: 9–1244).
3.1 Apnea Index and AHI Stratification
Among all participants, 17 patients (15.2%) had AHI between 5 and <15, while 95 patients (84.8%) had AHI >15. When categorized by apnea index, 73 patients (62.5%) had apnea index <5 and 39 patients (34.8%) had apnea index ≥5. The distribution of apnea index differed significantly between AHI groups (p = 0.007) (Table 1).
3.2 Comparison of Clinical Variables
Patients with AHI >15 had a higher mean snoring duration and significantly higher ODI and duration of oxygen saturation <90% than patients with AHI 5–<15. No significant differences were observed in ESS scores or apnea‑to‑AHI ratio between groups (Table 2).
CPAP therapy, the mainstay non‑invasive treatment for OSA, delivers positive airway pressure to prevent upper airway collapse during sleep. Despite its proven efficacy, patient acceptance and long‑term adherence remain suboptimal, with reported adherence rates of approximately 50% (10). OSA leads to decreased arterial oxygen saturation or arousal, after which respiratory status returns to normal by increasing the breathing amplitude and depth of respiration (11). Prior studies have identified several predictors of CPAP compliance, including BMI, AHI, Epworth Sleepiness Scale (ESS) score, sex, and age. (10, 14-15). Therefore, the present study aimed to evaluate clinical phenotypes and treatment compliance in patients with OSA and AHI >15, stratified by apnea index (<5 vs ≥5).
2. Materials and Methods
2.1 Study Design and Population
This cross‑sectional study was conducted among patients diagnosed with OSA at the sleep laboratory of Imam Khomeini Hospital, Tehran, Iran, between 2023and 2024. Data were collected using a structured questionnaire and review of medical records.
2.2 Inclusion and Exclusion Criteria
The inclusion criteria were a confirmed diagnosis of obstructive sleep apnea based on polysomnography, an apnea hypopnea index (AHI) >15 events/hour, and provision of written informed consent. Patients were excluded if they had incomplete clinical or polysomnographic data or if follow-up was not possible.
2.3 Sample Size and Data collection
Patients with confirmed OSA over the preceding two years were included using a census sampling method.
After obtaining informed consent, demographic and clinical data were recorded, including age, sex, menopausal status, body mass index (BMI), neck circumference, blood pressure status, history of smoking, alcohol consumption, and use of psychotropic substances.
Sleep‑related parameters extracted from PSG included AHI, apnea index, oxygen desaturation index, duration of oxygen saturation <90%, and snoring duration. Patients with AHI >15 were further categorized based on apnea index (<5 vs ≥5). Excessive daytime sleepiness was assessed using the Epworth Sleepiness Scale (ESS). Treatment modality (medical therapy, surgery, CPAP, or bilevel positive airway pressure [BiPAP]), compliance with the recommended treatment, average nightly usage (hours), and duration of device use (months) were recorded.
2.4 Epworth Sleepiness Scale
The ESS is a validated self‑administered questionnaire consisting of eight items assessing the likelihood of dozing in common daily situations. Each item is scored from 0 (no chance of dozing) to 3 (high chance of dozing), yielding a total score ranging from 0 to 24. A score >10 indicates excessive daytime sleepiness.
2.5 Statistical Analysis
Quantitative variables were expressed as mean ± standard deviation, and qualitative variables as frequency and percentage. Parametric or non‑parametric tests were applied based on data normality. Statistical analyses were performed using SPSS software version 22. A p‑value <0.05 was considered statistically significant.
3. Result
A total of 112 patients were included, comprising 59 women (52.7%) and 53 men (47.3%). The mean age was 51 ± 13.4 years (range: 18–85 years). Nearly all participants (99.1%) reported no history of smoking, psychotropic substance use, or alcohol consumption. The mean BMI was 31.84 ± 7.55 kg/m², and the mean neck circumference was 40.83 ± 3.38 cm (range: 34–55 cm). Among female participants, 85% were postmenopausal. According to the ESS, 69 patients (61.6%) experienced excessive daytime sleepiness. The mean AHI was 31.96 ± 43.14 events/hour (range: 6.3–159.5), and the mean ODI was 36.1 ± 29.88 events/hour (range: 1.3–140.6). The mean snoring duration during the sleep study was 308.9 ± 249.78 (range: 9–1244).
3.1 Apnea Index and AHI Stratification
Among all participants, 17 patients (15.2%) had AHI between 5 and <15, while 95 patients (84.8%) had AHI >15. When categorized by apnea index, 73 patients (62.5%) had apnea index <5 and 39 patients (34.8%) had apnea index ≥5. The distribution of apnea index differed significantly between AHI groups (p = 0.007) (Table 1).
3.2 Comparison of Clinical Variables
Patients with AHI >15 had a higher mean snoring duration and significantly higher ODI and duration of oxygen saturation <90% than patients with AHI 5–<15. No significant differences were observed in ESS scores or apnea‑to‑AHI ratio between groups (Table 2).
Table 1. The number and percentage of apneas below 5 by AHI group in individuals with OSA.
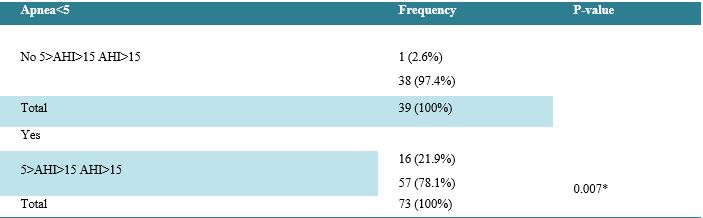
Table 2. The mean of snoring, ODI, EP, and Apnea/AHI in two groups among OSA patients.
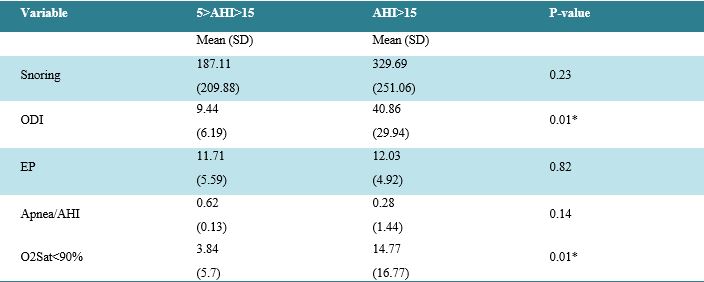
Table 2. The mean of snoring, ODI, EP, and Apnea/AHI in two groups among OSA patients.
3.3 Treatment Recommendations and Compliance
Of the 112 patients, 61 (54.5%) were recommended positive airway pressure therapy (CPAP or BiPAP), 8 (7.1%) were advised surgical or pharmacological treatment, and 9 patients did not receive treatment recommendations. Among those advised to use CPAP/BiPAP, only 28 patients (45.9%) obtained the device; financial constraints were the primary reason for non‑compliance (Table 3). All patients who obtained positive airway pressure devices had AHI >15. None of the patients with AHI between 5 and <15 received positive airway pressure therapy (Table 4).
Of the 112 patients, 61 (54.5%) were recommended positive airway pressure therapy (CPAP or BiPAP), 8 (7.1%) were advised surgical or pharmacological treatment, and 9 patients did not receive treatment recommendations. Among those advised to use CPAP/BiPAP, only 28 patients (45.9%) obtained the device; financial constraints were the primary reason for non‑compliance (Table 3). All patients who obtained positive airway pressure devices had AHI >15. None of the patients with AHI between 5 and <15 received positive airway pressure therapy (Table 4).
Table 3. The frequency and percentage of surgical compliance and instrument preparation in patients with OSA.
Table 4. Frequency and percentage of patients with OSA who purchased the instrument based on the AHI group.
Among device users, 27 of 28 patients used the device for ≥4 hours per night. Additionally, 25 patients (89.2%) continued therapy for more than three months. Patients with an AHI <5 demonstrated slightly better long‑term adherence, with all using the device ≥4 hours per night and the majority continuing therapy beyond three months. A significant association was observed between ESS score and AHI (Figure 1).
Figure 1. Relationship between Ep and AHI. (Prepared by Authors, 2026).
4. Discussion
Obstructive sleep apnea is the most common sleep-disordered breathing disorder, characterized by repeated obstruction of the upper airways (pharynx) during sleep, which can lead to decreased arterial oxygen saturation or arousal, after which respiratory status returns to normal by increasing breathing amplitude and depth (11). Therefore, this study aimed to evaluate the phenotype in patients suffering from obstructive sleep apnea with AHI> 15. The study consisted of 59 females and 53 males (112 patients). Pelosi et al. Also studied 138 patients consisting of 54.4% male and 45.6% female (12). In the Ernas study, the proportion was 54.8% male and 45.2% female (13). Previous studies have reported that the prevalence of the disease varies by sex, and the Male/Female ratio has been 3.1 to 5.1 and even 8.1 to 10.1 (14). In our study, the gender percentage differed from some studies, but the higher percentage of women in this study may be due to the choice of patients in the sleep clinic.
In the present study, the mean age of the patients was 51±13.4 years. Pelosi et al reported a mean age of 58 ± 11 years (12), while a study by Ernas et al reported a mean age of 54.7 (13). In 2012, Dipoosu et al. conducted a study on 488 people with a mean age of 53 ± 11 (15).
The mean age obtained in our study was similar to that in other studies. Furthermore, 99.1% of the patients in this study had no history of smoking or psychotropic substance use. Olayemi et al. (16) and Ernas et al. (13) reported that 8% and 16.6% of patients had a history of smoking, respectively, which may be due to cultural issues. In this study, 32.1% of OSA patients had a history of HTN. Ernas et al, reported a history of HTN in 30.6% of subjects (13). Another study reported HTN in 23.5% (16), which was similar to this study.
The mean BMI of patients in the present study was 31.84 ± 7.55. In other studies, BMI was reported as 33.1 ± 6 (12), 28.2 ± 5 (13) and 30.2 ± 5 (14). However, some studies reported BMI above 42.6 (17) and below 23.9 (16). BMI in this study was higher in women than in men (34 to 29.3), which was similar to the results of other studies. In one study, women had a BMI of 31.39 ± 7.12 versus 29.82 in men (P> 0.001) (13). The mean neck circumference of patients in the present study was 40.83. In other studies, similar results were reported where the mean neck circumference of patients was reported to be 42.4 ±3.4 (17) and 43.9 (13); these findings are similar to this study. In comparison between men and women, the BMI and neck circumference of women were lower than those of men.
The mean ODI in the present study was 36.1, which was higher in women than in men. In another study, women experienced a more severe ODI. In one study, the mean ODI in men and women was reported as 8.6 and 4.7, respectively, which showed a statistically significant difference (P = 0.001) (18). The mean EP worth Scale in the present study was 11.98 ± 5, which was similar to Kim's study with EP of 5.6±5 (19). The mean AHI of patients was 43.14±31.96 in the current study. In other studies, AHI was reported to be 45.5 ± 26.56 (12) and 38.4 (20), which were similar to the results obtained in our study. In another study, AHI was reported in men and women at 7.7 ± 5.2l and 10.4 ± 9.5 (P <0.001), which differed from our results, but like the results of our study, AHI was more commonly reported in men (13).
Among 112 patients, 61 were recommended to use positive airway pressure, of which 28 (45.9%) provided the instrument, and 27 (96.4%) of the 28 patients who provided the instrument used the instrument for at least 4 hours at night, and 25 patients (89.2%) continued to use the instrument for more than 3 months. Of the 28 patients who provided the instrument and all had AHI above 15, 15 had apnea below 5 and 13 had apnea above 5. Of the 15 people with apnea less than 5, all used the instrument for more than 4 hours, and 14 people continued its use after 3 months. The results of a study also showed that 81% of people used CPAP for at least 2 hours and 70% for more than 4 hours (21). Another study comprising 69 patients diagnosed with OSA by polysomnography between 2002 and 2007 reported that 41 patients (59.4%) were satisfied with positive airway pressure (PAP) therapy after 1 month, while 34.7% continued using PAP for more than 3 months. (19). The results of another study showed that 46% of patients treated with continuous positive airway pressure (CPAP) continued to use the device for at least 4 hours per night, while at least 70% continued its use at night (22). Another study reported that 34.7% of patients continued treatment for more than 3 months (20). Comparison of these findings suggests that device adherence among our patients was comparable to that reported in previous studies. In this study, compliance was compared based on age, BMI, AHI, smoking, and alcohol consumption. AHI was 47.6 in the group with good compliance and 40.52 in the group with low compliance (P = 0.2). Also, a negative relationship between ESS and night time use has been observed, and the type of mask does not affect compliance (12).
Another study was performed to identify the risk factors for treatment failure and lack of compliance in patients with the sleep apnea/hypopnea syndrome (SAHS) treated by CPAP, where 131 of 949 identified patients underwent follow-up, and compliance was at least 4 hours per night in 70% of the nights, of which 48 patients did not have CPAP treatment compliance. In aforementioned study, low AHI was identified as a risk factor for lack of compliance (P = 0.004), but no relationship was found between compliance and other factors such as age, Oxygen saturation (O2Sat), sex, alcohol use, and ESS (17). Most studies in Europe have reported 46-80% compliance (22).
Some other studies have emphasized the lack of association between primary AHI and compliance (23) and also noted that improvement in sleep quality at the start of CPAP treatment was the most important predictor of its use. Regular follow-up and effective interventions also increased compliance (24). Conversely, some studies have reported a positive effect of AHI on compliance (25).
5. Conclusion
This study demonstrates that phenotype-based classification enhances the clinical utility of CPAP therapy in patients with moderate to severe OSA. Among patients with AHI >15, those with greater hypoxic burden and lower apnea index exhibited higher adherence to positive airway pressure therapy, both in nightly usage and long‑term continuation.
These findings reinforce the limitation of relying solely on AHI to guide treatment decisions and highlight the importance of incorporating apnea index and hypoxemia‑related parameters into routine clinical assessment. A phenotype‑driven approach may improve patient selection for CPAP therapy, optimize resource allocation, and ultimately enhance adherence and clinical outcomes. Future studies with larger cohorts and longitudinal follow-up are warranted to validate these findings and to further refine phenotype‑guided treatment algorithms. Integrating simple polysomnographic markers into personalized OSA management holds promise for improving both patient experience and therapeutic effectiveness.
6. Declarations
6.1 Acknowledgments
We would like to sincerely thank the sleep testing department of Imam Khomeini Hospital for their cooperation in implementing the project.
6.2 Ethical Considerations
The study was approved by the Research Council of the Medical School and the institutional ethics committee (Ethical approval code: IR.TUMS.IKHC.REC.1399.145). Written informed consent was obtained from all participants. Patient confidentiality was strictly maintained in accordance with the Declaration of Helsinki and local ethical guidelines.
6.3 Authors' Contributions
project management and validation: Dr Hamidreza Abtahi, research and writing Nooshin Jalili, drafting, review, and editing, supervision: Besharat Rahimi
6.4 Conflict of Interest
The funders had no role in the design of the study; in the collection, analyses, or interpretation of data; in the writing of the manuscript; or in the decision to publish the results.
6.5 Fund or Financial Support
This research received no external funding
6.6 Using Artificial Intelligence Tools (AI Tools)
The authors were not utilized AI Tools.
Type of Study: Original Research Article |
Subject:
Clinical Medicine
Received: 2026/02/13 | Accepted: 2026/06/2 | Published: 2026/06/29
Received: 2026/02/13 | Accepted: 2026/06/2 | Published: 2026/06/29
References
1. Beaudin A, Waltz X, Hanly PJ, Poulin MJ. Impact of obstructive sleep apnoea and intermittent hypoxia on cardiovascular and cerebrovascular regulation. Exp. Physiol, 2017; 102: 743-63. [DOI:10.1113/EP086051] [PMID]
2. Choi J, Song JS, Lee YJ, Jeong DU. Periodic limb movements in sleep is associated with increased mortality. Psychiatr Investig. 2017; 14, 669-673. [DOI:10.4306/pi.2017.14.5.669] [PMID] [PMCID]
3. Edwards BA, Wellman A, Sands SA, Owens RL, Eckert DJ, White DP, et al. Personalized treatment approaches for obstructive sleep apnea. Am J Respir Crit Care Med. 2023;208(8):889 901.
4. Hnin Kh,Mukherjee S,Antic N,Catcheside P,Coetzer Ch,McEvoy D,et al. The impact of ethnicity on the prevalence and severity of obstructive sleep apnea. Sleep Med Rev. 2018; 4(1): 78-86. [DOI:10.1016/j.smrv.2018.01.003] [PMID]
5. da Silva P, Zhang L. Continuous positive airway pressure for adults with obstructive sleep apnea and cardiovascular disease: A meta-analysis of randomized trials. Sleep Med. 2019; 5(4): 28-34. [DOI:10.1016/j.sleep.2018.09.030] [PMID]
6. Malhotra A, Ayappa I, Ayas N, Collop N, Kirsch D, Mehra R. Advances in the diagnosis of obstructive sleep apnea. Lancet Respir Med. 2023;11(6):543 56.
7. Kapur VK, Auckley DH, Chowdhuri S, Kuhlmann DC, Mehra R, Ramar K, et al. Clinical practice guideline for diagnostic testing for adult obstructive sleep apnea. J Clin Sleep Med. 2024;20(2):259 271.
8. Bajwah S, Ross JR, Wells AU, et al. Palliative care for patients with advanced fibrotic lung disease: a randomised controlled phase II and feasibility trial of a community case conference intervention. Thorax. 2015; 70: 8-30. [DOI:10.1136/thoraxjnl-2014-206583] [PMID]
9. Eckert DJ. Phenotypic approaches to obstructive sleep apnoea - New pathways for targeted therapy. Lancet Respir Med. 2023;11(4):321 34.
10. Ramos A, Figueredo P, Shafazand Sh, Chediak A, Abreu A, Dib S, et al.Obstructive sleep apnea phenotypes and markers of vascular disease: A review. Front Neurol, 2017; 8: 659. [DOI:10.3389/fneur.2017.00659] [PMID] [PMCID]
11. de Ruiter M, Benoist L, de Vries N , de Lange J. Durability of treatment efects of the sleep position trainer versus oral appliance therapy in positional OSA: 12- month follow-up of a randomized controlled trial. Sleep Breath. 2018; 2(4): 441-50. [DOI:10.1007/s11325-017-1568-4] [PMID] [PMCID]
12. Pelosi LB, Silveira ML, Eckeli AL, Chayamiti EM, Almeida LA, Sander HH, et al. The importance of clinical monitoring for compliance with continuous positive airway pressure. Braz J Otorhinolaryngol. 2017; 8(3): 439-44. [DOI:10.1016/j.bjorl.2016.05.013] [PMID] [PMCID]
13. Erna S. Obstructive sleep apnoea in the general population: highly prevalent but minimal symptoms, Eur Respir J. 2016; 4(7): 194-202. [DOI:10.1183/13993003.01148-2015] [PMID]
14. Gabbay I. Age- and gender-related characteristics of obstructive sleep apnea. Sleep Breath. 2012; 1(6): 453-60. [DOI:10.1007/s11325-011-0523-z] [PMID]
15. Ghosh D. Identifying poor compliance with CPAP in obstructive sleep apnoea: A simple prediction equation using data after a two-week trial. Respir Med. 2013;107 (6): 936-42. [DOI:10.1016/j.rmed.2012.10.008] [PMID]
16. Awopeju O, Fawale M, Olowookere S, Salami O, Adewole O , Erhabor G. The risk of obstructive sleep apnea and its association with indices of general and abdominal obesity in a Nigerian family practice clinic: a crosssectional study.Alexandria J Med. 2020; 56(1): 14-20. [DOI:10.1080/20905068.2019.1711304]
17. Lin H. Factors associated with noncompliance to treatment with positive airway pressure. Arch Otolaryngol Head Neck Surg. 2007;13(3): 69-72. [DOI:10.1001/archotol.133.1.69] [PMID]
18. Anttalainen U, Saaresranta T, Aittokallio J,Kalleinen N,Vahlberg T,Virtanen I, et al. Impact of menopause on the manifestation and severity of sleep-disordered breathing. Acta Obstet Gynecol Scand. 2006; 8(5): 1381-88. [DOI:10.1080/00016340600935649] [PMID]
19. Kim J. Compliance with positive airway pressure treatment for obstructive sleep apnea, Clin Experiment Otorhinolaryngol. 2009; 2(2): 90-96. [DOI:10.3342/ceo.2009.2.2.90] [PMID] [PMCID]
20. Hayashi Sh , Tamaoka M , Tateishi T , Murota Y , Handa I, Miyazaki Y.A new feature with the potential to detect the severity of obstructive sleep apnoea via snoring sound analysis.Int J Environ Res Public Health. 2020; 1(7): 29- 51. [DOI:10.3390/ijerph17082951] [PMID] [PMCID]
21. Kribbs NB, Pack AI, Kline LR, Smith PL, Schwartz AR, Schubert NM, et al. Objective measurement of patterns of nasal CPAP use by patients with obstructive sleep apnea. Am Rev Respir Dis. 1993; 147(4): 887-95. [DOI:10.1164/ajrccm/147.4.887] [PMID]
22. McArdle N, Devereux G, Heidarnejad H, Engleman HM, Mackay TW, Douglas NJ. Long-term use of CPAP therapy for sleep apnea/hypopnea syndrome. Am J Respir Crit Care Med. 1999; 15(9): 1108-14. [DOI:10.1164/ajrccm.159.4.9807111] [PMID]
23. Claudio W , Dibur E, Salomone C, Bartolo C. Compliance with continuos positive airway pressure in patients with sleep apnea/hypopnea syndrome.Medicina. 2004;64(5):395-9
24. Ayas N , Patel S, Malhotra A, Schulzer M, Malhotra M, Jung D, et al. Auto-titrating versus standard continuous positive airway pressure for the treatment of obstructive sleep apnea: results of a meta-analysis. Sleep. 2004; 27(2): 249-53. [DOI:10.1093/sleep/27.2.249] [PMID]
25. Hui DS, Choy DK, Li TS, Ko FW, Wong KK, Chan JK, et al. Determinants of continuous positive airway pressure compliance in a group of Chinese patients with obstructive sleep apnea. Chest. 2001; 120(1): 170e6. [DOI:10.1378/chest.120.1.170] [PMID]
Send email to the article author
| Rights and permissions | |
 |
This work is licensed under a Creative Commons Attribution-NonCommercial 4.0 International License. |
Copyright Policy
Journal of Advances in Medical and Biomedical Research by Zanjan University of Medical Sciences is licensed under CC BY-NC 4.0